An ESR1 mutation means the estrogen receptor in your cancer cells has changed shape and can switch itself on without estrogen. Aromatase inhibitors lose much of their effect at that point, but several drugs made for this exact change are now approved in the US, and the newest arrived on November 16, 2026.
Table of Contents

Quick answer: ESR1-mutated, ER-positive, HER2-negative advanced breast cancer is usually treated with a newer hormone drug that blocks or breaks down the estrogen receptor directly. FDA-approved choices are elacestrant (Orserdu), imlunestrant (Inluriyo, alone or with abemaciclib), vepdegestrant (Veppanu), camizestrant (Etcamah) with a CDK4/6 inhibitor, and giredestrant (Wilserdly) with everolimus. Fulvestrant shots and capivasertib remain options in some cases. The right one depends on prior treatment, timing and other mutations.
What an ESR1 mutation changes about treatment
Doctors sort breast tumors by the receptors on their cells, and ER-positive is by far the largest of the main breast cancer types: about three in four breast cancers depend at least partly on estrogen. The ESR1 gene holds the instructions for that estrogen receptor. When the gene mutates, the receptor takes a shape that signals “grow” whether estrogen is around or not. None of the drugs below help in triple-negative breast cancer, which has no estrogen receptor for them to act on.
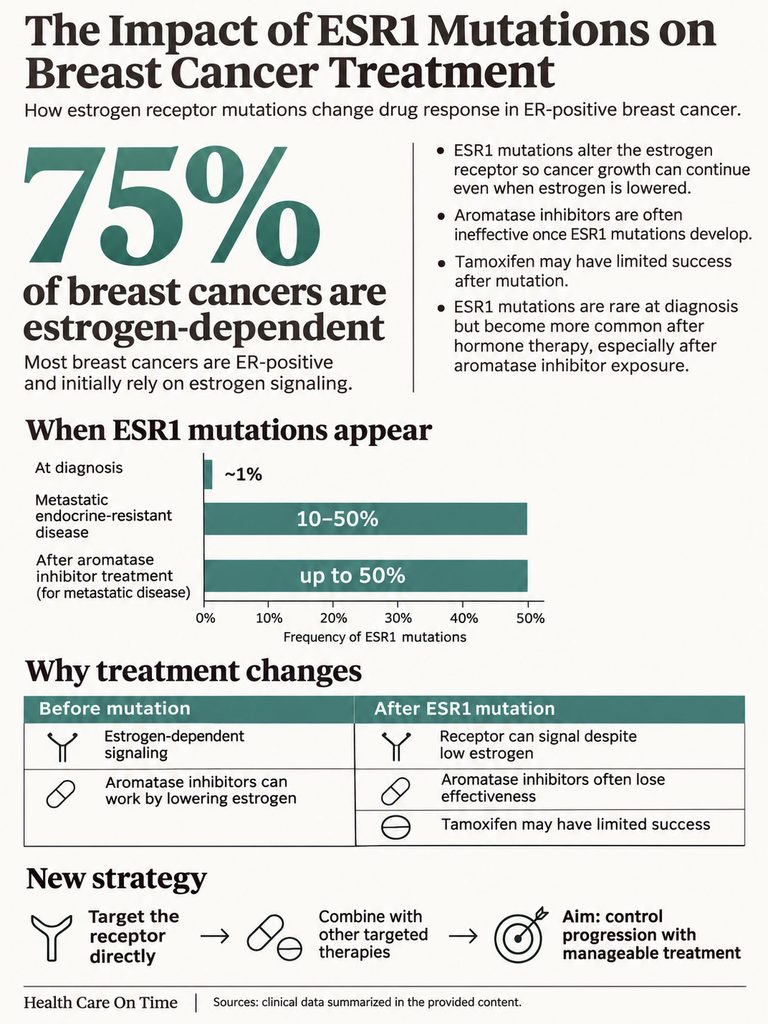
Aromatase inhibitors such as letrozole, anastrozole and exemestane work by lowering estrogen. A receptor that no longer needs estrogen doesn’t care much how low those levels go, so these drugs often stop working once the mutation shows up. Tamoxifen works differently. It sits on the receptor and blocks it, which is closer to how the new drugs work, but it doesn’t destroy the receptor, and it’s rarely the answer for a cancer that has already outgrown an aromatase inhibitor.
The mutation is almost always acquired during treatment. In 2013, a Memorial Sloan Kettering team found ESR1 mutations in tumors that had grown resistant to hormone therapy but not in tumors sampled before therapy, and that work led, ten years later, to the first drug built for it. The change appears mostly after time on aromatase inhibitors and only rarely after tamoxifen. Because it arises inside the tumor, it isn’t inherited and can’t be passed to children, which makes it a different matter from the BRCA changes a genetic counselor tests for.
Lab reports often name the exact change, such as Y537S or D538G, two of the variants found most often, and some research suggests certain variants resist fulvestrant more than others. The FDA labels key on whether an authorized test finds a qualifying ESR1 mutation, not on which one, so the letter-and-number code rarely changes which drug is offered.
Instead of lowering estrogen, the newer drugs go after the receptor itself. Some block it, others tag it for destruction, and vepdegestrant goes a step further by recruiting the cell’s own protein-disposal system to remove it. Most can be paired with a second targeted drug that slows a different growth pathway. None of them is a cure. The aim is to keep the cancer controlled for as long as possible with a tolerable daily routine, then move to the next option when it grows.
How often the mutation turns up
ESR1 mutations are rare at first diagnosis and common after hormone therapy for metastatic disease. Estimates vary with how and when people were tested, and the likelihood rises with each additional round of aromatase inhibitor treatment.
| Measure | Figure | Source |
| ESR1 mutations in primary (newly diagnosed) breast tumors | About 1% | College of American Pathologists, updated Oct 2026 |
| ESR1 mutations in metastatic, hormone-resistant tumors | 10% to 50% | College of American Pathologists |
| ESR1 mutations in metastatic cancer treated with aromatase inhibitors | Up to half | Living Beyond Breast Cancer, reviewed Jul 2026 |
| Liquid biopsy study of more than 500 people with hormone-resistant metastatic disease (2016) | About 30% had one of the two most common mutations | Memorial Sloan Kettering |
| PALOMA-3 trial participants (fulvestrant with or without palbociclib) | 25.3% (91 of 360) had ESR1 mutations | Dustin et al., Cancer, 2019 |
| SoFEA trial participants | 39.1% (63 of 161) had ESR1 mutations | Dustin et al., Cancer, 2019 |
| Distant-stage breast cancer, all subtypes, 5-year relative survival | 32% (diagnosed 2015 to 2021) | American Cancer Society, from SEER |
Finding it: the ctDNA blood test
Most ESR1 results now come from a liquid biopsy. It’s a blood draw. Tumors shed small fragments of DNA into the bloodstream (circulating tumor DNA, or ctDNA), and the lab separates the plasma, pulls out that DNA and reads it with next-generation sequencing. Each new drug is tied to a specific FDA-authorized test: Guardant360 CDx for elacestrant, imlunestrant, vepdegestrant and camizestrant, and FoundationOne Liquid CDx for giredestrant.
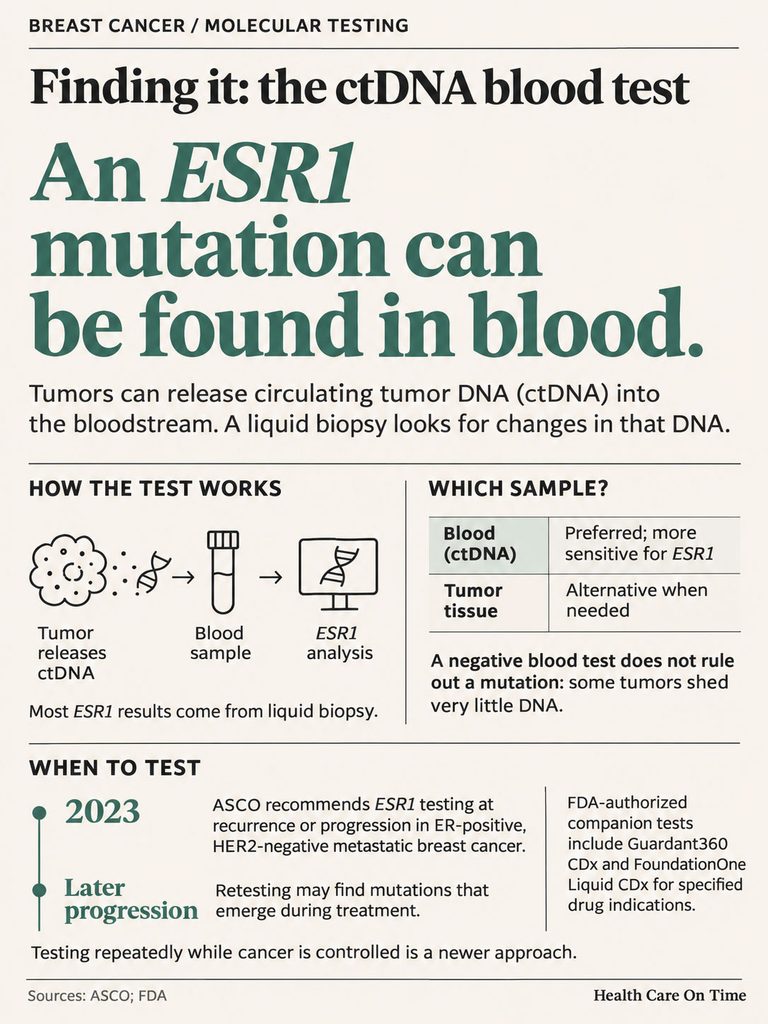
Routine ESR1 testing whenever metastatic ER-positive, HER2-negative cancer recurs or grows on hormone therapy, with or without a CDK4/6 inhibitor, has been part of ASCO guidance since 2023. Blood is the preferred sample. It picks up the mutation more reliably than tissue, partly because ESR1 changes develop under treatment pressure and usually can’t be found in the original tumor removed at diagnosis. A biopsy of a new metastasis, read with next-generation sequencing, is the alternative, and some doctors order both.
A negative blood result can happen when a tumor sheds very little DNA into the bloodstream, so a clean report doesn’t always mean the mutation is absent. That’s one reason some oncologists add a tissue biopsy when the result doesn’t fit the clinical picture.
A negative result isn’t permanent, and retesting at a later progression is reasonable because the mutation can appear after more time on treatment. The same sample can often be checked for other tumor biomarkers such as PIK3CA, AKT1 and PTEN, and those results decide whether capivasertib is on the list.
Testing on a schedule while the cancer is still under control is newer. It’s what made the camizestrant trial possible, and whether everyone on first-line treatment should be tested this way is still being argued over.
The ESR1 treatment options, side by side
Eight regimens matter for an ESR1-mutated cancer in the US as of November 2026. Six use one of five new oral estrogen receptor drugs, with imlunestrant counted both alone and with abemaciclib. The other two, fulvestrant combinations and capivasertib, are older, broader options that still get used.

| Treatment | How it’s taken | When it’s used (FDA label) | Key trial result in ESR1-mutated cancer | Main side effects |
| Giredestrant (Wilserdly) + everolimus | Both by mouth, once daily | After cancer returns during or after adjuvant hormone therapy, or grows on at least 1 hormone regimen for metastatic disease; approved Nov 16, 2026 | evERA, 207 patients: median PFS 10 vs 5.5 months (HR 0.38) (FDA) | Mouth sores, rash, fatigue, diarrhea, muscle and bone pain, pneumonitis, nausea; slow heart rate warning |
| Camizestrant (Etcamah) + CDK4/6 inhibitor | Pill once daily, CDK4/6 pill continues | When a blood test finds ESR1 after at least 6 months on an aromatase inhibitor plus CDK4/6 inhibitor, before the cancer grows; accelerated approval Sep 4, 2026 | SERENA-6, 315 patients: median PFS 16 vs 9.2 months (HR 0.44) (FDA) | Low blood counts, visual disturbances 34%, fatigue 23%, slow heart rate 8%; boxed warning for heart rhythm with QTc-prolonging drugs |
| Imlunestrant (Inluriyo) + abemaciclib | Two pills by mouth | After at least 1 line of hormone therapy; approved Sep 18, 2026 | EMBER-3 subgroup, 159 patients: median PFS 11.1 vs 5.5 months vs imlunestrant alone (HR 0.53) (FDA) | Abemaciclib label warns of diarrhea, low neutrophils, lung inflammation, liver injury and blood clots |
| Imlunestrant (Inluriyo) alone | Pill once daily on an empty stomach | After at least 1 line of hormone therapy; approved Sep 25, 2025 | EMBER-3, 256 patients: median PFS 5.5 vs 3.8 months (HR 0.62) (FDA) | Low hemoglobin, muscle and bone pain, fatigue, diarrhea, nausea, raised liver enzymes |
| Vepdegestrant (Veppanu) | Pill once daily with food | After at least 1 line of hormone therapy; approved May 1, 2026 | VERITAC-2, 270 patients: median PFS 5.0 vs 2.1 months vs fulvestrant (HR 0.57) (FDA) | Low white cells, raised liver enzymes, muscle and bone pain, fatigue, nausea; QTc prolongation in 10% |
| Elacestrant (Orserdu) | Pill once daily with food | Postmenopausal women and adult men after at least 1 line of hormone therapy; approved Jan 27, 2023 | EMERALD, 228 patients: median PFS 3.8 vs 1.9 months (HR 0.55) (FDA) | Muscle and bone pain, nausea, vomiting, fatigue, raised cholesterol and triglycerides, hot flushes |
| Fulvestrant (Faslodex) + palbociclib, abemaciclib or ribociclib | Two shots in the buttocks on days 1, 15 and 29, then monthly, plus a pill | After hormone therapy; one of the longest-used options | PALOMA-3, 91 patients with ESR1 mutations: PFS 9.4 vs 3.6 months with fulvestrant alone (2019 review) | Injection site pain 12%, nausea 10%, bone pain 9% with fulvestrant alone |
| Capivasertib (Truqap) + fulvestrant | Pill twice daily, 4 days on and 3 off, plus shots | Only if PIK3CA, AKT1 or PTEN changes are present, after an aromatase inhibitor; approved Nov 16, 2023 | CAPItello-291, 289 patients with those changes: median PFS 7.3 vs 3.1 months (HR 0.50) (FDA) | Diarrhea, skin reactions, high blood sugar, nausea, fatigue, mouth sores |
PFS means progression-free survival, the time until scans show the cancer growing or the person dies. HR is the hazard ratio; 0.38 means a 62% lower risk of progression or death during the trial, compared with the control group.
The PFS column doesn’t rank the drugs against each other, because each trial used a different control, enrolled people at a different point in their illness and started the clock in a different place. Everyone in the elacestrant trial had already been on a CDK4/6 inhibitor, some after two lines of hormone therapy, while the camizestrant figure is measured from the moment the mutation shows up in blood, often long before scans change. No trial has put these drugs head to head.
Across the trials, the ESR1-targeted drug beat older hormone therapy in people whose cancer carried the mutation, and where results for people without the mutation were published, the benefit faded. Elacestrant’s hazard ratio in that group was 0.86, too weak to explain the overall result on its own, and imlunestrant alone showed no improvement over standard therapy in people whose blood test found no ESR1 mutation.
The newest approval: giredestrant plus everolimus
On November 16, 2026, the FDA approved giredestrant (Wilserdly, Genentech) for use with everolimus, roughly four weeks ahead of its target date. Everolimus is an mTOR inhibitor, a pill that slows a growth-signaling pathway cancer cells often lean on once hormone therapy fails, and both drugs are taken by mouth once a day.
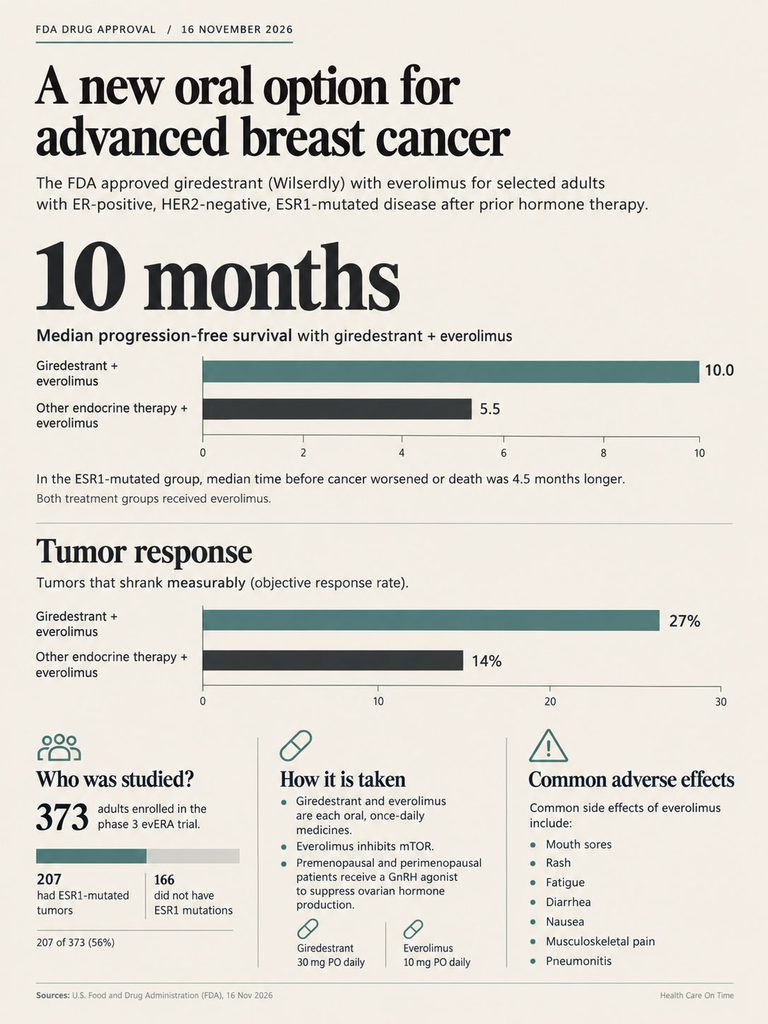
The approval covers adults with ER-positive, HER2-negative, ESR1-mutated breast cancer that is locally advanced or metastatic and that came back during or after hormone therapy given after surgery, or grew on at least one hormone-based regimen for metastatic disease. The mutation has to be confirmed with FoundationOne Liquid CDx.
The evERA trial enrolled 373 adults, 207 of them with ESR1-mutated tumors. Everyone got everolimus. Half also got giredestrant, and the other half got their doctor’s choice of exemestane, fulvestrant or tamoxifen. In the mutated group the giredestrant pair held the cancer back for a median of 10 months against 5.5, and tumors shrank in 27% versus 14%. Survival data weren’t mature at approval, so nobody can say yet whether longer control means longer life.
Everolimus brings its own well-known side effects, led by mouth sores (stomatitis). Rash, fatigue, diarrhea, muscle and bone pain, pneumonitis (lung inflammation) and nausea each affected at least 20% of people on the combination, and common lab changes included low blood counts, low calcium, potassium and sodium, and higher liver enzymes and creatinine. Giredestrant itself can slow the heart rate (bradycardia) and can harm a developing fetus.
Premenopausal and perimenopausal women and men in the trial also got a GnRH agonist to shut down hormone production, unless a man had had both testicles removed, so anyone in those groups should expect the care team to discuss ovarian or testicular suppression before starting.
Camizestrant and the switch-before-progression approach
Camizestrant (Etcamah, AstraZeneca) is approved for a moment when nothing looks wrong on scans yet.
The usual first treatment for ER-positive, HER2-negative metastatic breast cancer is an aromatase inhibitor plus a CDK4/6 inhibitor such as palbociclib, ribociclib or abemaciclib. In the double-blind SERENA-6 trial, people on that combination had regular blood tests looking for ESR1 in circulating tumor DNA. When the mutation appeared and the cancer hadn’t grown, 315 patients were randomly assigned either to swap the aromatase inhibitor for camizestrant while keeping the CDK4/6 inhibitor, or to stay on the aromatase inhibitor. Median progression-free survival was 16 months after the switch against 9.2 months without it.

The FDA granted accelerated approval on September 4, 2026. In practice, the switch is simple. The aromatase inhibitor stops, camizestrant starts, and the CDK4/6 inhibitor carries on at the dose already being used. To qualify, a person needs at least six months of an aromatase inhibitor plus a CDK4/6 inhibitor as initial treatment, no progression, and an ESR1 mutation found with Guardant360 CDx.
Months earlier, the FDA’s own advisory committee had voted 6 to 3 on April 30, 2026, that switching early hadn’t shown clinically meaningful benefit, mostly because survival data were immature, and one member said a survival benefit would have changed his vote. The agency approved it anyway, tying the indication to progression-free survival measured from the time the mutation was detected, and accelerated approval means further data are expected. Whether repeated blood testing in people with no symptoms helps them live longer, or mainly moves the next treatment earlier, is still an open question. For someone who feels well on first-line treatment, it means deciding whether to change drugs based on a blood result alone, a choice to talk through before the first test comes back.
Visual disturbances such as flashes of light (photopsia) affected 34% of people taking camizestrant, mostly mildly, and fatigue affected 23%. Bradycardia occurred in 8%, with the largest drop in heart rate around day 15. Low neutrophil and white cell counts were very common, partly from the CDK4/6 inhibitor. A boxed warning covers dangerous heart rhythms when camizestrant is combined with ribociclib or other drugs that prolong the QT interval, so an ECG is done before starting and weekly for the first two weeks, and people who take a beta-blocker or have a resting heart rate below 60 get closer heart rate checks for the first 30 days.
Three single-pill options
Elacestrant (Orserdu)
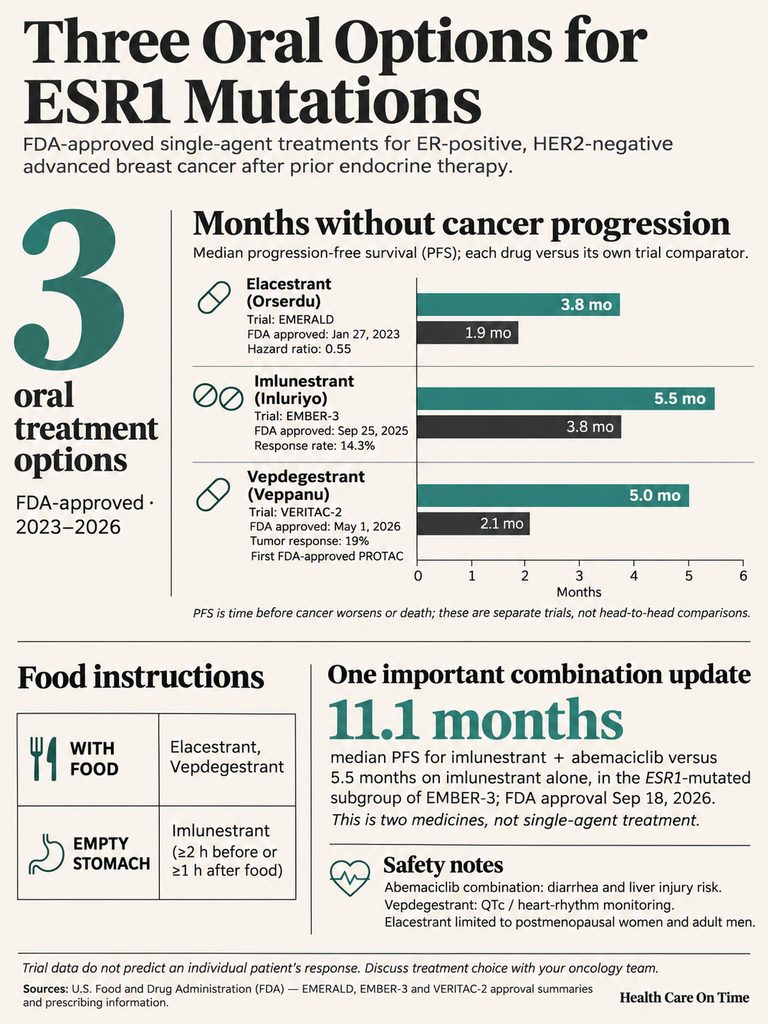
Elacestrant has the longest track record of the group, and it’s the only one whose label is limited to postmenopausal women and adult men. Approved on January 27, 2023, it was tested in a heavily pretreated group: everyone in EMERALD had already had a CDK4/6 inhibitor, and the comparison was fulvestrant or an aromatase inhibitor. Among the 228 people with ESR1 mutations, median progression-free survival was 3.8 months against 1.9. Small as those numbers look, the hazard ratio of 0.55 means the risk of progression fell by nearly half. It’s one of the options ASCO names for ESR1-mutated tumors and is taken with food.
Imlunestrant (Inluriyo), alone or with abemaciclib
Imlunestrant is the one pill here that has to go in on an empty stomach. The rule is strict: at least two hours before or one hour after eating, and some people find that harder to live with than a with-food pill. On its own (approved September 25, 2025) it gave 256 people with ESR1 mutations a median of 5.5 months before progression, compared with 3.8 months on fulvestrant or exemestane, and tumors responded in 14.3% versus 7.7%.
A year later, on September 18, 2026, the FDA approved it with abemaciclib (Verzenio). In 159 people with ESR1 mutations from the same EMBER-3 trial, the pair reached 11.1 months against 5.5 with imlunestrant alone, and tumors shrank in 35% versus 15%. This was an exploratory subgroup, so the estimate is less certain than a main trial result. Abemaciclib can cause diarrhea, low neutrophils, lung inflammation, liver injury and blood clots, and those risks come on top of whatever imlunestrant causes.
Vepdegestrant (Veppanu)
Vepdegestrant is the only one of the five new pills tested directly against fulvestrant shots alone, and it’s also the first approved PROTAC (proteolysis targeting chimera), a molecule that tags the estrogen receptor for the cell’s protein-recycling machinery. Approved May 1, 2026, it was studied in VERITAC-2 in people who’d had one or two prior hormone therapies, one including a CDK4/6 inhibitor. In the 270 with ESR1 mutations, the pill gave 5.0 months against 2.1 on fulvestrant, with tumor shrinkage in 19% versus 4%. It’s taken with food. QTc prolongation, a change in heart rhythm seen on an ECG, was reported in 10% of trial patients, so low potassium and magnesium are corrected before and during treatment and the ECG is repeated about four weeks in.
Fulvestrant shots and capivasertib
Before the oral drugs arrived, fulvestrant was the main tool once aromatase inhibitors failed, and it’s still widely used. It does work against many ESR1-mutated cancers, though a 2017 study of more than 900 patients identified ESR1 mutations that leave it only partly effective. In the PALOMA-3 trial, a quarter of patients (91 of 360) had ESR1 mutations, and adding palbociclib to fulvestrant lengthened progression-free survival from 3.6 to 9.4 months in that group, as summarized in a 2019 review of ESR1 research. Those patients hadn’t had a CDK4/6 inhibitor before, which is uncommon today, so the result may not carry over to someone whose cancer already grew on one.
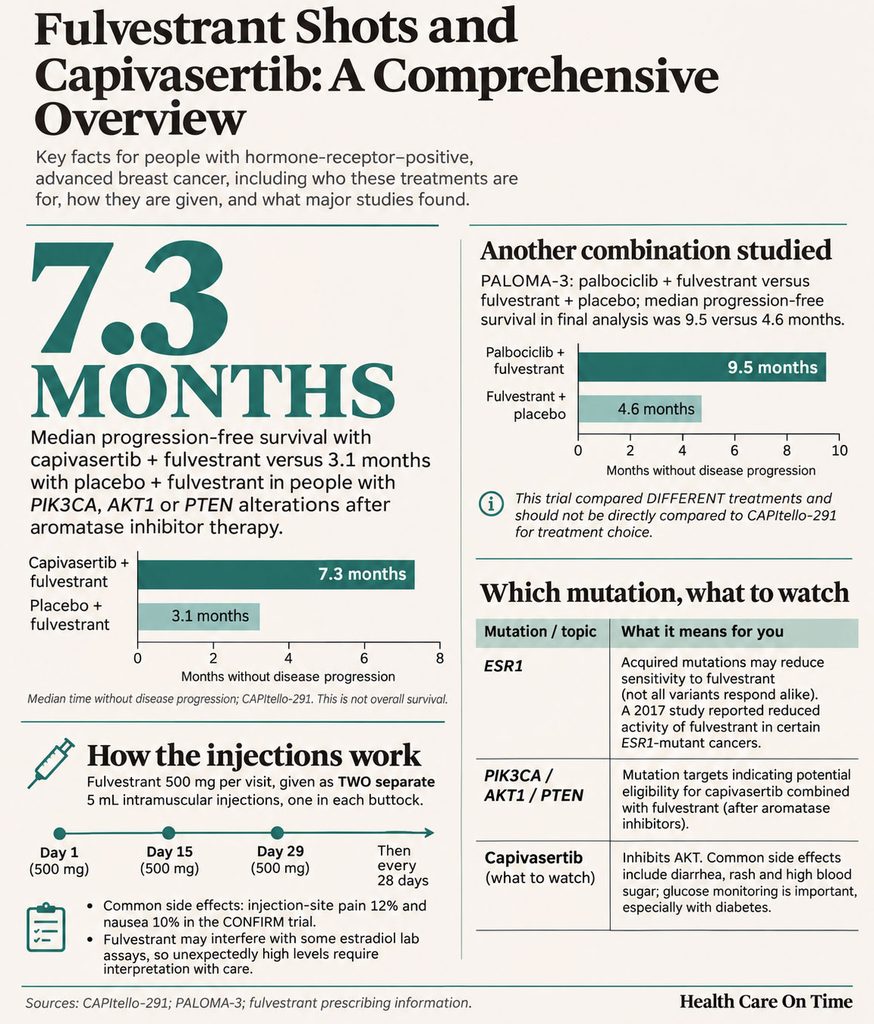
The practical cost is the schedule: 500 mg as two 5 mL injections, one in each buttock, on days 1, 15 and 29 and then monthly. Injection site pain (12%), nausea (10%) and bone pain (9%) were the most common side effects in the main trial of that dose. Fulvestrant can also make estradiol blood tests read falsely high, so a surprising hormone result during treatment should be read with that in mind.
Fulvestrant is also the partner drug for capivasertib (Truqap), which isn’t an ESR1 drug at all. Capivasertib targets the AKT pathway and is approved only when a tumor has a PIK3CA, AKT1 or PTEN change and has grown after aromatase inhibitor treatment. ESR1 and PIK3CA mutations can sit in the same tumor, so some people qualify for both kinds of drug. In CAPItello-291, people with those alterations went a median of 7.3 months before progression on the combination versus 3.1 months on fulvestrant alone, while in people without them the effect was much weaker (hazard ratio 0.79). Diarrhea, rash and high blood sugar are the side effects people notice most, which is why diabetes control matters before starting.
Choosing between one pill and a combination
Metastatic ER-positive breast cancer is treated one line at a time, and a treatment that’s working is generally kept going until scans confirm progression. For most people the first line is an aromatase inhibitor with a CDK4/6 inhibitor. If ESR1 appears in blood during that line and scans are stable, the camizestrant switch is the only FDA-approved move. If the cancer grows instead, a fresh ESR1 test, along with PIK3CA, AKT1 and PTEN, usually guides the second line.
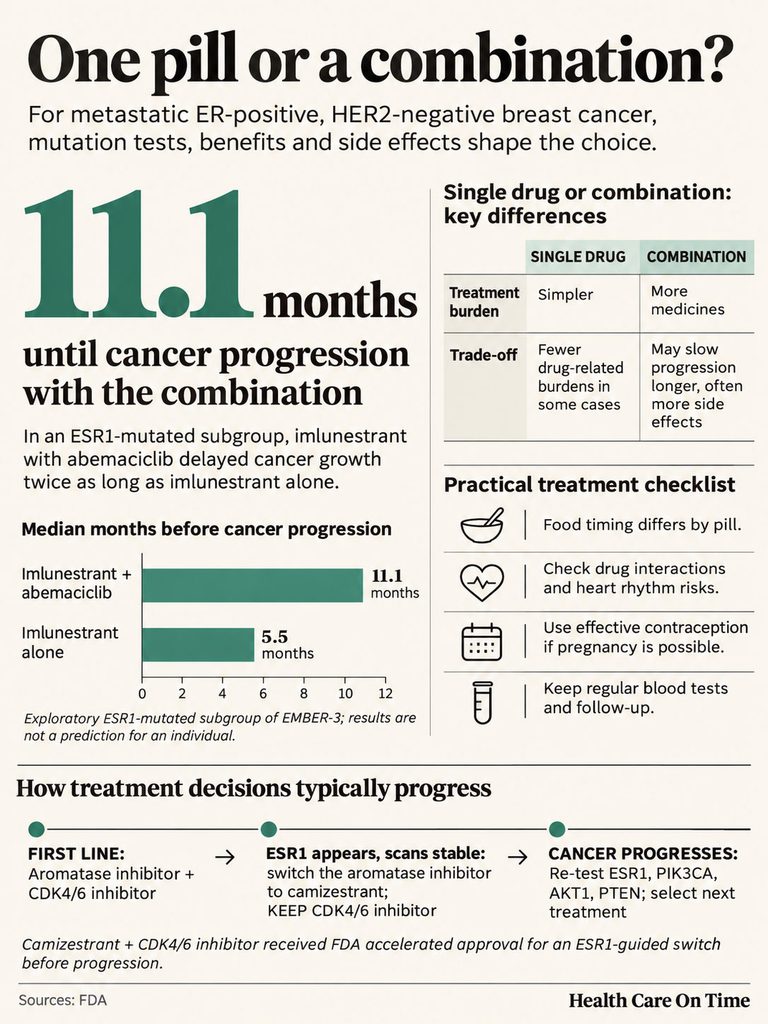
That second line now has many branches, and current guidance lists them without ranking them. The choice is often a trade. In the trials, the combinations (imlunestrant with abemaciclib, giredestrant with everolimus) held the cancer back for longer, but they add the partner drug’s side effects, from diarrhea and low blood counts with abemaciclib to mouth sores and lung inflammation with everolimus, and those can shape how a person feels day to day for months. A single pill such as elacestrant, imlunestrant or vepdegestrant carries a shorter list of problems, and direct comparisons between the two approaches don’t exist yet. Chemotherapy remains an option at any point, and clinical trials are worth asking about at every step.
Daily routine counts in that choice more than people expect. No monthly injections is a real gain, yet the pills don’t share rules: elacestrant and vepdegestrant go with food, imlunestrant needs an empty stomach, and camizestrant and giredestrant can be taken either way. Vepdegestrant tablets are swallowed whole. Someone also taking abemaciclib twice a day, or everolimus once a day, ends up with a schedule that helps to write down for the first few weeks.
Interactions need checking before the first dose. Camizestrant and vepdegestrant both affect heart rhythm, and doctors are told to avoid, where possible, other drugs that prolong the QT interval, plus strong CYP3A inhibitors in the case of vepdegestrant. Several common antibiotics, antifungals and heart drugs fall into those groups, so a full list of medicines, over-the-counter products and supplements should go to both the oncologist and the pharmacist.
Giredestrant, camizestrant, imlunestrant and vepdegestrant can all harm a developing fetus, and effective contraception is advised during treatment for anyone who could become pregnant.
Regular blood work comes with every one of these regimens, since CDK4/6 inhibitors lower blood counts, several of the drugs raise liver enzymes, and everolimus and capivasertib can push blood sugar up. When a result or a symptom crosses a line, the labels for these drugs describe pausing a dose or lowering it before stopping treatment outright, so one bad week doesn’t automatically end a regimen that’s working. Slow heart rate on camizestrant and QTc changes on vepdegestrant are both handled that way first.
What the mutation means for outlook
Trial results for these drugs come in months, and it’s tempting to read them as a life expectancy. Progression-free survival is how long a treatment holds the cancer in check before it grows, not how long a person lives, and when one drug stops working the next one starts. Many people go through several lines of treatment over years.
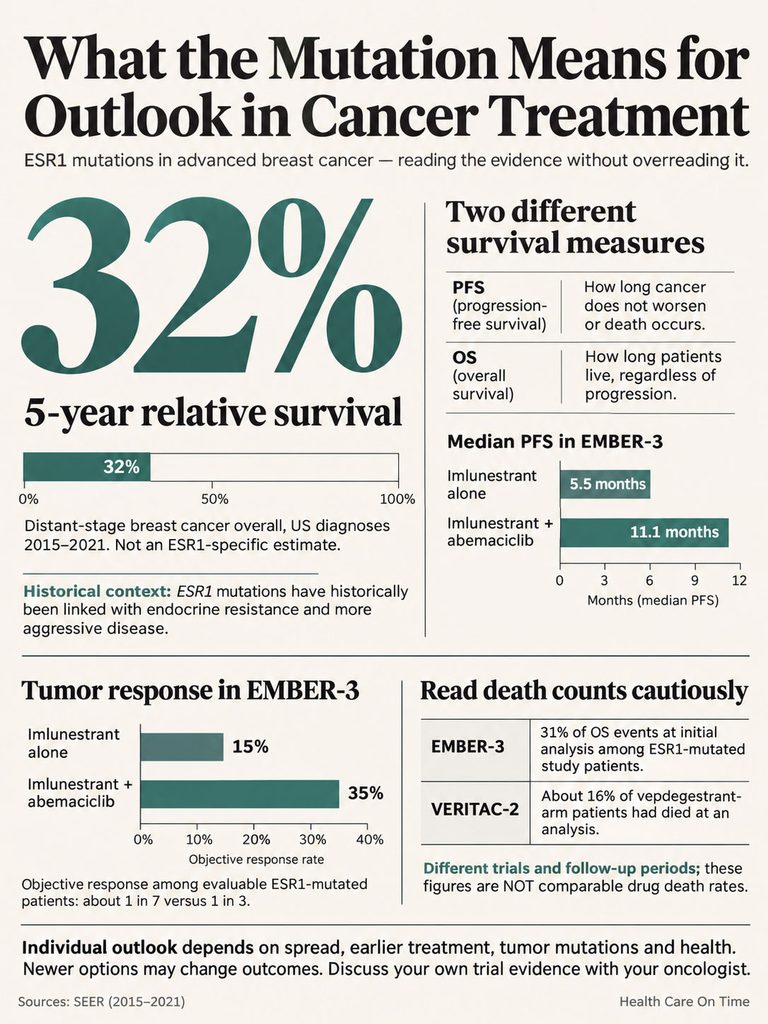
Overall survival, the measure that does count how long people live, was immature for every new drug here at approval. For imlunestrant alone, 31% of people with ESR1 mutations had died by the analysis; for vepdegestrant it was 16%. Those figures reflect how much follow-up existed, not a survival rate, and they can’t be compared with each other.
Response rate measures something narrower again: the share of people whose tumors shrank by a set amount on scans. In these trials it ran from roughly one in seven people on a single pill to about one in three on the abemaciclib combination. A cancer that holds steady without shrinking still counts as controlled, so a low response rate doesn’t mean a drug failed for most people who took it.
Older research did tie ESR1 mutations to tougher disease. In the 2016 liquid biopsy study of more than 500 patients, people carrying the common mutations had more aggressive cancer and shorter overall survival, while the 2019 Cancer review reached a more cautious conclusion, that ESR1 status alone hadn’t been shown to predict a person’s outcome. Both come from the years before ESR1-targeted pills existed, so neither says much about how people do on them.
The broad national figure is a 5-year relative survival of 32% for breast cancer that has already spread to distant organs when it’s first found, from SEER data for women diagnosed from 2015 through 2021. It mixes every subtype together, leaves out cancer that spreads later after early-stage treatment, and predates every drug approved since 2023, including four of the five ESR1-targeted drugs, which arrived in 2025 and 2026. The American Cancer Society is plain that treatments improve over time and these numbers may not reflect them.
It’s reasonable to ask the care team how they read these trial numbers for one specific situation, and how much detail to go into at each visit.
A personal outlook depends on where the cancer has spread, how long earlier treatments worked, other mutations, overall health and response to the next treatment. The oncologist who has seen the scans is the right person to put a number on it, if a number is wanted at all.
Common situations and the questions they raise

Six situations come up often, and each has its own label rules.
| Situation | Options the FDA labels allow | Questions worth asking the oncologist |
| Blood test finds ESR1 while on an aromatase inhibitor plus a CDK4/6 inhibitor, scans stable, at least 6 months on treatment | Camizestrant switch, keeping the CDK4/6 inhibitor (accelerated approval) | How often will heart rate and ECGs be checked, especially with ribociclib or a beta-blocker? What’s known so far about survival? |
| Cancer grew on an aromatase inhibitor plus a CDK4/6 inhibitor, ESR1 found | Elacestrant, imlunestrant, vepdegestrant, imlunestrant plus abemaciclib, giredestrant plus everolimus, or fulvestrant-based therapy | Why a single pill or a combination in this case? Which side effects and food rules come with it? |
| ESR1 and a PIK3CA, AKT1 or PTEN change both found | All ESR1 options above, plus capivasertib with fulvestrant | Which one should come first? How will blood sugar be handled with diabetes? |
| Cancer came back during or after hormone therapy given after surgery | Giredestrant plus everolimus is labeled for this case | Do the other ESR1 pills apply too? How can mouth sores be prevented, and which lung symptoms need a call? |
| ESR1 test negative | Standard hormone combinations; PIK3CA, AKT1 or PTEN-targeted drugs if those are positive | Will the blood test be repeated at the next progression? |
| Premenopausal woman | Giredestrant was studied with ovarian suppression; elacestrant’s label is limited to postmenopausal women and men | What’s the plan for ovarian suppression? Which birth control works during treatment, given that several labels warn of fetal harm? |
Men with ER-positive, HER2-negative breast cancer have the same treatment options.
Questions to ask at the next visit
- Has an ESR1 test been done, and was it a blood test or tissue?
- Which FDA-authorized test was used, and does it match the drug being suggested?
- Were PIK3CA, AKT1 and PTEN checked at the same time?
- Is there a reason to choose a single pill over a combination, or the other way around?
- If this stops working, what comes next?
- Is there a clinical trial nearby that fits this situation?
When to call the oncology team
A slow or irregular heartbeat, dizziness or a near-faint deserves a same-day call on camizestrant, giredestrant or vepdegestrant, and so does a new cough or shortness of breath on everolimus or abemaciclib, which can be early pneumonitis. Diarrhea matters too. Severe diarrhea on capivasertib or abemaciclib can lead to dehydration, and extreme thirst or frequent urination on capivasertib can mean high blood sugar. New flashes of light in vision on camizestrant should be reported at the next contact even though they’re usually mild.

Keeping the clinic’s after-hours number somewhere easy to find helps, because several of these problems can start at night or over a weekend.
Chest pain, fainting or trouble breathing at rest is a 911 call, not a phone message to the clinic.
Frequently Asked Questions
How are ESR1 mutations treated in breast cancer?
With drugs that act on the estrogen receptor directly rather than lowering estrogen. In the US, the FDA-approved options are elacestrant, imlunestrant (alone or with abemaciclib), vepdegestrant, camizestrant with a CDK4/6 inhibitor, and giredestrant with everolimus. Fulvestrant-based combinations remain in use, and capivasertib with fulvestrant is an option when PIK3CA, AKT1 or PTEN changes are also present. The choice depends on earlier treatments, whether scans show growth, other mutations and side effect concerns.
How common are ESR1 mutations in breast cancer?
They show up in about 1% of newly diagnosed tumors and in 10% to 50% of metastatic, hormone-resistant ones. After aromatase inhibitor treatment for metastatic disease, up to half of cancers may develop one.
Is an ESR1 mutation inherited?
No. It develops inside the tumor during hormone therapy and can’t be passed to children.
What is the newest ESR1 breast cancer drug?
Giredestrant (Wilserdly), approved on November 16, 2026, for use with everolimus after earlier hormone therapy. It’s the fifth ESR1-targeted drug the FDA has approved.
Is camizestrant approved?
Yes. It has been since September 4, 2026, under accelerated approval, for use with a CDK4/6 inhibitor when a blood test finds an ESR1 mutation before the cancer grows. More data are expected, and overall survival results weren’t mature at approval.
Is a pill better than fulvestrant injections?
In the one trial that compared them straight on, vepdegestrant held ESR1-mutated cancer back longer than fulvestrant shots (5.0 versus 2.1 months), and elacestrant also beat a control arm that was mostly fulvestrant. Pills spare monthly clinic visits for two buttock injections, though they bring daily food and timing rules. Fulvestrant still has a role. It’s often paired with a CDK4/6 inhibitor or capivasertib.
What is the life expectancy with an ESR1 mutation?
No reliable ESR1-specific figure exists yet. Trials report progression-free survival, which measures how long one treatment works, not how long a person lives, and overall survival data were immature for every new drug at approval. For all distant-stage breast cancer, the American Cancer Society reports a 32% 5-year relative survival, based on women diagnosed from 2015 through 2021, before most of these pills existed. Older studies linked ESR1 mutations to shorter survival, but a 2019 review found the mutation alone hadn’t been shown to predict outcome. The care team can give a far more personal estimate.
Can men get these ESR1 treatments?
Yes. Elacestrant’s label names adult men directly, and in the giredestrant trial men also received a drug to suppress hormone production unless both testicles had been removed.
Does the ESR1 test need to be repeated?
Often. Retesting makes sense at later progressions if earlier results were negative, since the mutation can appear with more time on treatment.
Medical disclaimer: This article is for general information only and doesn’t replace advice from an oncologist or other qualified health professional. Treatment choices for metastatic breast cancer depend on individual test results, earlier treatments and overall health. Don’t start, stop or change any cancer medicine without talking to your care team. Drug approvals and labels change; check current FDA prescribing information. If you have chest pain, fainting or trouble breathing, call 911.
References
- FDA: FDA approves giredestrant in combination with everolimus for ER-positive, HER2-negative, ESR1-mutated breast cancer (Nov 16, 2026)
- FDA: Accelerated approval to camizestrant with a CDK4/6 inhibitor (Sep 4, 2026)
- FDA: Imlunestrant in combination with abemaciclib (Sep 18, 2026)
- FDA: Imlunestrant for ESR1-mutated advanced or metastatic breast cancer (Sep 25, 2025)
- FDA: Vepdegestrant for ESR1-mutated advanced or metastatic breast cancer (May 1, 2026)
- FDA: Veppanu (vepdegestrant) prescribing information, 2026
- FDA: Elacestrant for ESR1-mutated advanced or metastatic breast cancer (Jan 27, 2023)
- FDA: Capivasertib with fulvestrant for breast cancer (Nov 16, 2023)
- Etcamah (camizestrant) prescribing information, Drugs.com
- Faslodex (fulvestrant) prescribing information, Drugs.com
- ASCO: Biomarkers for Systemic Therapy in Metastatic Breast Cancer guideline and ESR1 rapid recommendation update (2023)
- OncLive: FDA ODAC votes against clinical benefit of switching to camizestrant (Apr 30, 2026)
- Dustin D, Gu G, Fuqua SAW. ESR1 Mutations in Breast Cancer. Cancer. 2019;125(21):3714-3728
- College of American Pathologists: ESR1 Mutations in Hormone Receptor-Positive Breast Cancer (updated Oct 2026)
- Living Beyond Breast Cancer: ESR1 Mutation Testing (reviewed Jul 2026)
- Memorial Sloan Kettering: MSK Discovery of ESR1 Gene Mutation Leads to Approval of Breast Cancer Drug Elacestrant (May 2023)
- American Cancer Society: Survival Rates for Breast Cancer (revised Jul 23, 2026)