Most people who get migraines can take hormone replacement therapy (HRT), and that includes many people who have migraine with aura. Migraine mainly changes which form of HRT makes sense, what dose to start at, and how closely the first few months get watched.
Table of Contents
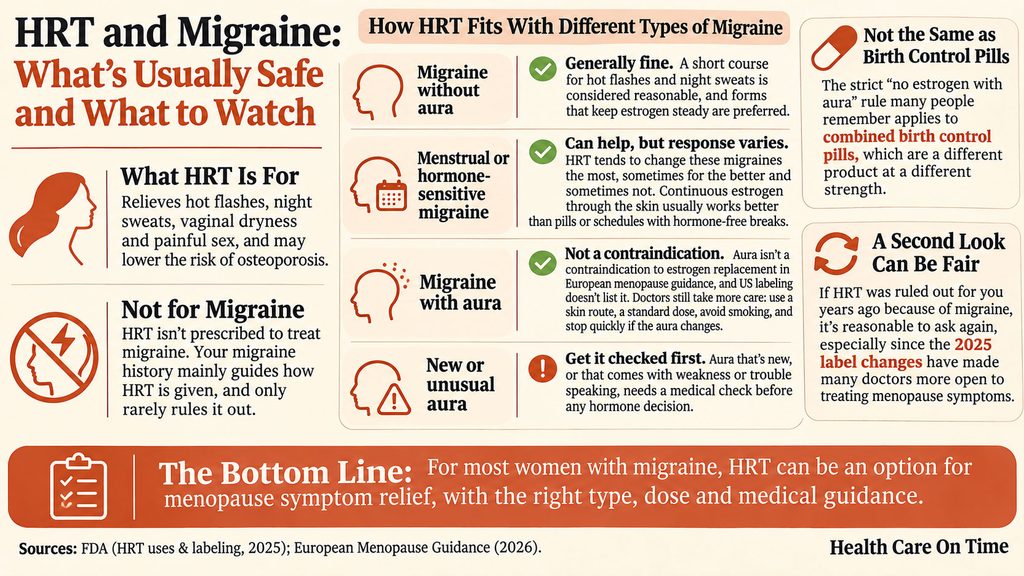
Quick answer: Yes, for most people. Migraine, with or without aura, does not appear among the contraindications on FDA estrogen labeling. With aura, stroke risk is the concern, and the form of estrogen matters a lot. In a study of more than 15,000 strokes, standard-dose estrogen patches showed no measurable rise in stroke risk, while estrogen pills and higher-dose patches did. Skin patches, gels or sprays are the usual first choice.
The Answer Depends on Your Kind of Migraine
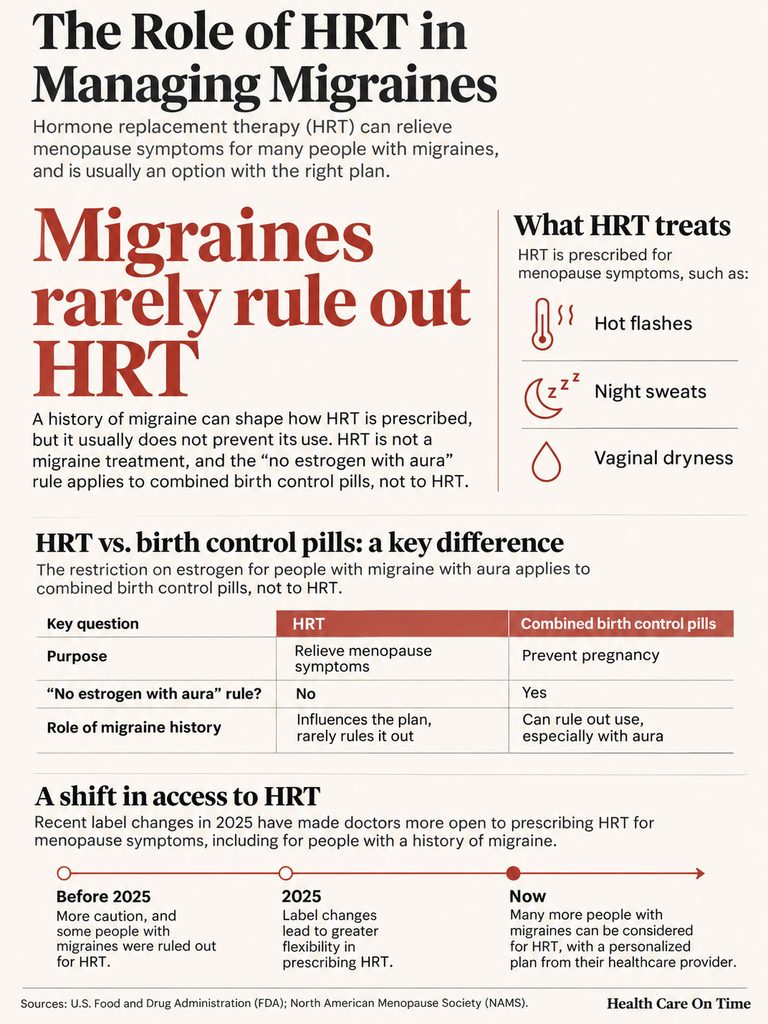
HRT is prescribed for hot flashes, night sweats, vaginal dryness and painful sex, and it may lower the chance of osteoporosis. Nobody prescribes it to treat migraine. If you need it for those symptoms, your migraine history mostly decides how HRT is given, and only rarely rules it out.
- Migraine without aura. Generally fine. A short course for hot flashes and night sweats is considered reasonable, and forms that keep estrogen steady are preferred, since a falling estrogen level is a well-known trigger.
- Menstrual or hormone-sensitive migraine. HRT tends to change these migraines the most, sometimes for the better and sometimes not. Continuous estrogen through the skin usually works better than pills or schedules with hormone-free breaks.
- Migraine with aura. Aura isn’t a contraindication to estrogen replacement in European menopause guidance, and US labeling doesn’t list it. Doctors still take more care: a skin route, a standard dose, no smoking, and a quick stop if the aura changes.
- New or unusual aura. Aura that’s new, or that comes with weakness or trouble speaking, needs a medical check before any hormone decision.
The strict “no estrogen with aura” rule many people remember belongs to combined birth control pills, which are a different product at a different strength.
If a doctor ruled out HRT for you years ago because of migraine, it’s fair to ask again, especially since the 2025 label changes have made many doctors more open to treating menopause symptoms in general.
Why Migraines Often Flare Before Menopause
Estrogen and migraine are tied together in a fairly specific way: a level that drops quickly tends to set off attacks, and a level that holds steady tends to calm them. Pregnancy shows the steady side, because estrogen climbs early and stays high, and many women get fewer migraines while pregnant. Menstrual migraine shows the other side. It follows the fall in estrogen before a period (progesterone’s fall doesn’t seem to matter), typically starting about two days before bleeding and sometimes lasting into the third day.
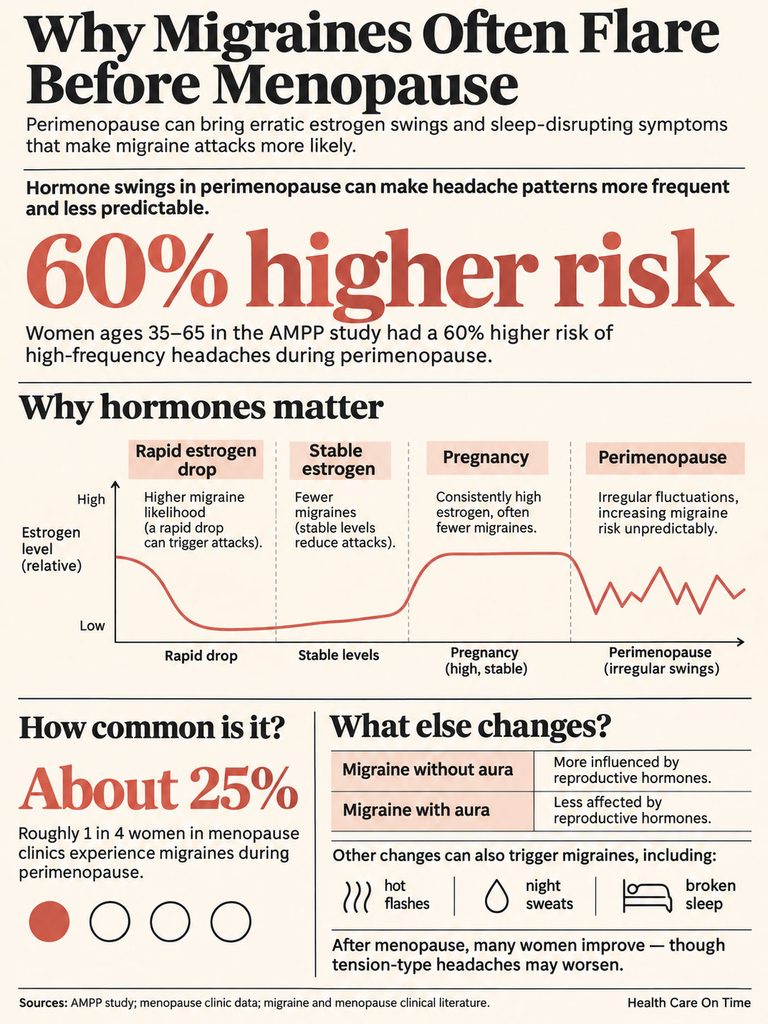
In perimenopause, periods turn irregular and estrogen swings without a clear rhythm, so the trigger can arrive at any point in the month. This stage can start around 10 years before the last period, and menopause is confirmed only after 12 months without one.
By this stage of life, women already get severe headache or migraine about twice as often as men. About a quarter of women seen in menopause clinics have migraine during perimenopause, and headache days tend to pile up as the transition goes on. Among 3,664 women aged 35 to 65 with migraine in the AMPP study, those in perimenopause had a 60% higher risk of high-frequency headache than women whose cycles were still regular, with high-frequency meaning more than 10 headache days a month. The rise showed up most in late perimenopause, when periods start getting skipped and estrogen runs low, although overuse of pain medicine may have played a part too.
Women with menstrually related migraine also seem more prone to hot flashes and night sweats, and broken sleep is a migraine trigger in its own right. When HRT calms the night sweats and you sleep through the night again, your migraines can ease along with it.
After menopause, many women get relief; in one mixed group of perimenopausal and postmenopausal women, almost two-thirds improved. Migraine with aura seems less tied to reproductive hormones than migraine without aura.
Tension-type headaches, on the other hand, sometimes get worse once periods stop, so a new kind of headache after menopause may have a different cause and deserves its own check. Surgical menopause is another exception: removing the ovaries drops hormone levels all at once, which often makes migraine worse at first.
Migraine With Aura and Stroke
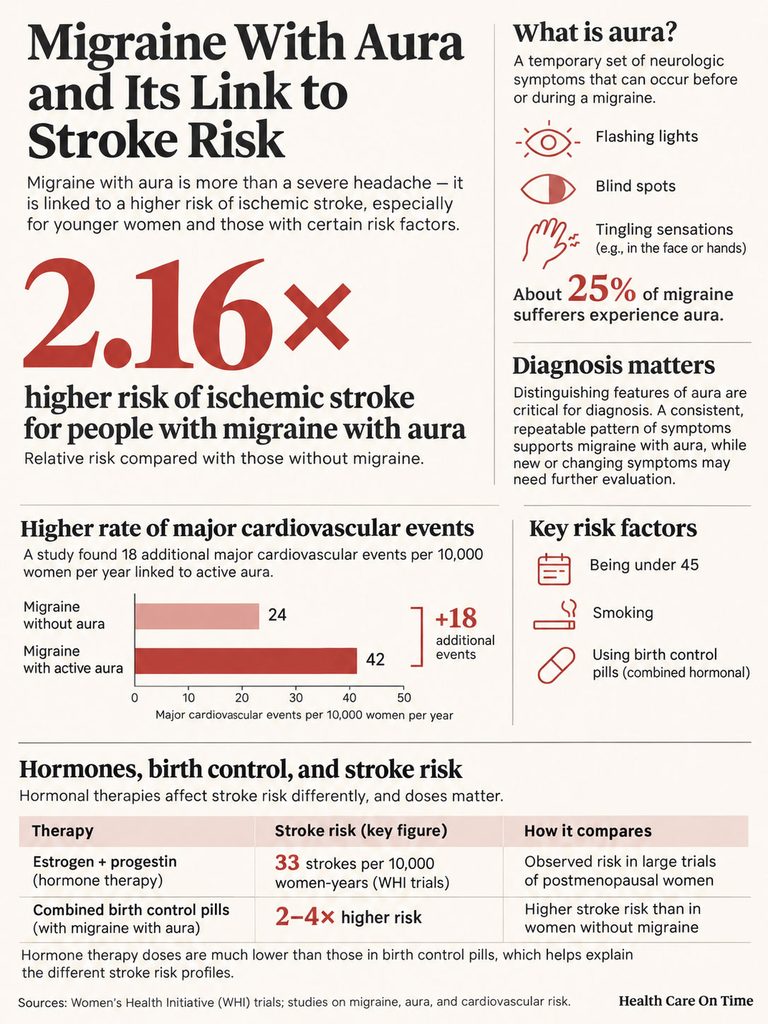
Aura is a set of nervous system symptoms that come before or during the headache. Most often that means flashing lights, blind spots or zigzag lines, and tingling in the hand or face; less often, trouble speaking or weakness on one side. About a quarter of people with migraine get aura, and some get aura with very little headache afterward, so a person can live with migraine with aura for years before anyone names it.
Doctors care a lot about the details. If you’ve had the same zigzag lines since your twenties, lasting 5 to 10 minutes and looking the same every time, that’s treated very differently from aura that is new, lasts longer than usual, changes character, or affects speech or strength. When you aren’t sure whether what you get counts as aura, describe one episode in plain terms at the appointment: what you saw or felt, which side, how long it lasted, and when the headache began.
Aura matters for HRT because it’s linked to ischemic stroke, the kind caused by a blocked blood vessel. Pooled observational data put the relative risk at 2.16 for migraine with aura compared with no migraine, while migraine without aura came out at 1.23, a difference small enough that it could be chance. Being under 45, smoking and taking birth control pills each pushed the risk higher. A US study of 27,840 women aged 45 and older, followed for about 10 years, found a hazard ratio of 1.91 for ischemic stroke with active aura.
In absolute terms, aura accounted for 18 additional major cardiovascular events, such as heart attacks and strokes, per 10,000 women per year. For any one woman, that risk is small.
Estrogen carries its own stroke signal, measured mainly with pills. The Women’s Health Initiative (WHI) trials of estrogen tablets found 33 strokes per 10,000 women-years with estrogen plus progestin, against 25 on placebo. Women aged 50 to 59 taking estrogen alone didn’t follow that pattern, with 18 strokes against 21. Oddly, these pill-trial numbers are printed in the Warnings section of estradiol patch labeling too, even though patches behave differently.
No trial has studied HRT in women with migraine with aura as a group, so advice rests on what’s known about each risk separately and on how much the route of estrogen changes things.
| Finding | Number | Source |
| US adults with severe headache or migraine in the past 3 months | Women 20.1%, men 10.6% | CDC, National Health Interview Survey 2018 |
| Same measure, women aged 18 to 44 | 25.5% | CDC, National Health Interview Survey 2018 |
| High-frequency headache in perimenopause vs regular cycles | 60% higher risk | AMPP study, Headache 2016 (3,664 women) |
| Ischemic stroke, migraine with aura vs no migraine | Relative risk 2.16 | Meta-analysis, The BMJ 2009 |
| Ischemic stroke, migraine without aura | Relative risk 1.23 (not significant) | Meta-analysis, The BMJ 2009 |
| Ischemic stroke, active aura, women 45 and older | Hazard ratio 1.91; 18 extra major cardiovascular events per 10,000 women per year | Women’s Health Study, JAMA 2006 |
| Stroke with oral estrogen plus progestin vs placebo | 33 vs 25 per 10,000 women-years | WHI data in estradiol patch labeling |
| Stroke with combined birth control pills in women with migraine | 2 to 4 times higher | CDC systematic review, Contraception 2016 |
Why the Birth Control Pill Rule Doesn’t Carry Over
The firm advice against combined pills with aura comes from contraception research. A CDC systematic review found fair-to-poor quality evidence of a two- to fourfold higher stroke risk in women with migraine who take combined pills, most likely because of the estrogen in them.
Menopause hormone therapy usually uses estradiol, the same estrogen the ovaries make, at a dose meant to replace what’s been lost, whereas a birth control pill uses a synthetic estrogen strong enough to stop ovulation. Shutting the ovaries down with estradiol alone takes patches delivering 200 mcg twice weekly, far above usual menopause doses, so stroke figures from the pill don’t transfer to HRT.
Patch, Gel, Pill or Vaginal Estrogen
If you have migraine, and especially aura, the route may matter more than any other choice. Two separate things are at stake: how steady the hormone level stays, which affects the migraines, and how much the estrogen affects clotting, which affects stroke.
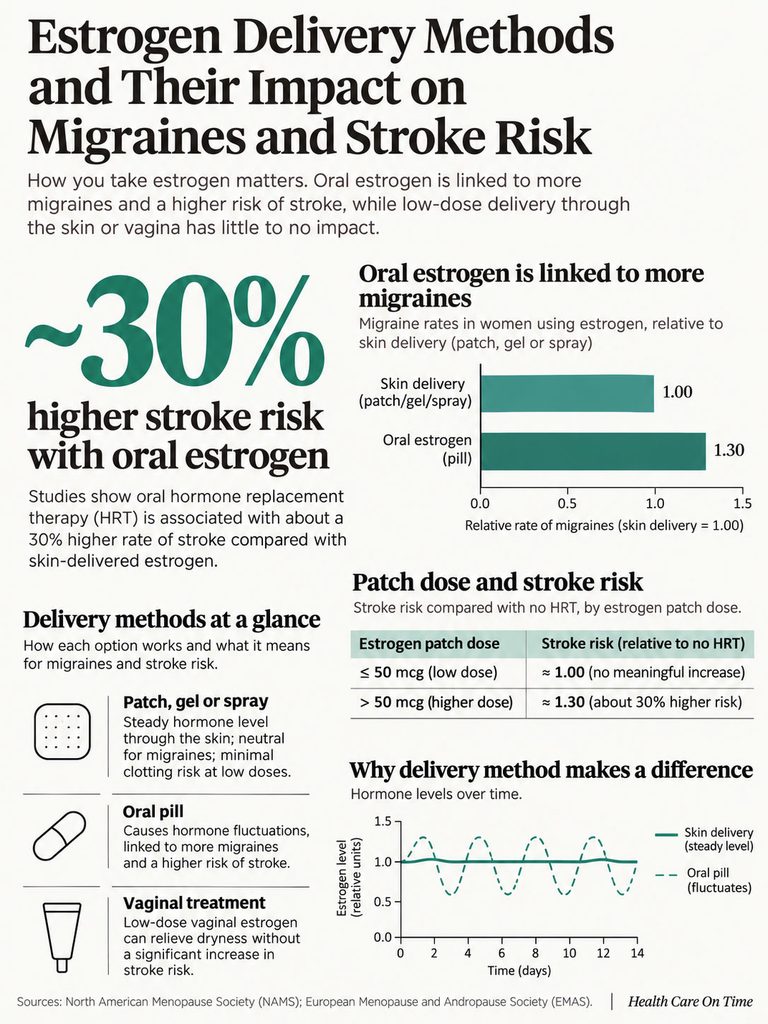
Patches, gels and sprays all deliver estrogen through the skin in a small, steady stream. A pill delivers its dose all at once, so levels rise and fall through the day, which is the kind of swing that sets off attacks. Small studies have linked oral estrogen to more migraine, while estrogen through the skin looked neutral. Low doses of natural estrogen given through the skin also have little effect on clotting, the main reason menopause specialists in Europe prefer non-oral routes for women with migraine.
For stroke, route and dose seem to work together. In a 2010 analysis of UK health records covering 15,710 women aged 50 to 79 who had a stroke, oral HRT went with a modestly higher stroke rate and patches of 50 mcg or less did not, while stronger patches did. The exact ratios are in the table below.
That study was observational and included women with and without migraine, so it can’t answer the aura question on its own.
| HRT form | How estrogen enters | Hormone levels | Stroke data | Usual fit with migraine with aura |
| Estrogen pill | Swallowed | Rise and fall with each dose | Rate ratio 1.28 (UK study, 15,710 strokes); WHI oral estrogen plus progestin 33 vs 25 per 10,000 women-years | Usually avoided when a skin route is possible |
| Estrogen patch, 50 mcg or less | Through the skin | Steady | Rate ratio 0.81, not significantly different from no HRT | Usual first choice |
| Estrogen patch, above 50 mcg | Through the skin | Steady, higher level | Rate ratio 1.89 | Weigh against better migraine control at 100 mcg |
| Estrogen gel or spray | Through the skin | Steady | Not analyzed separately in the UK study; grouped with non-oral routes in guidance | Reasonable alternative to a patch |
| Vaginal cream, tablet, insert or ring | Mostly local | Low; treats vaginal symptoms | Not part of the stroke studies above | Can be used for dryness and painful sex |
| Combined birth control pill | Swallowed, synthetic estrogen | Drops during placebo days | 2 to 4 times higher stroke risk in women with migraine | Not recommended with aura |
Low-dose vaginal creams, tablets, inserts and rings treat dryness and painful sex right where the symptoms are, and they’re commonly used even with aura, though some women notice a short rise in migraine at the start that usually settles with continued use.
Dose and Schedule
Giving estrogen continuously, without breaks, avoids the drop behind withdrawal migraine. European advice also favors the lowest dose that controls symptoms, even after the FDA took the “lowest dose for the shortest time” wording out of the US boxed warning in 2025.
Dose can pull the other way, too. In one estrogen-only comparison, a 100 mcg patch prevented migraine better than a 50 mcg patch, and in a 2024 case report, a woman whose patch dose was lowered step by step got more frequent attacks until the dose went back up. The UK stroke data, though, put patches above 50 mcg in a higher-risk group. With aura, where to settle depends on your blood pressure, smoking history and migraine pattern.
If HRT makes headaches worse, the usual moves are a lower dose, a different form, or stopping.
The Progestogen Half of the Plan
If you still have a uterus, you need a progestogen along with estrogen, because estrogen alone raises the risk of endometrial cancer; that warning is the one part of the boxed warning the FDA kept for systemic estrogen-only products. Some women do fine on estrogen and react to the progestogen instead, so this half of the plan deserves as much thought.

The schedule seems to matter most. A randomized study found cyclical HRT, where progestogen is added for part of each month, worse for migraine than continuous combined HRT, where both hormones are taken daily, and women who react badly to progestogens tend to do better on the continuous kind. Cyclical regimens are still common within about a year of the last period, since starting continuous treatment too early can cause breakthrough bleeding.
US options include combination pills and patches, progestogen-alone pills such as oral micronized progesterone, and a levonorgestrel-releasing intrauterine device (LNG-IUD). No study has compared which one is gentlest on migraine.
Many specialists like the LNG-IUD during the menopausal transition because it releases progestin locally and keeps blood levels low. Contraception guidelines see no problem with aura either: the CDC’s 2024 eligibility criteria put it in category 1, meaning no restriction, for migraine with or without aura. In the US, though, the LNG-IUD is approved for birth control and heavy periods, so using it to protect the uterus during HRT is off-label. Plenty of gynecologists prescribe it that way anyway; just know that’s what’s happening.
Still Having Periods: HRT or Birth Control?
In early perimenopause, while periods still come, the practical choice is sometimes between HRT and a hormonal birth control method, since pregnancy is still possible. Steadying hormone levels comes first, and both contraceptive pills and estrogen patches can do it.

For women without aura, continuous combined hormonal contraception, taken without the usual placebo week, can prevent menstrual migraine early in the transition by removing the monthly estrogen drop. If you’re already on the pill and the headaches land in the placebo week, there are several ways around it: packs with fewer placebo days, extended-cycle packs taken for 84 days before a seven-day break, continuous packs taken for a full year, a pill with less estrogen, or a low-dose estrogen pill or patch during the placebo days.
With aura, estrogen-containing birth control is usually avoided, because it stacks stroke risk on top of the aura itself, and smoking makes that combination worse. That leaves estrogen-free methods: the progestin-only pill norethindrone, or an LNG-IUD, which can cover birth control now and the progestogen part of an HRT plan later. Once periods have stopped for good and birth control is no longer needed, most women move from contraception to HRT.
Matching the Plan to Your Situation
Most real cases look like one of these rows, though one detail in your history can move you to another.

| Your situation | What current guidance generally supports | A question worth asking |
| Migraine without aura plus bothersome hot flashes | HRT is reasonable; skin route preferred for steadier levels | Should we start with a patch or a gel instead of a pill? |
| Menstrual migraine that worsened in perimenopause | Continuous estrogen through the skin, no hormone-free gaps | Can the progestogen be taken every day so there’s no monthly drop? |
| Lifelong, simple visual aura lasting 5 to 10 minutes | Aura is not a contraindication; standard-dose patch or gel | Do blood pressure or clotting history change the plan? |
| New aura, or aura that changes pattern | Medical check first; stop HRT immediately if aura changes while on it | Does a neurologist need to see this before hormones? |
| Migraine with aura and you smoke | Aura, smoking and estrogen each add stroke risk | What help is available to quit before starting? |
| Past stroke, heart attack, blood clot or clotting disorder | Listed as contraindications on estradiol labeling | Which nonhormone treatments fit instead? |
| Migraines worse after starting HRT | Lower dose, switch form, or stop | Which change should come first? |
| Still having periods and need birth control | LNG-IUD rated category 1 even with aura; combined pill avoided with aura | Can an IUD also protect the uterus later (off-label in the US)? |
A common real-world case is night sweats, wrecked sleep, and migraine without aura that lands the day before each period, and a continuous patch or gel often suits it well. Add a short zigzag aura that has been around since college plus a smoking habit, and HRT may still be possible, but the plan starts with quitting and a blood pressure check, and any change in the aura ends the trial.
What the FDA Changed
On November 10, 2025, the FDA announced it would remove several boxed warnings from menopausal hormone therapy. Drug makers were asked to take language on cardiovascular disease, breast cancer and probable dementia out of the boxed warning, along with the advice to use the lowest dose for the shortest time. The endometrial cancer boxed warning stays for systemic estrogen-only products, and labels are to suggest starting systemic therapy in women under 60 or within 10 years of menopause onset.

Cardiovascular disease and breast cancer still appear in the Warnings and Precautions section, so stroke remains on the label, just not in the black box. By October 2026 several companies had revised their labels, and the FDA was openly stating that millions of women had avoided hormone therapy since the early 2000s out of fear of cancer and heart disease.
None of this mentions migraine. For a woman with aura, the stroke question hasn’t changed, and the route and dose choices above still do most of the work. Doctors are more willing than a few years ago to treat symptoms in women under 60, a long way from the mood after the first WHI results came out, while for women past 60 the newer labeling points to a narrower window and a closer look at stroke risk.
When Hormones Are the Wrong Choice
Some conditions rule out systemic estrogen whatever your migraine type. Estradiol patch labeling lists:

- Undiagnosed abnormal genital bleeding
- Breast cancer, a history of it, or another estrogen-dependent cancer
- A current or past blood clot in a leg vein or lung
- A current or past stroke or heart attack
- Liver disease or impaired liver function
- Protein C, protein S or antithrombin deficiency, or another known clotting disorder
- A past allergic reaction to the product
Smoking doesn’t appear there, yet with aura it tilts the stroke math enough that anyone who smokes should go over it with a clinician before starting.
If hormones are ruled out, hot flashes can still be treated, since the FDA has approved three nonhormone medicines for menopause symptoms. For migraine prevention, daily options include beta blockers, antiseizure medicines, calcium channel blockers, antidepressants and magnesium, with monthly CGRP antibody injections when those haven’t worked, and attacks themselves are usually treated with anti-inflammatories, triptans or gepants. Several migraine preventives also ease perimenopausal symptoms, which makes them a sensible first pick for some women.
After You Start
HRT may make headaches better, worse or no different, and there’s no reliable way to know which before trying. The full benefit for hot flashes can take about three months, so a rough first few weeks doesn’t always mean the plan has failed.

A simple migraine diary for those months is worth the small effort. Write down each attack, whether aura came with it, how long it lasted, how bad it was, and what seemed to set it off, along with hot flashes and how you slept. Warning signs belong there too; about 60% of people with migraine get them hours before the pain, things like mood changes, food cravings, neck stiffness or yawning. At the follow-up visit, a few weeks of real entries make dose changes far easier than memory does.
Any change in your usual aura means stopping HRT and calling your doctor, whether the aura lasts longer, looks different, shows up for the first time, or brings new symptoms.
Women in the WHI whose migraines worsened on hormone therapy had somewhat higher odds of ischemic stroke (odds ratio 1.3) than never or past users, in early data presented at the International Stroke Conference in 2016. Those results haven’t appeared as a full paper, so they’re a reason for caution rather than proof.
Get emergency care right away, by calling 911, for sudden weakness or numbness on one side, trouble speaking or understanding speech, or vision loss, especially if it happens without your usual headache or is new for you.
Questions to Bring to Your Appointment
Appointments go fast, so it helps to walk in with these written down:

- Is this aura the common harmless kind, or should a neurologist look at it before hormones start?
- Would a patch or gel be safer than a pill in this case, and what’s a sensible starting dose?
- With the uterus still in place, which progestogen makes the most sense: pills, a combination patch or an IUD?
- If the migraines get worse in the first few weeks, what do we try first?
- Do blood clots in the family change anything?
- Could a nonhormone medicine handle the hot flashes instead?
Frequently Asked Questions
Is it safe to take HRT if you get migraines?
In most cases it is. Migraine isn’t listed as a contraindication on FDA estrogen labeling, and aura isn’t treated as one in European menopause guidance. Estrogen through the skin at a standard dose is the typical starting point.
What disqualifies you from HRT?
The main exclusions are undiagnosed abnormal vaginal bleeding, breast cancer or another estrogen-dependent cancer, a current or past blood clot, stroke or heart attack, liver disease, inherited clotting disorders such as protein C, protein S or antithrombin deficiency, and allergy to the product. Migraine itself isn’t one of them. Smoking, high blood pressure and an aura that has recently changed aren’t formal exclusions either, but each one makes a careful doctor slow down and look harder at stroke risk before writing a prescription.
What is the best HRT for migraine sufferers?
Estrogen through the skin, as a patch, gel or spray, is the most common pick, because it keeps levels steady and has been linked to less migraine than pills, and in a large UK study, patches of 50 mcg or less showed no significant rise in stroke risk. Continuous dosing avoids withdrawal headaches, and a continuous combined schedule tends to suit migraine better than a cyclical one. For the progestogen, choices include micronized progesterone pills, combination patches and an LNG-IUD, which is off-label for this use in the US.
Are migraines caused by low estrogen?
Low estrogen on its own isn’t the usual culprit. The trigger is mostly a drop or swing, which is why attacks cluster before periods and during perimenopause, and why steady levels, even low ones after menopause, bring relief for many women.
Can HRT cure migraines?
No. HRT isn’t recommended as a migraine treatment. Some women improve because hot flashes and sleep improve, while others get worse, so migraine still needs its own treatment plan.
Do estrogen patches cause headaches?
They can, though less often than pills. If headaches start or worsen on a patch, a doctor may lower the dose, switch to a gel or spray, or stop it.
Can you take hormone replacement with migraines after 60?
Sometimes, but the bar is higher. The Menopause Society’s view is that benefits outweigh risks for most healthy women with symptoms who are under 60 or within 10 years of menopause, and the newer FDA labeling points to the same window. Past that point, stroke and clot risks get more weight, particularly with aura, so a skin route and a blood pressure check become central.
Is vaginal estrogen OK with migraine with aura?
Low-dose vaginal estrogen is generally fine, since it works mainly where it’s applied and is commonly used for dryness and painful sex. A brief rise in migraine at the start usually settles.
Does a hysterectomy help hormone-related migraine?
No. A hysterectomy isn’t a migraine treatment, and if the ovaries come out too, the sudden hormone drop can make migraine worse at first.
Medical disclaimer: This article is general health information for adults in the United States. It isn’t medical advice and doesn’t replace a visit with a licensed clinician who knows your history. Decisions about hormone therapy, especially with migraine with aura, should be made with your doctor. If you have sudden weakness, trouble speaking or vision loss, call 911.
References
- FDA: Hormone Replacement Therapies Can Help Women With Bothersome Menopausal Symptoms (consumer update, 2026)
- RAPS: FDA to remove boxed warnings from hormone therapies (November 2025)
- Estradiol Transdermal System prescribing information: contraindications and warnings
- Mayo Clinic: Headaches and hormones: What’s the connection?
- American Migraine Foundation: Migraine and Women’s Health
- Schürks M, et al. Migraine and cardiovascular disease: systematic review and meta-analysis. BMJ 2009;339:b3914
- Kurth T, et al. Migraine, headache, and the risk of cardiovascular disease in women. JAMA 2006;296(3):283-291
- Renoux C, et al. Transdermal and oral hormone replacement therapy and the risk of stroke. BMJ 2010;340:c2519
- The Menopause Society: 2022 Hormone Therapy Position Statement release
- EMAS: Menopause Essentials 2026, Migraine
- Australasian Menopause Society: Migraine headaches, menopause and MHT/HRT
- MacGregor EA, Briggs P. Hormone replacement therapy (HRT) in perimenopausal women with migraine. Post Reproductive Health 2024
- University of Cincinnati: Migraines worsen as women approach menopause (AMPP study, Headache 2016)
- CDC MMWR QuickStats: Severe headache or migraine by sex and age, NHIS 2018
- Tepper NK, et al. Safety of hormonal contraceptives among women with migraine: a systematic review. Contraception 2016
- CDC: U.S. Medical Eligibility Criteria for Contraceptive Use, 2024, appendix tables
- Jensen JT. Endometrial protection: which progestogen is best? Contraceptive Technology Update
- Healio: Worsening migraines with hormone replacement linked to increased stroke risk in women (International Stroke Conference 2016 abstract)
- National Migraine Centre: Migraine, menopause and HRT