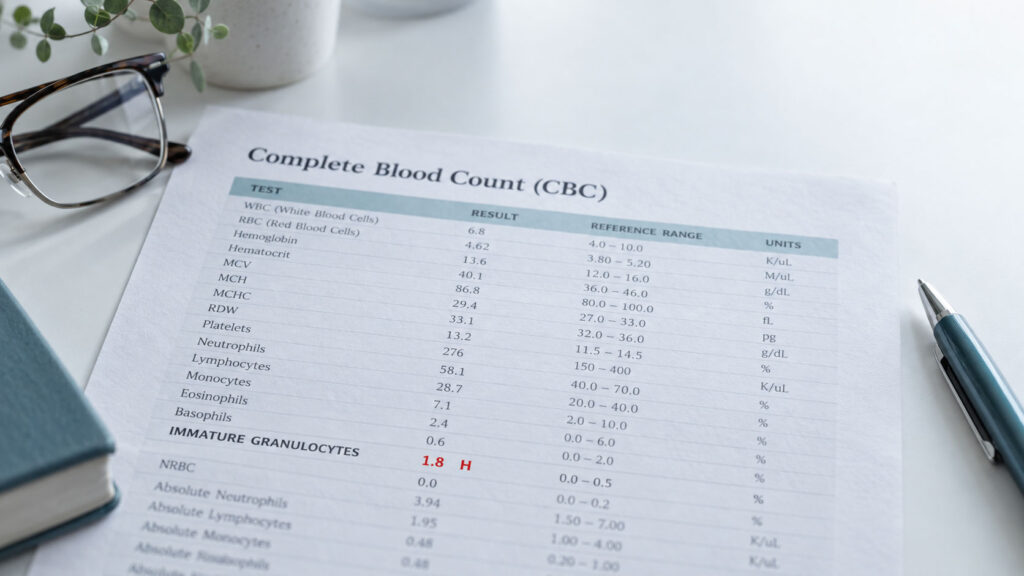
Your complete blood count came back with one line flagged in red, and the words next to it were ones you had never seen before. Immature granulocytes. High. Somewhere between reading that line and closing the patient portal, most people have already typed “leukemia” into a search bar.
Table of Contents
Here is what rarely makes it onto the lab report itself: the reference range your result was measured against may not be the right one for you.
Quick Answer: High immature granulocytes (IG) means your bone marrow released young white blood cells into your bloodstream before they finished maturing. In adults over age 10, the published upper limit is about 0.90% of white cells, or 70 cells per microliter. Infection, inflammation, surgery, steroids, and pregnancy account for the large majority of elevations. Blood cancers are a rare cause. Most mild elevations resolve on their own and are confirmed with a repeat blood count.
The six reasons immature granulocytes most often turn up high, roughly in order of how frequently they show up:
- Bacterial or viral infection anywhere in the body
- Inflammation from injury, autoimmune flare, or recent illness
- Physical stress such as surgery, trauma, burns, or labor and delivery
- Medications, especially corticosteroids and growth factor injections
- Pregnancy, particularly the second and third trimesters
- Bone marrow and blood disorders, which sit at the end of this list for good reason
At a Glance
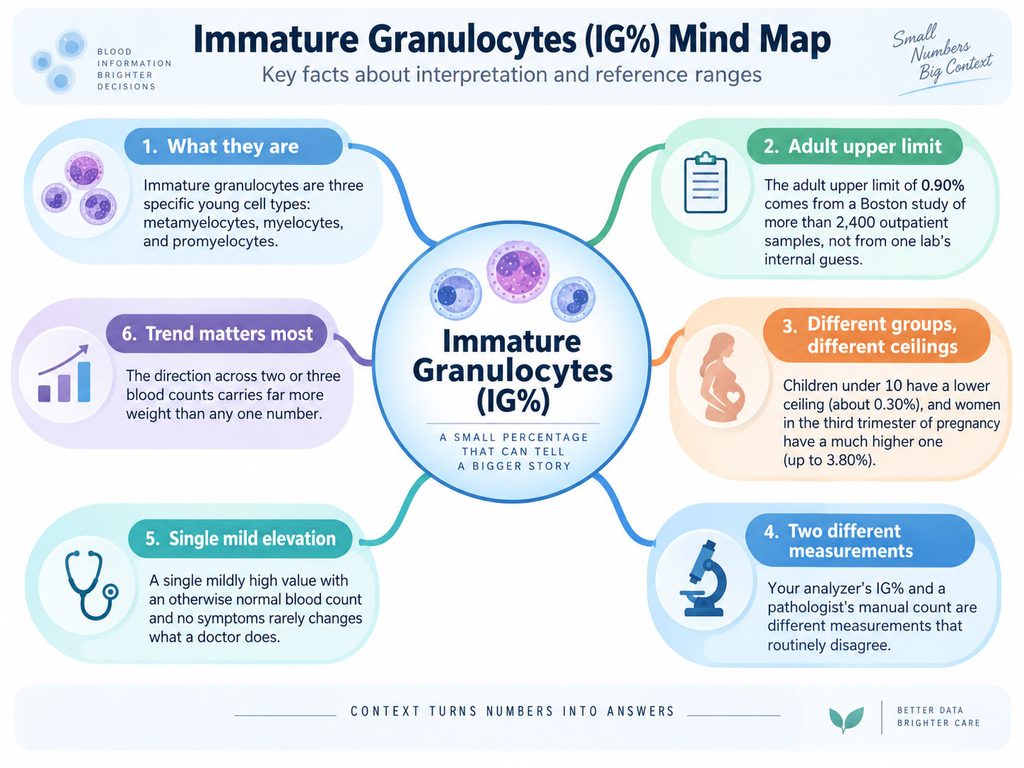
- Immature granulocytes are three specific young cell types: metamyelocytes, myelocytes, and promyelocytes.
- The adult upper limit of 0.90% comes from a Boston study of more than 2,400 outpatient samples, not from one lab’s internal guess.
- Children under 10 have a lower ceiling (about 0.30%), and women in the third trimester of pregnancy have a much higher one (up to 3.80%).
- Your analyzer’s IG% and a pathologist’s manual count are different measurements that routinely disagree.
- A single mildly high value with an otherwise normal blood count and no symptoms rarely changes what a doctor does.
- The direction across two or three blood counts carries far more weight than any one number.
What Immature Granulocytes Actually Are
Granulocytes are the workhorse white blood cells. Neutrophils, eosinophils, and basophils all belong to this family, and neutrophils handle most of the fight against bacteria.

They are built in your bone marrow along a production line. A stem cell becomes a myeloblast, then a promyelocyte, then a myelocyte, then a metamyelocyte, then a band cell, then a fully mature segmented neutrophil.
The Three Cells the Machine Is Counting
When a modern hematology analyzer reports “immature granulocytes,” it is counting three of those stages: promyelocytes, myelocytes, and metamyelocytes. Band cells are deliberately excluded.
That distinction matters because older articles and many chart notes still talk about “bands” and “left shift.” Band counts and IG counts are related but not interchangeable, and they come from completely different methods.
Our medical reviewers field this confusion constantly from patients who compared an old paper report to a new electronic one and assumed the lab had changed something. The lab did change something. It moved from a person counting cells by eye to a machine classifying them by optical and fluorescence signals.
Why They Normally Stay Put
In a healthy adult, the marrow runs like a warehouse with a strict shipping policy. Nothing leaves until it is finished.
That policy loosens under demand. When infection, tissue injury, or inflammatory signaling tells the marrow to send reinforcements right now, partially finished cells get pushed into circulation.
Clinicians have called this a “left shift” for more than a century, because on handwritten differential counts the immature forms sat in the left-hand columns. An elevated IG is a demand signal, not a defect signal. The useful question is what created the demand.
IG% and IG Absolute, and Why They Disagree
Your report may carry one value or two. IG% is the share of your white cells that are immature. IG absolute (often printed as IG# or “Immature Grans (Abs)”) is the actual count per microliter or per liter.
The absolute count is the steadier of the two. Percentages have a denominator, and denominators move.
The Percentage Trap
Suppose your total white cell count drops because a viral illness knocked down your lymphocytes. The number of immature granulocytes in your blood has not changed at all, but the total shrank, so the percentage climbs and the report flags it.
That single mechanism explains a large share of confusing results. Reading both values together, when both are printed, usually settles it in seconds.
What Counts as “High,” and Why Your Lab’s Flag May Be Wrong
This is where most consumer health content stops short. Page after page says immature granulocytes are “normally absent or very low” without printing a single number.
The numbers exist. They are just not on the pages that rank first.
The Adult and Pediatric Limits
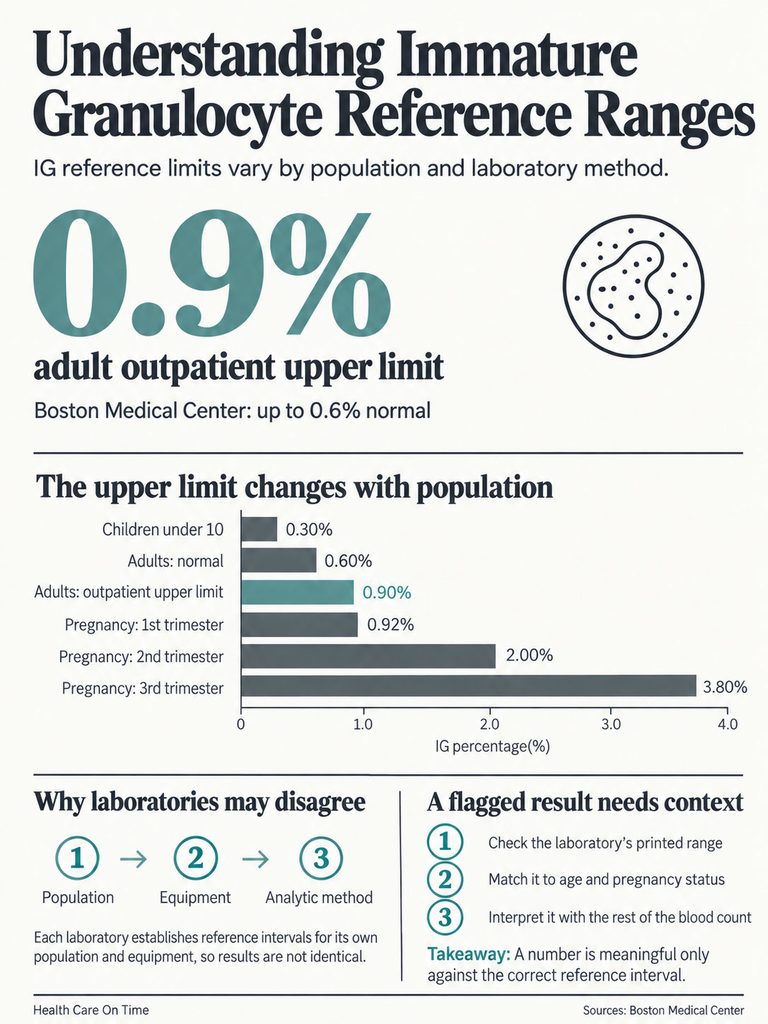
The most relevant dataset for people who are not in a hospital bed comes from Boston Medical Center, where researchers analyzed more than 2,400 outpatient samples and built age-stratified reference ranges. They found no difference between men and women.
For routine outpatient use, they recommended an upper limit of 0.30% or 40 cells per microliter for children aged 10 and under, and 0.90% or 70 cells per microliter for everyone older than 10.
A separate healthy-donor study set the reference range at 0 to 0.06 × 10⁹/L and 0 to 0.63%, and an earlier blood donor study on Sysmex equipment landed at almost exactly 0.6%.
So a workable answer for a healthy adult looks like this. Anything up to about 0.6% is squarely normal. Up to about 0.9% remains inside published limits. Above that, meaning depends entirely on context.
Pregnancy Changes the Whole Scale
Competitor pages hand pregnant readers one sentence about mild increases and move on. The real data is far more specific and far more reassuring.
A study of 1,372 healthy pregnant women built separate reference intervals for each trimester. The upper limits climbed steadily: 0.92% in the first trimester, 2.00% in the second, and 3.80% in the third.
Read that last figure again. A third-trimester IG of 3.5% sits inside the normal range for pregnancy, yet nearly every analyzer in the United States will print it as high, because the flag is set against a non-pregnant adult interval.
The same study found the median value in healthy pregnant women (0.5%) ran more than double the median in healthy non-pregnant women (0.2%). The value rose with gestational age but showed no relationship to maternal age.
Two honest limits belong here. That cohort was Chinese and ran on a single Sysmex XE-5000 analyzer, so the exact cut points may not transfer perfectly to a US laboratory using different equipment. And the intervals describe uncomplicated pregnancies, not pregnancies with infection, preeclampsia, or chorioamnionitis.
Patients booking prenatal blood panels through HealthCareOnTime regularly ask why a value their obstetrician waved off was printed in bold red. This is the reason.
Why Two Labs Give You Two Different Numbers
Reference intervals are not universal constants. Each laboratory is expected to establish or verify its own, using its own analyzer and its own local population, following Clinical and Laboratory Standards Institute methodology.
Analyzer platforms also differ in how they identify immature cells. Some use fluorescence flow cytometry in a dedicated channel, others rely on different optical scatter approaches. The same tube of blood run on two brands can return two different IG values.
That is not carelessness. It is exactly why the reference range printed beside your result carries more authority than any range you find online, this article included.
| Group | IG% upper limit | IG absolute upper limit | Source | What a flagged value usually reflects |
| Adults and children over 10 | 0.90% | 70 per µL | Roehrl et al., Arch Pathol Lab Med, 2011 (n > 2,400 US outpatients) | Infection, medication effect, inflammation |
| Children 10 and under | 0.30% | 40 per µL | Roehrl et al., 2011 | Otitis media, respiratory infection, gastroenteritis |
| Healthy adult blood donors | 0.63% | 0.06 × 10⁹/L | Monteiro et al., Int J Lab Hematol, 2021 (n = 115) | Normal biological variation |
| Pregnancy, first trimester | 0.92% | 0.091 × 10⁹/L | Yu et al., Int J Clin Exp Med, 2016 (n = 1,372) | Normal physiologic shift |
| Pregnancy, second trimester | 2.00% | 0.247 × 10⁹/L | Yu et al., 2016 | Normal physiologic shift |
| Pregnancy, third trimester | 3.80% | 0.456 × 10⁹/L | Yu et al., 2016 | Normal physiologic shift, peaks near term |
Table 1: Immature granulocyte reference limits by group.
How to Read Your Own Number
People arrive at this topic holding one specific value, so here is a plain reading of the common bands for a non-pregnant adult. Treat these as orientation, not diagnosis, and always defer to the range printed on your own report.
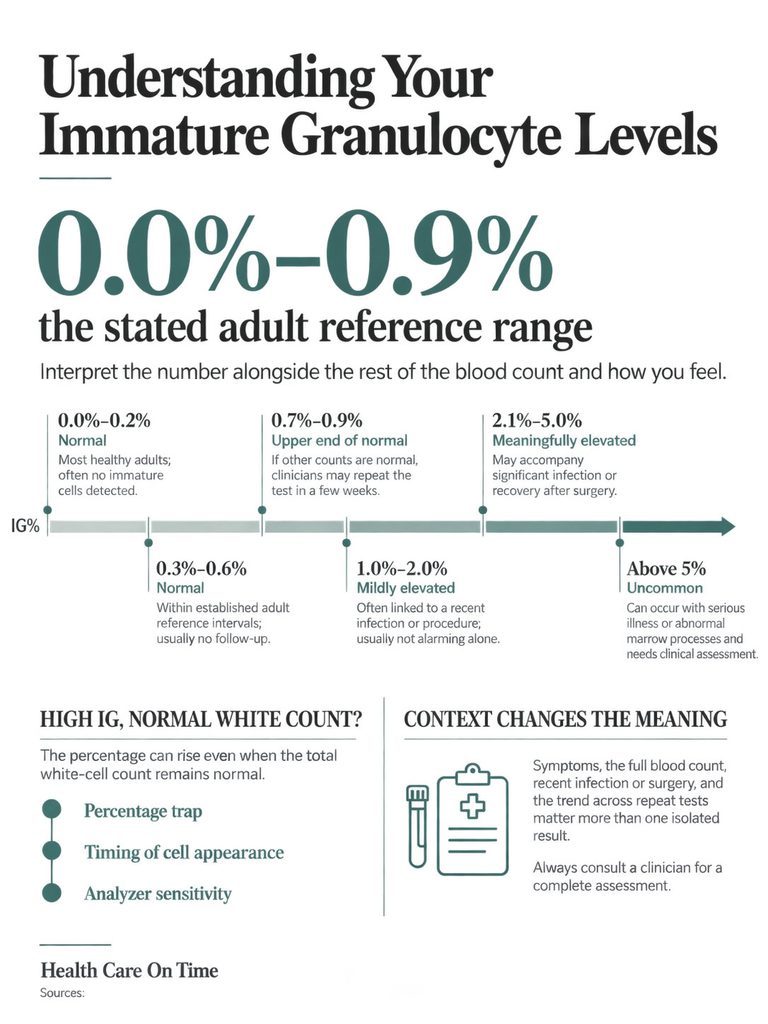
0.0% to 0.2%. Normal, and the most common result. Many healthy adults report 0.0%, which simply means the analyzer detected no immature cells in the sample it examined.
0.3% to 0.6%. Normal. This band sits inside every published adult reference interval and inside most lab-specific ones too. No follow-up is triggered by the value alone.
0.7% to 0.9%. Upper end of normal in adults, and flagged high by labs using a tighter internal cutoff. With a normal white count, normal hemoglobin, normal platelets, and no symptoms, this is the classic “repeat it in a few weeks” result.
1.0% to 2.0%. Mildly elevated for a non-pregnant adult. Nearly always reactive, and nearly always explained by something in the recent history: an infection, a procedure, a new medication, a fall or fracture. Worth an explanation, not worth alarm.
2.1% to 5.0%. Meaningfully elevated. This range shows up in significant infection, in the days after major surgery or severe trauma, and in people on growth factor injections. In pregnancy it can still be normal. Your clinician will want the rest of the blood count and your symptoms.
Above 5%. Uncommon outside of serious acute illness or an active marrow process. Almost always accompanied by other abnormalities that direct the workup, and usually already visible to whoever ordered the test.
When IG Is High but Your White Count Is Normal
This combination puzzles people more than any other, and it is common enough to deserve its own answer.
The first explanation is the percentage trap described earlier. A shrinking denominator raises the percentage without adding a single immature cell.
The second is timing. Immature granulocytes can appear early in an infection, sometimes before the total white count has climbed at all, which is precisely why emergency departments find the parameter useful.
The third is analyzer sensitivity, covered in a later section. Modern instruments detect small populations of cells that a human counting 100 cells on a slide would never have reported. Detection is not the same as danger.
Why Your Marrow Sent Them Out Early: Nine Causes

Bacterial Infection
The headline cause, and the reason the parameter earned attention in the first place. Pneumonia, urinary tract infection, cellulitis, abscess, appendicitis, and dental infection all push immature granulocytes into circulation.
The rise frequently precedes any large move in the total white count.
Viral Illness
Viruses are a weaker but genuine trigger. Influenza, COVID-19, and mononucleosis can each produce a modest left shift, and severe viral illness can produce a pronounced one.
Inflammation Without Infection
Rheumatoid arthritis flares, inflammatory bowel disease, pancreatitis, and vasculitis raise immature granulocytes through the same signaling pathways infection uses. The marrow cannot distinguish a bacterial threat from sterile inflammation.
Physical Stress and Tissue Injury
Surgery, major trauma, burns, fractures, cardiac arrest, and seizures all produce reliable, temporary elevations. So does labor and delivery.
If your blood was drawn within a few days of an operation or a significant injury, that timing alone accounts for most modest elevations. In cases reviewed across our diagnostic network, post-surgical blood counts are among the most frequent sources of an IG flag that resolves with no intervention at all.
Medications
Corticosteroids such as prednisone push neutrophils and their precursors out of the marrow and off the vessel walls. Granulocyte colony-stimulating factor injections (filgrastim and its relatives) do this on purpose, and can drive IG values dramatically high in someone who feels perfectly well.
Recovery from chemotherapy creates the same picture as the marrow restarts production. Lithium and several other agents contribute in some patients.
If you take any of these, the elevation is expected rather than surprising, and your oncology or rheumatology team already knows how to read it.
Pregnancy
Covered above. The elevation is physiologic, climbs through gestation, and needs a pregnancy-specific reference interval to interpret fairly.
Smoking
Chronic smoking shifts the entire white cell distribution upward, including granulocyte precursors. Smokers carry higher baseline counts than non-smokers, which changes how a borderline value should be weighed.
Recent Strenuous Exercise
Hard exertion mobilizes white cells from the marginal pool along vessel walls into the circulating pool. A draw taken shortly after a heavy workout can read differently from one taken on a rest day.
Blood and Bone Marrow Disorders
The rare bucket, and it deserves both honesty and proportion. Myelodysplastic syndromes, myeloproliferative neoplasms, chronic myeloid leukemia, and acute leukemias can all release immature myeloid cells into the blood.
For scale, SEER projects 67,790 new leukemia cases in the United States in 2026, an incidence rate of 14.7 per 100,000 people per year. The American Cancer Society estimates about 9,650 new chronic myeloid leukemia diagnoses in 2026, with a lifetime risk near 1 in 500 and an average age at diagnosis around 66.
Set that against the many millions of blood counts run each year in American labs, and the arithmetic explains why a mildly high IG in a well person is not handled as an emergency.
Leukemoid Reaction Versus Chronic Myeloid Leukemia
When the white cell count climbs above 50,000 per microliter with a strong left shift, hematologists use the term leukemoid reaction: a reactive picture that looks alarming and is not cancer.
The features that separate the two are specific. A leukemoid reaction shows mostly mature neutrophils carrying toxic granulation and Döhle bodies, alongside a high leukocyte alkaline phosphatase score.
Chronic myeloid leukemia typically shows a deeper left shift, a characteristic bulge of myelocytes, and absolute increases in basophils and eosinophils, as the American Society of Hematology education program describes.
The definitive answer is molecular. Testing peripheral blood for the BCR::ABL1 fusion, the product of the Philadelphia chromosome translocation, resolves the question in most cases without any bone marrow procedure.
How Good Is This Number, Really?
An honest article has to answer something the ranking pages skip. Does a high immature granulocyte count actually predict anything dependable?
What the Sepsis Research Found
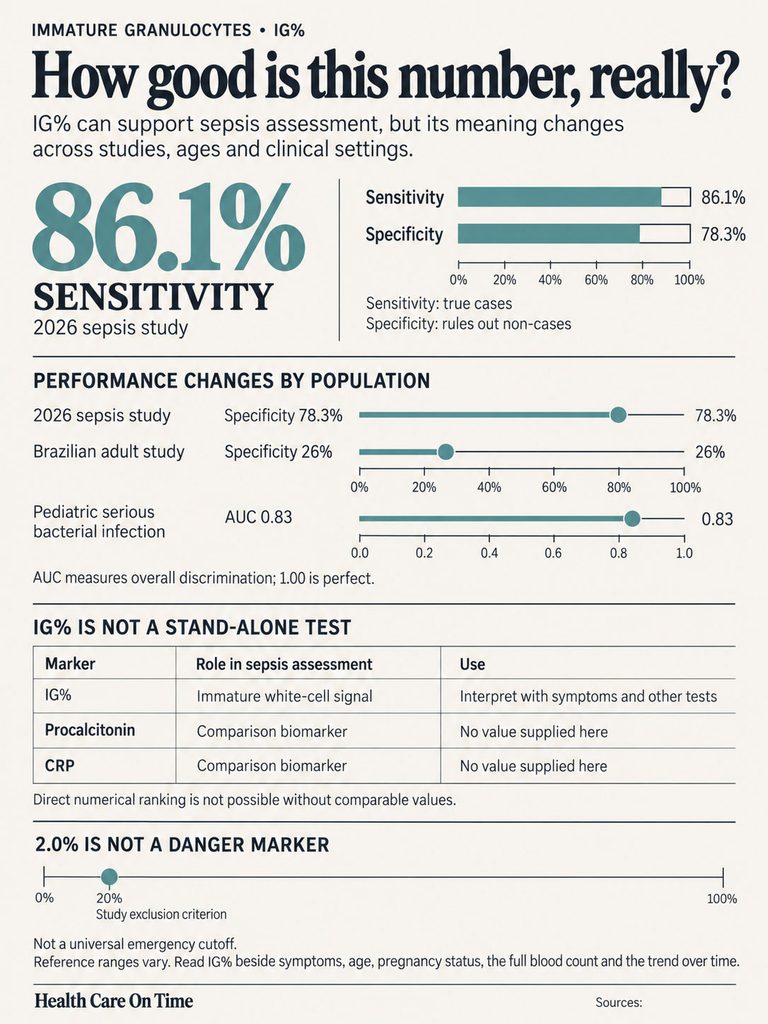
A 2026 intensive care study of 178 critically ill patients, 72 of whom developed sepsis, tested an IG% cutoff of 0.80%. It produced 86.1% sensitivity and 78.3% specificity, with a positive likelihood ratio of 3.96 and a negative likelihood ratio of 0.18.
In that study IG% outperformed procalcitonin, and both outperformed C-reactive protein. Combining IG% with procalcitonin beat either one alone.
Pediatric data has a similar shape. In children evaluated for serious bacterial infection, IG% produced an area under the curve of 0.83, against 0.76 for the white cell count, 0.73 for absolute neutrophils, and 0.79 for CRP. At a cutoff above 0.35%, sensitivity was 75.4% and specificity 76.6%.
Children with sepsis in that cohort averaged 3.7% IG. Those with bacterial meningitis averaged 1.6%.
The Specificity Problem, in Plain Terms
Not every study flatters the marker. In a Brazilian intensive care cohort of 200 adults with suspected infection, IG% reached 74.4% sensitivity against culture results but only about 26% specificity.
Translated: in a population where nearly everyone is sick with something, a high IG barely separates one cause from another. The parameter is far better at ruling problems out than ruling them in.
That reading also explains the 2.0% figure circulating online. Research found an IG% below 2.0% helped exclude sepsis with 90.9% specificity, at just 38.5% sensitivity. It is an exclusion threshold, not a line past which a person is in danger, and it was never designed to be applied to a routine annual physical.
Published cutoffs range from 0.2% to 3.0% across studies, depending on patient age and whether the goal is screening or exclusion. Anyone quoting one universal danger number is oversimplifying badly.
The appendicitis literature makes the same point differently. In one cohort with suspected appendicitis, the absolute immature granulocyte count predicted appendicitis while the percentage did not, with mean counts of 60 per µL in confirmed cases against 33 per µL in those without.
What the Evidence Cannot Tell You Yet
Two limits are worth naming. The reference interval studies underpinning the numbers in Table 1 were published in 2011 and 2016, and analyzer technology has moved since then, so modern instruments may read slightly differently.
And most sepsis and infection research on this marker has been done in intensive care units and emergency departments, not in primary care offices. How well a 1.2% result performs in a healthy adult at a routine checkup has simply not been studied at the same depth.
Our medical reviewers make a related point that gets lost easily. None of these markers is a diagnosis. They are inputs to a clinical judgment that also weighs your temperature, heart rate, blood pressure, and how you actually look and feel.
| Statistic | Figure | Source |
| US adults hospitalized with sepsis each year | About 1.7 million | CDC, Sepsis Data and Reports, 2026 |
| US adults who die or enter hospice after sepsis annually | At least 350,000 | CDC, Sepsis Data and Reports, 2026 |
| Share of in-hospital deaths involving sepsis | About 1 in 3 | CDC, Hospital Sepsis Program Core Elements |
| Projected new US leukemia cases, 2026 | 67,790 | NCI SEER Cancer Stat Facts |
| Projected new US acute myeloid leukemia cases, 2026 | 22,720 | NCI SEER Cancer Stat Facts |
| Projected new US chronic myeloid leukemia cases, 2026 | 9,650 | American Cancer Society |
| US leukemia incidence rate, all types | 14.7 per 100,000 per year | NCI SEER, 2019 to 2023 data |
Table 2: US numbers that put an immature granulocyte result in context.
The Machine and the Microscope Disagree
Here is something almost no patient is told. The IG% on your report and the IG% a pathologist would count under a microscope are two different measurements, and they do not match.

Why the Analyzer Reads Higher
Comparison studies of the Sysmex XN series against manual microscopic differentials have found a systematic positive bias, with the analyzer reading roughly 2.5 percentage points higher on average. In one such comparison, 57% of samples fell outside the 95% confidence interval expected for a manual count based on 500 cells.
The direction is consistent. The machine tends to overcall immature granulocytes relative to a human reviewer.
Laboratories know this and build their review rules around it. Work published in the Journal of Laboratory and Precision Medicine examined whether the common autovalidation threshold of 3% IG could safely be raised, comparing more than 800 samples by both methods.
What Triggers a Human Review
Most labs release a blood count automatically unless a rule fires. Common rules include an IG value above a set percentage, a very high or very low white count, a scatter pattern the analyzer cannot classify, or a first-time abnormal result in a patient with no prior history on file.
When a rule fires, a technologist makes a slide, stains it, and looks. That step is where the findings that change management actually live.
What a Slide Shows That a Number Cannot
A number tells you how many. A smear tells you what kind, and what the rest of the blood looks like.
Toxic granulation, Döhle bodies, and cytoplasmic vacuoles point toward a reactive process such as bacterial infection or growth factor therapy. Blasts point somewhere entirely different and trigger urgent evaluation.
A leukoerythroblastic picture, meaning immature granulocytes appearing alongside nucleated red blood cells and teardrop-shaped red cells, suggests the marrow architecture itself has been disturbed. That combination warrants prompt hematology input no matter how mild the IG number looks on its own.
Red Flags: What Needs Attention Today
The IG value itself almost never sets urgency. Your symptoms do.

Call 911 or Go to an Emergency Department
Fever with shaking chills, confusion or sudden disorientation, severe shortness of breath, a heart rate that stays fast at rest, low blood pressure, lightheadedness on standing, skin that is mottled or unusually cold and clammy, or a strong sense that something is badly wrong.
These are sepsis warning signs and they do not wait for a lab interpretation. The CDC notes that most sepsis cases begin before a person reaches the hospital, and that nearly a quarter to a third of people who develop it had a healthcare visit in the preceding week.
Call Your Clinician Within a Day or Two
Persistent fever above 100.4°F, a new or worsening localized infection, drenching night sweats, unexplained weight loss, easy bruising or bleeding, bone or joint pain that keeps you awake, swollen lymph nodes, or a feeling of fullness under the left rib cage.
Call promptly as well if your hemoglobin or platelet count is abnormal on the same report, or if the lab comment mentions blasts.
Routine Follow-Up
A single mildly elevated IG with a normal white count, normal hemoglobin, normal platelets, no fever, and no symptoms usually means a repeat blood count in two to six weeks and nothing more.
Patients commonly ask us whether they should push for additional testing in that situation. The answer from most hematologists is that the repeat test is the additional testing.
The Pattern Beats the Number
One value is a snapshot. Two or three values are a direction.
An IG that was 1.2% during a sinus infection and 0.2% a month later has told a complete story. An IG that ran 1.2%, then 2.1%, then 3.4% across three months in someone with no infection has told a different one, and that trajectory is what prompts referral.
| Your situation | What it most likely reflects | Recommended action | Timeframe |
| IG 0.3% to 0.9%, rest of blood count normal, feeling well | Normal variation or a resolving minor illness | Repeat blood count at your next routine draw | 4 to 8 weeks |
| IG 1% to 3%, recent surgery, injury, or infection | Expected reactive left shift | Repeat blood count after full recovery | 2 to 6 weeks |
| IG elevated, currently pregnant, no symptoms | Physiologic pregnancy shift | Mention at your next prenatal visit, no separate workup usually needed | Next scheduled visit |
| IG elevated while taking prednisone or a growth factor injection | Known medication effect | Inform the prescribing clinician, do not stop medication on your own | Next contact |
| IG elevated with fever, fast heart rate, or confusion | Possible serious infection or sepsis | Emergency department now | Immediately |
| IG elevated with abnormal hemoglobin or platelets | Needs a broader marrow evaluation | Contact your clinician, expect smear review and possible referral | Within days |
| IG rising across three consecutive tests with no explanation | Requires hematology assessment | Ask for a referral and peripheral smear review | Within 2 to 4 weeks |
Table 3: Scenario to recommended action.
What Happens Next

The Repeat Blood Count
Repeating the test is the highest-yield next step, and it is deliberately unglamorous. Reactive elevations fall as the trigger resolves, usually within days to a few weeks.
Timing matters. Drawing the repeat while you are still fighting the same infection will simply show the same thing.
Tests Your Clinician May Add
A peripheral blood smear review is often first, and it is inexpensive. C-reactive protein and procalcitonin help gauge whether inflammation or bacterial infection is active.
A metabolic panel checks kidney and liver function. Blood cultures enter the picture when infection is suspected.
If a marrow disorder is genuinely on the table, BCR::ABL1 testing and other molecular studies can usually be run on peripheral blood before anyone raises the subject of a bone marrow biopsy.
What Triggers a Hematology Referral
Persistently elevated IG with no identifiable cause, blasts on a smear, a leukoerythroblastic picture, unexplained anemia or low platelets alongside the IG finding, or a white cell count that stays above 50,000 per microliter with no reactive explanation.
A referral is not a verdict. It is the appropriate level of expertise for a pattern a primary care panel cannot settle on its own.
US Cost and Access
A blood count with differential bills under CPT code 85025, and the version without a platelet count uses 85027. A manual differential or pathologist smear review carries separate codes, commonly 85007 or 85060.
Direct-to-consumer and cash-pay laboratory programs typically price a blood count with differential in the low tens of dollars. The same test billed through a hospital outpatient department can run several times that, sometimes into the low hundreds, and the difference is facility fees rather than anything about the test itself.
Insured patients generally find a repeat blood count covered when it is ordered to follow up an abnormal result, though your deductible status determines what you actually pay at the counter. Across the tests booked through HealthCareOnTime, this remains one of the least expensive follow-up steps in all of laboratory medicine, which is another reason clinicians reach for it before anything invasive.
What You Can and Cannot Do About It
There is no treatment for a high immature granulocyte count. There is treatment for whatever caused it.
Antibiotics for a bacterial infection. Anti-inflammatory therapy for an autoimmune flare. Time and healing after surgery. When the cause resolves, the number follows.

No supplement, diet, or “immune boosting” protocol has been shown to lower immature granulocytes, and any product marketed on that claim is selling you a lab value rather than a health outcome.
The reasonable ground-level advice stays unremarkable: treat infections promptly, keep vaccinations current, stop smoking, sleep, and keep your follow-up appointment.
The most useful thing you can actually do is bring context. Recent illnesses, recent procedures, every medication including over-the-counter and injectable ones, and whether you are pregnant. Those details resolve more IG questions than any additional test.
Frequently Asked Questions
Is 0.1% immature granulocytes high?
No. A value of 0.1% sits comfortably inside every published adult reference interval, which generally top out between 0.6% and 0.9%. Many healthy adults report 0.0%, so a small non-zero value simply means the analyzer detected a few early cells. On its own it warrants no follow-up.
What immature granulocyte level is dangerous?
No single number is dangerous by itself. Published cutoffs range from 0.2% to 3.0% depending on age group and clinical question. Values above 2% become more meaningful when paired with fever, a high white count, or elevated inflammatory markers. Your symptoms determine urgency, not the number.
Can immature granulocytes be high without any infection?
Yes, often. Surgery, trauma, burns, seizures, autoimmune flares, pregnancy, corticosteroids, growth factor injections, chemotherapy recovery, smoking, and recent strenuous exercise all raise immature granulocytes with no bacteria involved. The marrow responds to demand signals, and infection is only one source.
Does a high immature granulocyte count mean leukemia?
Almost never on its own. Leukemia affects roughly 14.7 Americans per 100,000 each year, while elevated IG results are common in routine practice. Leukemia is suspected when IG rises alongside abnormal hemoglobin, abnormal platelets, blasts on a smear, or a persistently very high white count.
Why is IG high when my white blood cell count is normal?
Two reasons. A percentage rises when the total white count falls, even though the number of immature cells has not changed. And early in an infection, immature granulocytes sometimes appear before the total white count climbs. Checking the absolute IG count, when reported, clarifies which applies.
How long do immature granulocytes stay elevated?
For reactive causes, usually days to a few weeks. The level tracks the trigger, so it drops as an infection clears or a surgical site heals. Elevations persisting beyond six to eight weeks with no obvious explanation are the ones that prompt further evaluation rather than more waiting.
Do immature granulocytes rise in pregnancy?
Yes, predictably. Trimester-specific data puts the upper limit at 0.92% in the first trimester, 2.00% in the second, and 3.80% in the third. Median values in healthy pregnant women run roughly double those in non-pregnant women. Most analyzers flag these results because they compare against non-pregnant ranges.
What is the difference between IG% and absolute immature granulocytes?
IG% is the share of your white blood cells that are immature. Absolute IG is the actual number of those cells per microliter or liter. The absolute count is steadier because it does not shift when other white cell populations rise or fall. Clinicians read both together when both appear.
Can stress or hard exercise raise immature granulocytes?
Physical stress can. Surgery, injury, burns, and severe illness reliably push immature cells into circulation, and strenuous exercise mobilizes white cells from vessel walls into the bloodstream. Everyday psychological stress has a much weaker and less consistent effect and rarely explains a flagged result.
Is a bone marrow biopsy needed for a high IG result?
Rarely. Biopsy is considered when immature granulocytes stay elevated without explanation, when blasts appear on a smear, or when other blood counts are abnormal at the same time. Most evaluations start with a repeat blood count and a peripheral smear, and many are settled by molecular testing on blood alone.
Can smoking raise immature granulocytes?
Yes. Chronic smoking shifts the entire white blood cell distribution upward, including granulocyte precursors, and smokers carry higher baseline counts than non-smokers. If you smoke, mention it when discussing an abnormal result, because it changes how a clinician weighs a mild elevation.
Should the test be repeated, and how soon?
Usually yes, and timing depends on the cause. If an infection or surgery explains the result, repeating once you have fully recovered makes sense, commonly two to six weeks out. With no obvious trigger and no symptoms, four to eight weeks is typical. Your clinician sets the interval based on the full picture.
Medical Disclaimer: This article is for general information only and is not a substitute for professional medical advice, diagnosis, or treatment. Laboratory reference ranges vary by laboratory, analyzer, age, and pregnancy status, and the range printed on your own report takes precedence over any figure published here. Always discuss abnormal blood test results with a licensed clinician who can interpret them alongside your symptoms and medical history. If you have fever with confusion, difficulty breathing, a rapid heart rate, or you feel severely unwell, seek emergency care immediately.
References
- Age-Dependent Reference Ranges for Automated Assessment of Immature Granulocytes and Clinical Significance in an Outpatient Setting, Archives of Pathology and Laboratory Medicine, 2011
- Definition of Reference Range for the Immature Granulocytes Parameter Provided by a Hematology Analyzer, International Journal of Laboratory Hematology
- Changes and Reference Intervals of Immature Granulocytes in the Peripheral Blood of Women According to Pregnancy Trimester, International Journal of Clinical and Experimental Medicine, 2016
- Diagnostic Accuracy of Immature Granulocyte Count for Early Sepsis Detection: A Comparative Evaluation With C-Reactive Protein and Procalcitonin
- Evaluation of the Accuracy of Immature Granulocyte Percentage in Predicting Pediatric Serious Bacterial Infection
- Accuracy of Sysmex XN Immature Granulocyte Percentage Compared to Manual Microscopy, Journal of Laboratory and Precision Medicine
- The Utility of Immature Granulocyte Count and Percentage in Suspected Acute Appendicitis
- Malignant or Benign Leukocytosis, American Society of Hematology Education Program
- About Sepsis, Centers for Disease Control and Prevention
- Hospital Sepsis Program Core Elements, Centers for Disease Control and Prevention
- Cancer Stat Facts: Leukemia, National Cancer Institute SEER Program
- Cancer Stat Facts: Acute Myeloid Leukemia, National Cancer Institute SEER Program
- Key Statistics for Chronic Myeloid Leukemia, American Cancer Society
- Granulocytes: What They Are and How They Protect You, Cleveland Clinic