In February 2025, the FDA pulled the heart attack and stroke language out of the boxed warning on every testosterone product. Sixteen months later, federal health officials asked drugmakers to loosen the labels even further.
Table of Contents
So testosterone is safe now, right? Not so fast. The same landmark trial that cleared it for heart attacks also found more irregular heartbeats, more lung clots and, to everyone’s surprise, more broken bones.
Quick Answer: Hormone therapy for men (testosterone replacement therapy, or TRT) is generally safe for men with confirmed low testosterone and symptoms, when it’s prescribed with FDA-approved products and monitored with regular blood tests. The largest trial so far found no rise in heart attacks or strokes. It still carries real risks: a thick-blood problem, blood pressure rises, worse sleep apnea, lower sperm counts and small increases in atrial fibrillation and clots.
At a Glance
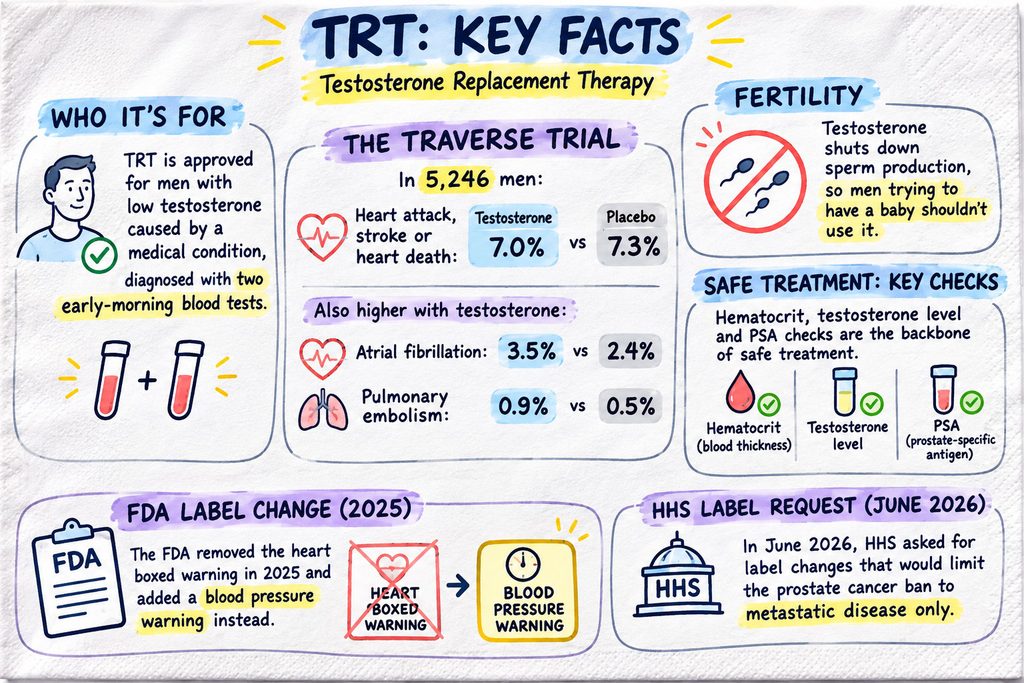
- TRT is approved for men with low testosterone caused by a medical condition, diagnosed with two early-morning blood tests.
- In the TRAVERSE trial of 5,246 men, heart attack, stroke or heart death hit 7.0% on testosterone versus 7.3% on placebo.
- The same trial found more atrial fibrillation (3.5% vs 2.4%) and pulmonary embolism (0.9% vs 0.5%).
- Testosterone shuts down sperm production, so men trying to have a baby shouldn’t use it.
- Hematocrit, testosterone level and PSA checks are the backbone of safe treatment.
- The FDA removed the heart boxed warning in 2025 and added a blood pressure warning instead.
- In June 2026, HHS asked for label changes that would limit the prostate cancer ban to metastatic disease only.
What “Hormone Therapy for Men” Actually Means
The phrase covers three very different things, and mixing them up causes a lot of bad decisions. Before asking whether hormone therapy is safe for men, it helps to know which one you’re talking about.

Testosterone Replacement Therapy (TRT)
TRT raises low testosterone back toward the normal range. According to the FDA, approved forms include pills, skin gels, patches, a buccal system stuck to the gum, and injections.
The Endocrine Society adds pellets placed under the skin every 3 to 6 months and a nasal gel. This article is mostly about TRT.
Prostate Cancer Hormone Therapy (ADT)
This is the opposite treatment. The Prostate Cancer Foundation describes it as “anti-testosterone therapy,” because it lowers or blocks testosterone to starve prostate cancer cells.
Its side effects (hot flashes, bone loss, erectile problems, weight gain, higher diabetes and heart risk) come from having too little testosterone. Readers often ask us whether “hormone therapy” news about prostate cancer applies to TRT. It doesn’t.
Clinic “Bioidentical” Programs and Over-the-Counter Boosters
Many cash-pay clinics sell hormone packages with branded names. Some use FDA-approved testosterone; some don’t. The Endocrine Society says only FDA-approved hormones should be used.
So-called natural testosterone boosters sold online are a separate category again. Cleveland Clinic cardiologist Steven Nissen, senior author of TRAVERSE, has warned that these products haven’t been tested in rigorous trials or approved by the FDA to treat low testosterone (as reported by TCTMD and in Cleveland Clinic’s trial announcement).
The Short Answer: Safe for the Right Man, With Monitoring
The Endocrine Society’s patient guide is direct: doctor-prescribed testosterone is safe and can be effective for men diagnosed with consistently low testosterone plus matching symptoms. The word doing the heavy lifting is “diagnosed.”
Low testosterone alone isn’t enough. Symptoms alone aren’t enough either. Harvard Health points out that most tired men who get tested turn out to have normal levels.
Who TRT Is Approved For
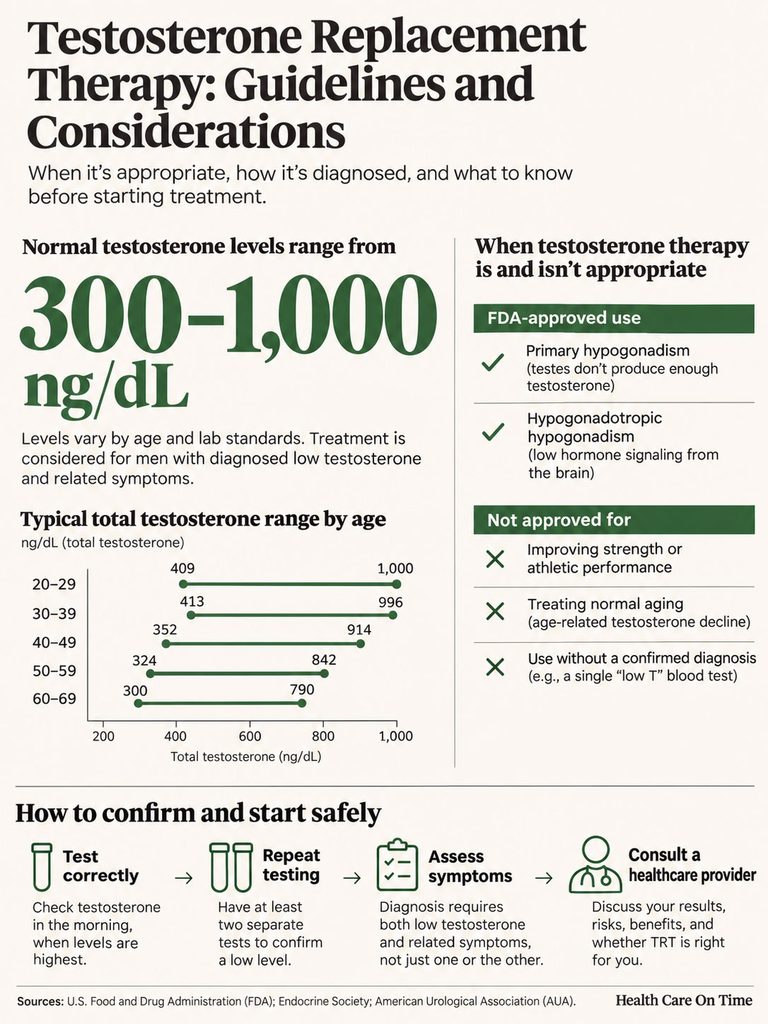
FDA-approved testosterone is labeled for men with primary hypogonadism (a testicle problem) or hypogonadotropic hypogonadism (a pituitary or brain signaling problem), according to the April 2026 Federal Register notice.
The Endocrine Society also says boosting testosterone isn’t FDA-approved to improve strength, athletic performance or appearance, or to treat aging. Using it for those goals may harm your health.
How Low Is “Low”?
The Endocrine Society’s patient guide puts normal total testosterone at roughly 300 to 1,000 ng/dL, depending on age and lab. Its 2018 guideline team cited a CDC-harmonized range of about 264 to 916 ng/dL (9.2 to 33 nmol/L).
Timing matters. Harvard advises testing between 7 and 10 a.m., when levels peak, and repeating a low result on another day. UCSF Urology calls at least two morning levels essential. A single afternoon reading proves very little.
Our medical content team sees this mistake constantly: one random-time blood draw labeled “low T,” followed by a prescription. If you haven’t had your testosterone test repeated in the morning, that’s step one.
What Changed: The FDA and HHS Label Updates
Testosterone safety advice has shifted more in the last two years than in the previous decade. Here’s the timeline our editors checked against the official FDA and HHS releases.

2014 to 2015: The Warnings Arrive
In January 2014, the FDA warned about reported strokes, heart attacks and deaths in men using testosterone. In March 2015 it required label changes and urged caution about using testosterone for low levels due to aging.
Prescribing dropped fast. A 2018 JAMA research letter found testosterone use among commercially insured men 30 and older climbed from 0.52% in 2002 to 3.20% in 2013, then fell to 1.67% by 2016.
February 2025: Heart Warning Out, Blood Pressure Warning In
After reviewing TRAVERSE, the FDA removed the boxed-warning language about increased cardiovascular risk from all testosterone products. It added TRAVERSE results to every label.
But the FDA didn’t hand out a clean bill of health. Required ambulatory blood pressure studies confirmed that all testosterone products, class-wide, raise blood pressure. Labels now carry a blood pressure warning.
April 2026: A Possible New Use
On April 16, 2026, the FDA invited makers of approved TRT products to discuss a new indication: low libido in men with idiopathic hypogonadism, meaning low testosterone with no known cause. A preliminary literature review suggested TRT may be safe and effective for that group.
That’s an invitation, not an approval. The agency said any new indication would still need rigorous evidence and a full risk-benefit review.
June 2026: HHS Requests Looser Prostate Language
On June 18, 2026, HHS announced that the FDA was requesting three label changes. The first removes the statement that safety and effectiveness haven’t been established in age-related low testosterone.
The second would make metastatic prostate cancer the only prostate cancer contraindication. The third revises the enlarged-prostate (BPH) warning while recommending continued monitoring for men with severe symptoms.
These were requested changes. Depending on when your product’s label was updated, the leaflet in your box may still show older wording. Ask your pharmacist which version applies.
TRT Risks, One by One
Here’s the side-by-side view none of the top-ranking pages give you. Every number below comes from a published trial or a US medical society.
| Risk | What Happens in the Body | What the Evidence Shows | How It’s Caught |
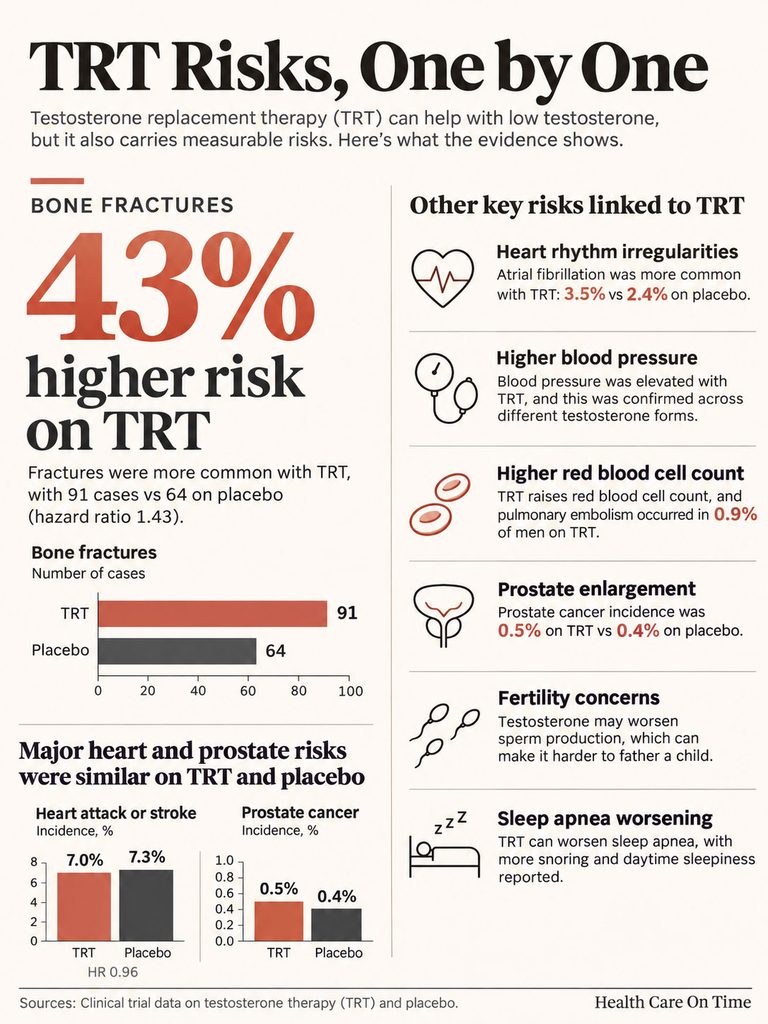
| Heart attack and stroke | Long-feared link to clots and plaque events | TRAVERSE: 7.0% on TRT vs 7.3% on placebo (HR 0.96) | Cardiovascular risk review before starting |
| Heart rhythm | Irregular beats, mainly atrial fibrillation | TRAVERSE: AF 3.5% vs 2.4%; any treated arrhythmia 5.2% vs 3.3% | Report palpitations; ECG if symptoms |
| Blood pressure | Pressure rises on all testosterone forms | FDA ABPM studies confirmed a class-wide increase | Home or office BP checks |
| Thick blood and clots | Red cell count climbs (erythrocytosis) | Most frequent side effect per Endocrine Society; PE 0.9% vs 0.5% in TRAVERSE | Hematocrit at baseline, 3 to 6 months, then yearly |
| Prostate | Can enlarge prostate and stimulate existing cancer | TRAVERSE prostate cancer: 0.5% vs 0.4% (not significant) | PSA and rectal exam per age and risk |
| Fertility | Brain stops signaling the testicles to make sperm | UCSF: testosterone is very likely to worsen fertility | Semen analysis if fertility matters |
| Sleep apnea | Breathing pauses during sleep can worsen | Listed by Mayo Clinic, Harvard and the Endocrine Society | Ask about snoring, daytime sleepiness |
| Bones | Unexpected rise in fractures | TRAVERSE: 91 vs 64 clinical fractures (HR 1.43) | Bone density review in men at risk |
Heart and Blood Pressure: What TRAVERSE Really Found
TRAVERSE enrolled 5,246 men aged 45 to 80 at 316 US sites, all with existing heart disease or high heart risk and two fasting testosterone levels below 300 ng/dL, according to TCTMD’s trial report.
Men used a daily 1.62% testosterone gel or a placebo gel, with doses adjusted to reach 350 to 750 ng/dL. Over a mean 33-month follow-up, the main heart endpoint was a tie. That’s a genuinely reassuring result for a high-risk group.
The fine print matters, though. Testosterone users had more nonfatal arrhythmias needing treatment, more atrial fibrillation and more acute kidney injury (2.3% vs 1.5%). One outside endocrinologist called the kidney result a possible statistical fluke.
There’s also an honest limitation: the trial was paid for by testosterone makers, and men took the drug for an average of about 22 months. It can’t tell you what 15 years of use does.
Red Blood Cells and Blood Clots
Testosterone pushes the bone marrow to make more red blood cells. A little rise is expected. Too much thickens the blood, and Mayo Clinic notes that this raises the chance of a clot that could travel to the lungs.
The Endocrine Society’s 2018 guideline review found erythrocytosis (hematocrit above 54%) was the most common side effect in older men. In TRAVERSE, pulmonary embolism was 0.9% on testosterone versus 0.5% on placebo, as reported by MDedge.
When our team reviews lab reports, the hematocrit line is the one we see readers overlook most. It sits on a routine CBC and quietly creeps up over months.
Prostate: Growth, PSA and Cancer
Mayo Clinic lists two prostate concerns: noncancerous enlargement (BPH) and faster growth of a cancer that’s already there. Testosterone doesn’t appear to create new cancers in the short term.
In TRAVERSE, prostate cancer showed up in 12 men on testosterone and 11 on placebo. HHS still notes real uncertainty, because prostate cancer can take years to develop and studies may not have followed men long enough.
That’s why PSA checks stay in every guideline. Our PSA test guide explains what the number does and doesn’t mean.
Sleep Apnea
Mayo Clinic, Harvard and the Endocrine Society all list worsening sleep apnea. The Endocrine Society says men with untreated sleep apnea shouldn’t start testosterone at all.
If your partner says you snore and stop breathing at night, get a sleep study first. Treating the apnea may also improve the fatigue you blamed on low T.
Fertility and Sperm Count
This is the risk younger men most often miss. Added testosterone tells the brain to stop sending the signals that drive sperm production. UCSF states plainly that testosterone is not a fertility treatment and is very likely to make fertility worse.
The Endocrine Society lists “planning to have children” as a reason not to receive testosterone. Mayo Clinic adds that testicles can shrink. Other medicines exist for men who need treatment but want to keep fertility, so ask a urologist.
Bones: The Surprise Finding
Doctors expected testosterone to protect bones. Instead, TRAVERSE recorded 91 clinical fractures on testosterone versus 64 on placebo. The investigators said the trial wasn’t designed to explain why.
One expert suggested men at high fracture risk may need standard bone medicines rather than assuming testosterone will protect them.
Skin, Breasts and Swelling
Harvard lists acne, breast swelling or tenderness, and ankle swelling among early side effects. Gels can also rub off onto partners or children through skin contact, so the Endocrine Society advises letting the gel dry fully.
What Benefits Can You Realistically Expect?
Safety only matters next to benefit. A drug with small risks and no payoff isn’t worth taking, so here’s what the evidence says testosterone actually does for men with real deficiency.
Sexual Function
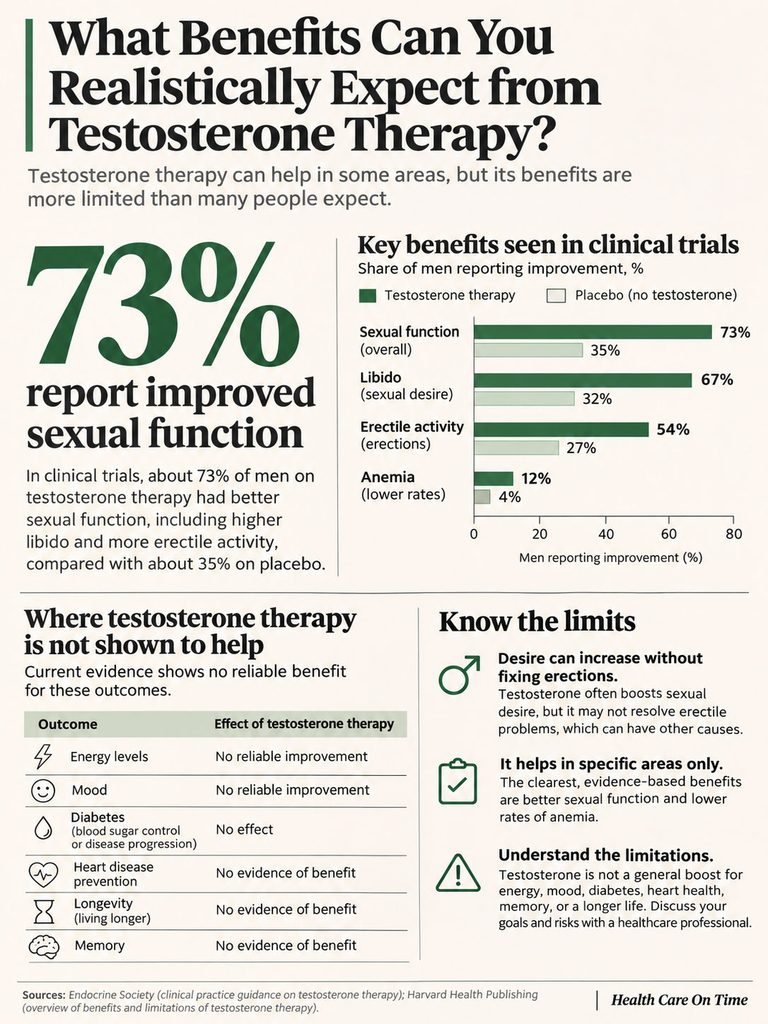
This is the strongest benefit. The Endocrine Society’s 2018 review found significant improvement in libido, erectile function and sexual activity. TRAVERSE confirmed better sexual activity and desire over one year, maintained over two years.
Erections are a separate issue, though. Harvard notes testosterone may raise desire without fixing erectile problems, and you may still need other treatment.
Anemia
TRAVERSE found lower rates of anemia in men on testosterone, both in men who started with it and in men who didn’t. The Endocrine Society also lists anemia correction as a supported benefit.
What It Doesn’t Reliably Do
The same Endocrine Society review found no significant difference in energy or mood. TRAVERSE showed no effect on progression from prediabetes to diabetes or on blood sugar control.
Harvard puts it plainly: testosterone isn’t a fountain of youth. There’s no proof it helps you live longer, prevents heart disease or sharpens memory. Our medical content team flags this gap often, because clinic ads tend to promise exactly those things.
Gels, Shots, Pellets and Patches: Safety Differences
Every form carries the core risks above. Each one also has its own practical problems, listed in the Endocrine Society’s patient guide:
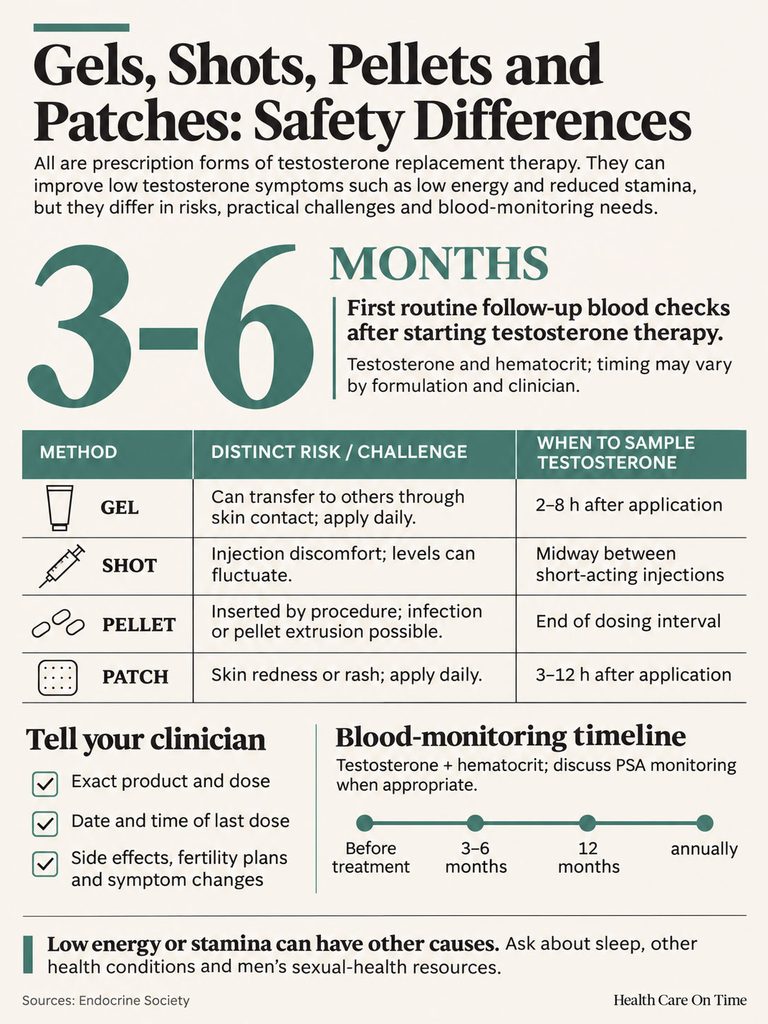
- Injections: given every 1 to 2 weeks, or every 10 weeks for a longer-acting clinic shot. Levels can swing, so symptoms may rise and fall between doses.
- Gels and solutions: applied to the upper arm, shoulder, inner thigh or armpit. They can transfer to a partner or child by skin contact until fully absorbed.
- Patches: worn daily; skin redness and rash are common, so sites are rotated.
- Buccal tablets: stuck to the gum twice a day; gum irritation is the main complaint.
- Pellets: placed under the skin every 3 to 6 months. A pellet can work its way out, and the dose fades toward the end of each cycle.
- Nasal gel: pumped into each nostril three times a day; it can irritate the nose.
The form also changes when blood is drawn for monitoring, which is why your doctor needs to know exactly what you use. If you’re also working on stamina and energy without hormones, our guide to maintaining sexual health for men covers habits that help either way.
TRT by the Numbers
These figures help put the risks in proportion. Each comes from a source our editors opened and checked.
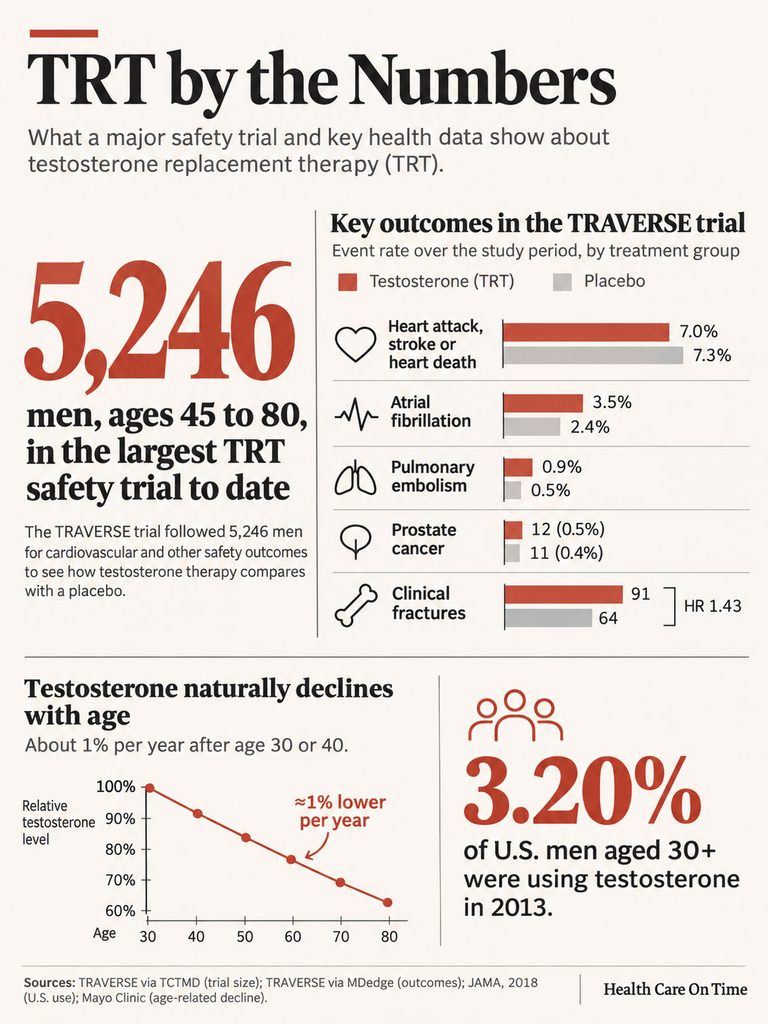
| Measure | Figure | Source |
| Men in the largest TRT safety trial | 5,246 men aged 45 to 80 | TRAVERSE via TCTMD |
| Heart attack, stroke or heart death | 7.0% testosterone vs 7.3% placebo | TRAVERSE via MDedge |
| Atrial fibrillation | 3.5% vs 2.4% | TRAVERSE via MDedge |
| Pulmonary embolism | 0.9% vs 0.5% | TRAVERSE via MDedge |
| Prostate cancer cases | 12 (0.5%) vs 11 (0.4%) | TRAVERSE via MDedge |
| Clinical fractures | 91 vs 64 (HR 1.43) | TRAVERSE via MDedge |
| US men 30+ using testosterone, 2013 peak | 3.20% | JAMA, 2018 |
| Same group, 2016 | 1.67% | JAMA, 2018 |
| Natural testosterone decline | About 1% a year after age 30 or 40 | Mayo Clinic |
| Normal total testosterone | About 300 to 1,000 ng/dL | Endocrine Society |
Who Should Not Take Testosterone
The Endocrine Society’s patient guide lists clear reasons not to receive testosterone. This list answers the question competitors bury in long paragraphs:

- A history of blood clots
- Prostate or breast cancer, known or suspected
- An elevated PSA that hasn’t been evaluated
- An enlarged prostate causing trouble urinating
- A heart attack or stroke within the last six months
- A high red blood cell count
- Plans to father a child soon
- Untreated sleep apnea
Where the Rules Are Shifting
Two items on that list are under review. The June 2026 HHS request would limit the prostate cancer contraindication to metastatic disease. It would also soften the BPH warning for mild to moderate symptoms.
That doesn’t mean a man with treated prostate cancer should start testosterone on his own. It means the conversation with a urologist may be different than it was a few years ago.
Older Men
The Endocrine Society’s 2018 guideline recommends against routinely prescribing testosterone to all men 65 and older with low levels. For older men with clear symptoms and consistently low morning levels, it suggests an individual decision after an explicit talk about risks and benefits.
Mayo Clinic is blunter: treating normal aging with testosterone isn’t advisable. If you’re comparing this with the women’s side, our guide on hormone therapy safety for women over 60 shows how age changes the math there too. For the broader history of hormone debates, see our piece on hormone replacement therapy and menopause.
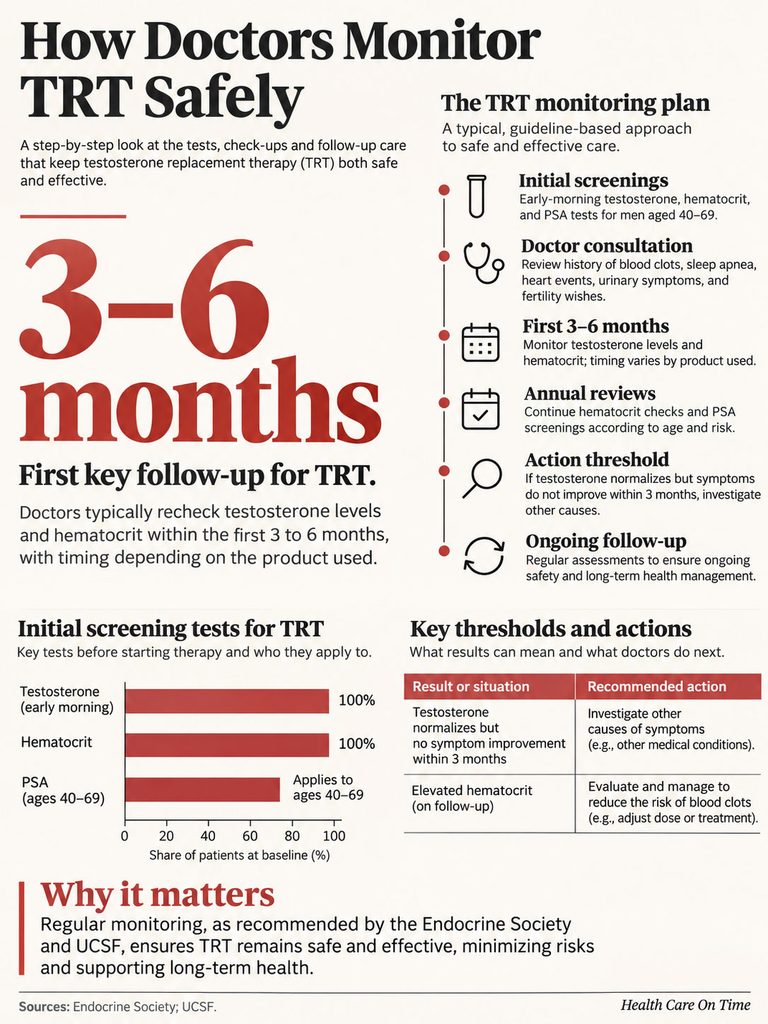
How Doctors Monitor TRT Safely
Monitoring is what turns a risky drug into a reasonably safe one. TRAVERSE’s lead investigator stressed that its reassuring results applied to men who were monitored carefully, as they were in the trial.
Before You Start
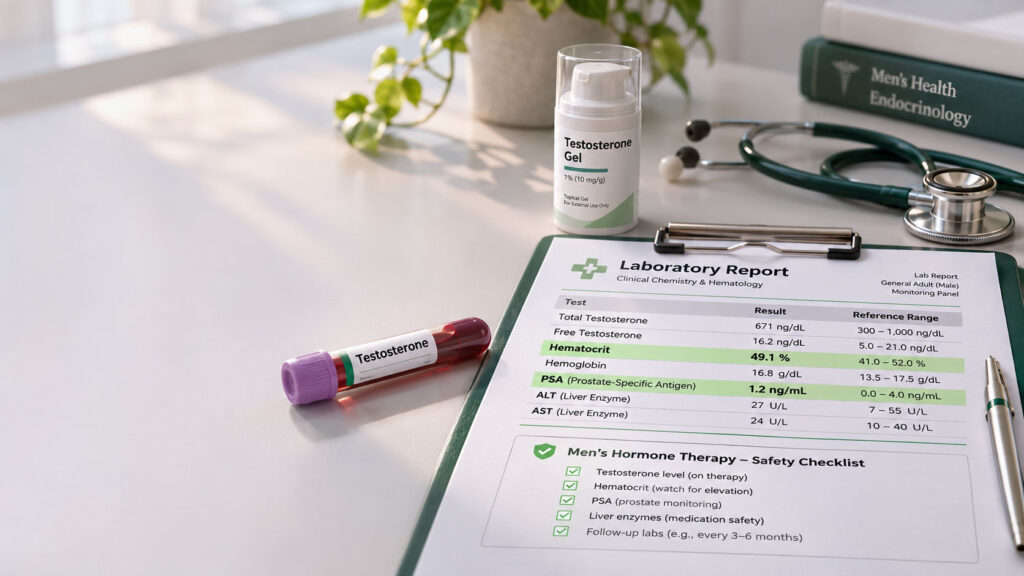
Expect two early-morning testosterone levels, a hematocrit (part of a CBC), and a PSA if you’re in a screening age group. The Endocrine Society suggests PSA and a rectal exam for men 55 to 69, and for higher-risk men from age 40.
Your doctor should also ask about blood clots, sleep apnea, heart events in the last six months, urinary symptoms and whether you want children.
The First 3 to 6 Months
The Endocrine Society recommends checking testosterone 3 to 6 months after starting, aiming for the mid-normal range. Hematocrit should be rechecked 3 to 6 months in.
Timing depends on the product. An MDedge summary of the guideline notes that with gels, blood is drawn 2 to 8 hours after applying. PSA and a rectal exam are repeated 3 to 12 months after starting for men in screening groups.
Every Year After That
Hematocrit and a symptom review continue yearly. PSA then follows normal prostate screening rules for your age and risk.
The Numbers That Trigger Action
- Hematocrit above 54%: hold testosterone until it falls, then restart at a lower dose.
- PSA rise of more than 1.4 ng/mL within 12 months: urology referral.
- Confirmed PSA above 4 ng/mL: urology referral.
- Abnormal prostate exam or much worse urinary symptoms: urology referral.
UCSF adds a useful rule: if your testosterone level normalizes but you don’t feel better within about three months, look for another cause rather than raising the dose.
Your TRT Decision Guide
Use this table to match your situation to a sensible next step. It’s a starting point for a doctor visit, not a substitute for one.

| Your Situation | What It Means | Recommended Action |
| Tired, one afternoon test under 300 ng/dL | Not a diagnosis yet | Repeat two morning tests on different days |
| Two morning levels low, clear symptoms, no red flags | Likely a TRT candidate | Discuss FDA-approved options and a lab schedule |
| Trying to conceive in the next year or two | Testosterone will likely lower sperm count | Ask a urologist about fertility-sparing options |
| Heart attack or stroke in the last 6 months | Endocrine Society says don’t start yet | Wait and revisit with your cardiologist |
| Loud snoring, daytime sleepiness | Possible untreated sleep apnea | Get a sleep study before starting |
| On TRT, hematocrit 55% | Blood too thick | Doctor holds therapy, rechecks, lowers dose |
| On TRT, PSA up 1.5 ng/mL in a year | Above the 1.4 ng/mL trigger | Urology evaluation |
| History of prostate cancer, now cancer-free | Rules are being revised | Decide only with your urologist |
Mistakes That Make TRT Riskier
Most testosterone problems our team reads about don’t come from the drug itself. They come from how it’s started and followed.
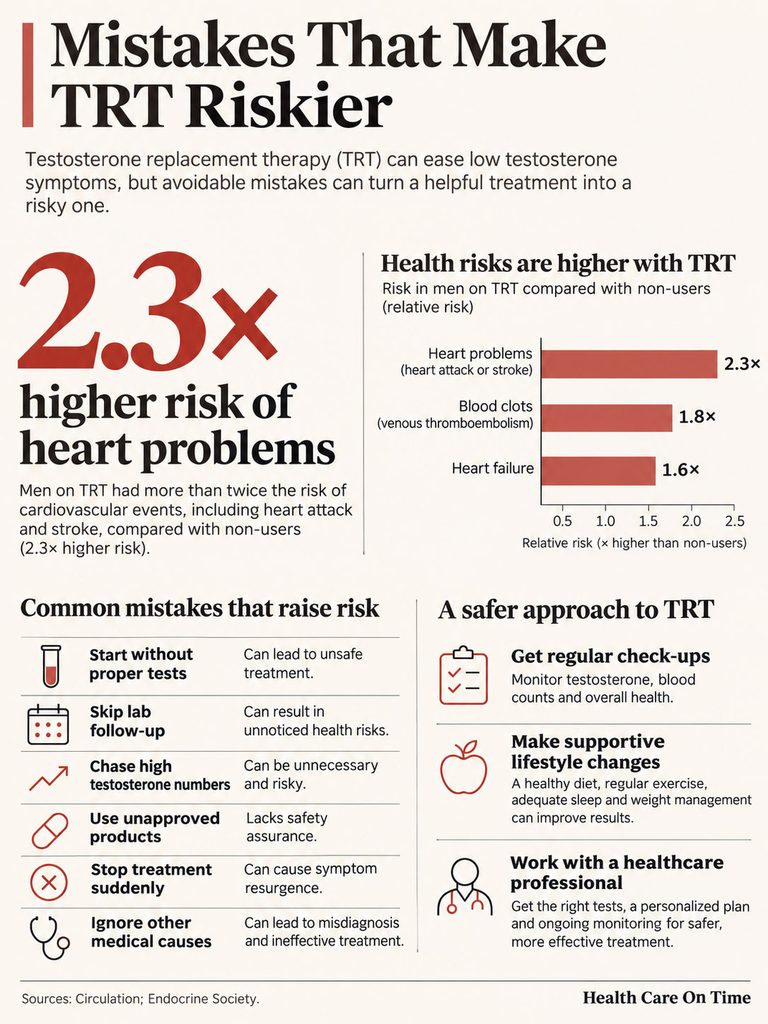
Starting without proper tests. A 2023 trial report noted that at many clinics, hormone levels aren’t tested first or checked afterward. TRAVERSE’s safety findings don’t apply to men who never had real deficiency.
Skipping the lab follow-up. Hematocrit and blood pressure can rise silently. A blood test every few months in year one costs far less than a clot.
Chasing high numbers. TRAVERSE targeted 350 to 750 ng/dL. Guidelines aim for mid-normal, not the top of the chart.
Using unapproved products. Supplements and non-FDA-approved compounds haven’t been tested for safety the way prescription testosterone has.
Stopping suddenly without a plan. Harvard calls it the “testosterone trap”: on treatment, your body stops making its own, so symptoms can rush back if you quit. Plan any stop with your doctor.
Ignoring other causes. Mayo Clinic notes that medications, sleep apnea, thyroid problems, diabetes and depression can cause the same symptoms. Fixing those may help more, and lifestyle steps from our guide to improving sexual health for men are worth trying alongside any treatment.
When to Call a Doctor or 911
Call 911 for chest pain, sudden shortness of breath, coughing blood, one-sided weakness, facial drooping or trouble speaking. These can signal a heart attack, stroke or lung clot.

Call your doctor soon for a swollen, painful leg, a racing or irregular heartbeat, new headaches with high blood pressure readings, trouble urinating, breast lumps, or loud snoring with daytime sleepiness.
If low sex drive is your main complaint, our article on low libido in men covers causes that have nothing to do with testosterone.
Frequently Asked Questions
Is hormone therapy safe for men long term?
Long-term safety beyond a few years isn’t fully known. TRAVERSE followed men for a mean of 33 months and found no rise in heart attacks or strokes. HHS notes that prostate effects may take longer to appear, so ongoing PSA and hematocrit monitoring stays important for as long as you use testosterone.
What happens when a man takes hormone therapy?
With TRT, testosterone rises toward normal and many men notice better sex drive and sexual function. TRAVERSE also showed improved sexual activity and less anemia. At the same time, red blood cell counts rise, blood pressure may increase, sperm production drops, and the body’s own testosterone production slows down.
At what age do most men need TRT?
There’s no set age. Testosterone falls about 1% a year after 30 or 40, per Mayo Clinic, but most men never need treatment. The Endocrine Society advises against routine treatment of all men 65 and older. Diagnosis depends on symptoms plus two low morning tests, not age.
Should men get hormone therapy?
Only men with confirmed low testosterone and matching symptoms should consider it. The Endocrine Society says testosterone isn’t approved for aging, strength, athletic performance or looks. If you’re symptomatic, start with two morning blood tests and a check for other causes like sleep apnea, thyroid disease or depression.
How long can a man stay on hormone therapy?
There’s no fixed limit. Many men stay on it for years, and Harvard warns that stopping can bring symptoms back because natural production slows. UCSF advises reconsidering treatment if you feel no better within about three months of normal levels. Any long-term plan should include yearly labs.
Does testosterone therapy cause heart attacks?
In TRAVERSE, men with low testosterone and high heart risk had heart attacks, strokes or heart deaths at nearly the same rate on testosterone (7.0%) as on placebo (7.3%). That led the FDA to remove the boxed heart warning in 2025. Atrial fibrillation and blood pressure rises are still real concerns.
Does TRT cause prostate cancer?
Current evidence doesn’t show that TRT causes new prostate cancer. In TRAVERSE, cancer rates were 0.5% versus 0.4%. Testosterone can, however, feed a cancer that’s already present and enlarge the prostate. That’s why PSA testing before and during treatment remains standard for men in screening age groups.
Can TRT cause blood clots?
It can raise the risk. Testosterone thickens the blood by boosting red cell production, and TRAVERSE found pulmonary embolism in 0.9% of testosterone users versus 0.5% on placebo. The Endocrine Society says men with a history of blood clots shouldn’t receive testosterone without careful review.
Can TRT cause infertility?
Yes, it often does. It can lower sperm count sharply while you take it, and UCSF says it’s very likely to worsen fertility. The Endocrine Society lists planning to have children as a reason not to use testosterone. Men who need treatment but want children should ask a urologist about fertility-sparing medicines.
What blood tests are needed on TRT?
Expect total testosterone, hematocrit and, if you’re in a screening age group, PSA. The Endocrine Society recommends testosterone and hematocrit checks at 3 to 6 months, then hematocrit yearly. PSA is repeated at 3 to 12 months, then on a normal screening schedule. Blood pressure checks matter too.
Is TRT the same as hormone therapy for prostate cancer?
No. TRT adds testosterone to fix a deficiency. Prostate cancer hormone therapy, called ADT, lowers or blocks testosterone to slow the cancer. The Prostate Cancer Foundation calls it “anti-testosterone therapy.” Its side effects, like hot flashes and bone loss, come from having too little testosterone.
Medical Disclaimer: This article is for general education only and isn’t medical advice. Testosterone is a prescription drug with real risks. Talk with a licensed doctor before starting, stopping or changing any hormone treatment. If you have chest pain, trouble breathing or stroke symptoms, call 911.
References
- Mayo Clinic: Testosterone therapy, potential benefits and risks as you age
- Harvard Health Publishing: Is testosterone therapy safe?
- Endocrine Society: The truth about testosterone treatments (patient guide)
- Endocrine Society: Testosterone therapy in men with hypogonadism, guideline overview (2018)
- MDedge: Clinical guidelines, testosterone therapy in men with hypogonadism
- FDA: FDA issues class-wide labeling changes for testosterone products (Feb. 28, 2025)
- Federal Register: Potential new indication for testosterone replacement therapy (Apr. 20, 2026)
- HHS: Requested updates to testosterone therapy product labels (June 18, 2026)
- TCTMD: Testosterone doesn’t cause CV events in high-risk men with hypogonadism (TRAVERSE)
- MDedge: Big trial reassures on heart safety of testosterone in men
- JAMA: Testosterone prescribing in the United States, 2002-2016
- UCSF Urology: Hypogonadism (low testosterone)
- Prostate Cancer Foundation: Hormone therapy side effects