

For decades, textbooks called borderline personality disorder a “women’s disorder.” Then a national survey of about 34,000 American adults found it in 5.6% of men and 6.2% of women, a gap too small to matter statistically.
That one finding explains a lot about the ASPD vs BPD confusion. The two share a cluster, a reputation, and plenty of myths. Underneath, they run on almost opposite engines.
Table of Contents
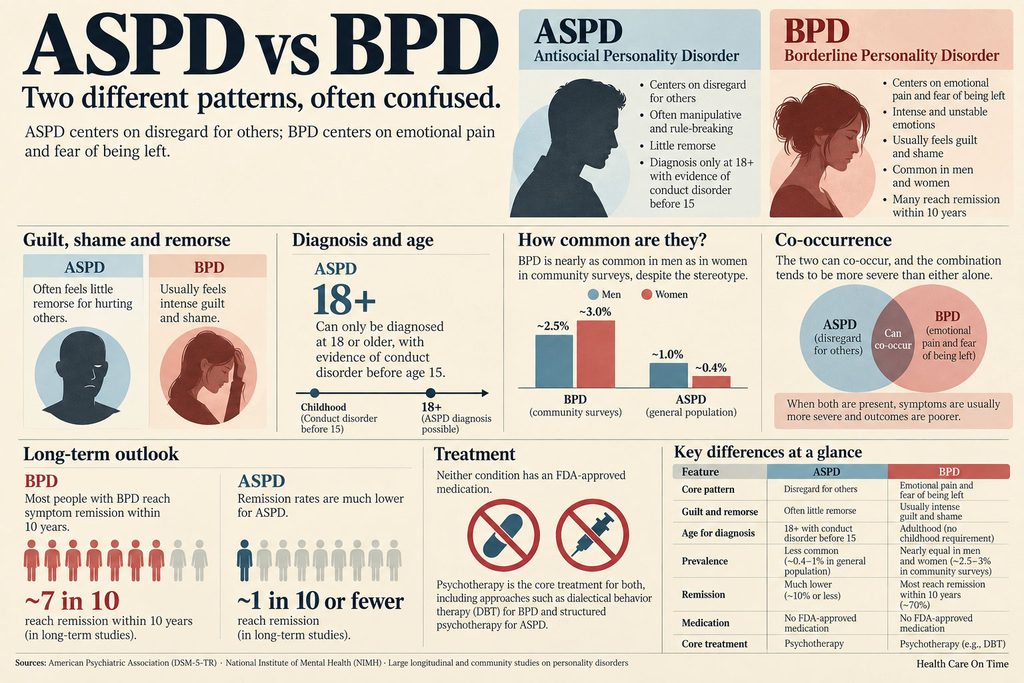
Quick Answer: The difference between ASPD and BPD comes down to feeling. Antisocial personality disorder (ASPD) is a long-term pattern of violating other people’s rights with little remorse, and it requires conduct problems before age 15. Borderline personality disorder (BPD) is a long-term pattern of intense emotions, fear of abandonment, and an unstable sense of self. ASPD involves too little feeling for others; BPD involves too much.
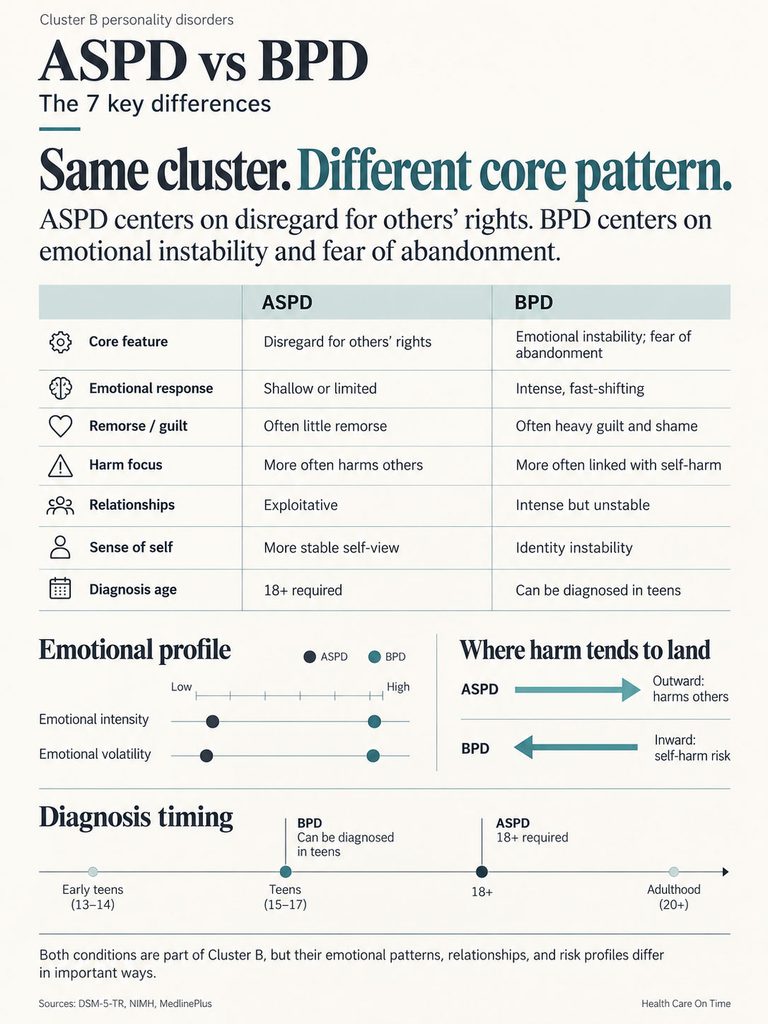
The 7 key differences between ASPD and BPD:
- Emotions: shallow toward others in ASPD; intense and fast-shifting in BPD.
- Remorse: little in ASPD; heavy guilt and shame in BPD.
- Who gets hurt: mostly others in ASPD; often the self in BPD.
- Relationships: used for gain in ASPD; driven by fear of abandonment in BPD.
- Sense of self: stable in ASPD; unstable or empty in BPD.
- Age rules: ASPD only at 18 or older with prior conduct disorder; BPD can be diagnosed in teens.
- Treatment response: weak evidence for ASPD; several proven therapies for BPD.
At a Glance
- ASPD centers on disregard for others; BPD centers on emotional pain and fear of being left.
- People with BPD usually feel intense guilt and shame; people with ASPD often feel little remorse.
- ASPD can only be diagnosed at 18 or older, with evidence of conduct disorder before 15.
- BPD is nearly as common in men as in women in community surveys, despite the stereotype.
- The two can co-occur, and the combination tends to be more severe than either alone.
- Most people with BPD reach symptom remission within 10 years; ASPD remission rates are much lower.
- Neither condition has an FDA-approved medication. Psychotherapy is the core treatment.
What Is Antisocial Personality Disorder (ASPD)?
Antisocial personality disorder is a pattern of disregarding and violating the rights of others that starts in childhood or early adolescence and continues into adulthood. The National Institute of Mental Health notes it is sometimes called sociopathy.

The word “antisocial” trips people up. In everyday speech, it means someone who skips parties. In psychiatry, it means someone who works against society’s rules and other people’s welfare.
The DSM-5-TR Criteria in Plain English
Under the American Psychiatric Association’s DSM-5-TR, a clinician looks for a pattern since age 15 that includes at least 3 of these 7 traits:
- Repeatedly breaking laws or social rules
- Lying, using aliases, or conning others for profit or pleasure
- Acting on impulse without planning ahead
- Irritability and aggression, such as repeated fights or assaults
- Reckless disregard for their own safety or other people’s safety
- Consistent irresponsibility with work or money
- Lack of remorse, often shown as indifference or rationalizing harm
Three more conditions apply. The person must be at least 18. There must be evidence of conduct disorder that began before age 15. And the behavior can’t occur only during an episode of schizophrenia or bipolar disorder.
That childhood link is strong. According to StatPearls, about 25% of girls and 40% of boys with conduct disorder go on to meet ASPD criteria. Children who reach 15 without antisocial behavior do not develop ASPD.
ASPD, Sociopathy, and Psychopathy: Not the Same Word
“Sociopath” is an informal, older label that most people treat as a synonym for ASPD. “Psychopathy” is different. It is a research construct measured with tools like the Psychopathy Checklist, and it adds traits like shallow emotion and grandiose charm.
Most people with psychopathy meet ASPD criteria. Most people with ASPD do not score as psychopaths. Our medical review team flags this distinction because headlines blur it constantly, and that blur feeds stigma.
What Is Borderline Personality Disorder (BPD)?
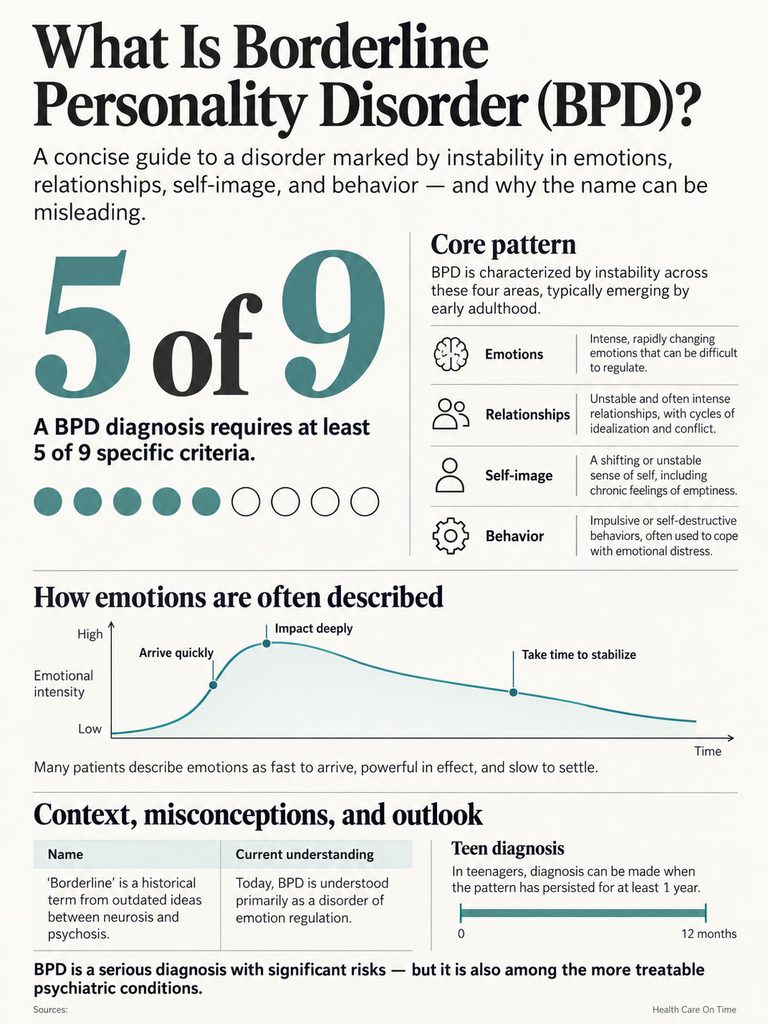
Borderline personality disorder is a pattern of instability in emotions, relationships, self-image, and behavior that usually takes shape by early adulthood. People with BPD often describe emotions that arrive fast, hit hard, and take a long time to settle.
The 9 Criteria
A BPD diagnosis requires at least 5 of these 9 features:
- Frantic efforts to avoid real or imagined abandonment
- Intense, unstable relationships that swing between idealizing and devaluing others
- An unstable sense of identity or self-image
- Impulsivity in at least two areas that can cause harm, such as spending, substance use, or reckless driving
- Recurrent suicidal behavior, threats, or self-harm
- Rapid mood shifts lasting hours to a few days
- Chronic feelings of emptiness
- Intense, hard-to-control anger
- Brief, stress-related paranoia or dissociation
Unlike ASPD, BPD can be diagnosed in teenagers when the pattern has lasted at least a year. The American Psychiatric Association’s 2024 practice guideline covers both adolescents and adults.
Why “Borderline” Is a Misleading Name
The term dates to the early 20th century, when clinicians thought these patients sat on the “border” between neurosis and psychosis. That idea is outdated. Many clinicians and patients now describe BPD as a disorder of emotion regulation.
Patients who reach out to HealthCareOnTime often ask whether the name means the condition is “mild” or “almost” a disorder. It doesn’t. BPD is a full diagnosis with real risks, and also one of the more treatable conditions in psychiatry.
ASPD vs BPD: The 7 Key Differences
Both disorders sit in Cluster B, the “dramatic, emotional, or erratic” group of personality disorders. Both involve impulsivity and damaged relationships. The table below shows where antisocial vs borderline personality disorder split apart.
| Feature | ASPD | BPD | What It Looks Like Day to Day | Clinical Note |
| Core feature | Disregard for others’ rights | Emotional instability and fear of abandonment | Breaking promises vs panicking when a partner is late | The “engine” differs even when behavior looks similar |
| Emotional range | Often shallow or flat in response to others’ pain | Intense, fast-shifting emotions | Calm after a fight vs distress lasting hours | BPD moods shift within hours to days |
| Remorse and guilt | Little or none; harm is often rationalized | Often heavy guilt and shame afterward | “They had it coming” vs harsh self-blame | Lack of remorse is one of the 7 ASPD criteria |
| Main target of harm | Mostly other people | Often the self, sometimes close others | Fraud or fights vs self-harm or reckless spending | Both groups can be aggressive |
| Relationships | Exploitative or shallow; low fear of rejection | Intense, close, and unstable; high fear of rejection | Moving on quickly vs clinging, then pushing away | Idealization and devaluation define BPD |
| Sense of self | Usually stable, sometimes inflated | Unstable, fragmented, or empty | Confident self-story vs not knowing who they are | Chronic emptiness is a BPD criterion |
| Age rules for diagnosis | 18+ only, with conduct disorder before 15 | Can be diagnosed in teens if present 1+ year | A 16-year-old can’t receive an ASPD diagnosis | Teens with antisocial traits get a conduct disorder diagnosis |
| Treatment response | Limited evidence for any therapy | Several proven therapies (DBT, MBT, TFP) | Rarely seeks help voluntarily vs often seeks help for pain | No FDA-approved drug for either condition |
1. Too Little Feeling vs Too Much Feeling
This is the deepest divide. People with ASPD tend to show a narrow emotional response to other people’s distress. People with BPD often feel too much, too quickly, and struggle to come back down.
Think of a thermostat. In ASPD, the dial for other people’s pain is turned low. In BPD, the whole system runs hot and swings wildly.
2. Remorse and Guilt
Lack of remorse is built into the ASPD criteria. Someone with ASPD may hurt a person and explain it away with “they were stupid enough to fall for it.”
Someone with BPD usually does the opposite. After an angry outburst, they often spiral into shame and self-criticism. That guilt is real, even when the behavior repeats.
3. Who Gets Hurt: Others vs Self
ASPD behavior mostly lands on other people: lying, theft, fraud, fights, and reckless risks. Harm to self tends to come as a side effect of risk-taking, not as a goal.
BPD harm often turns inward, through self-harm, substance use, or reckless choices during emotional storms. Anger in BPD is real too, and it often targets the people the person feels closest to.
4. Relationships: Using People vs Fear of Losing Them
In ASPD, relationships often serve a purpose: money, status, sex, or control. Rejection doesn’t sting much, so the person can move on fast.
In BPD, relationships feel like oxygen. Fear of abandonment drives a cycle of closeness, panic, accusation, and repair. A partner may hear “you’re perfect” and “you never cared about me” in the same week.
5. Sense of Self
People with ASPD usually have a steady, sometimes inflated, view of themselves. Their self-story rarely shifts with the mood of the day.
People with BPD often report not knowing who they are. Goals, values, friends, and even style can change suddenly. Chronic emptiness, a hollow “nothing inside” feeling, is one of the nine BPD criteria.
6. Age and Diagnosis Rules
ASPD has the strictest age rules of any personality disorder. The person must be 18 or older and must have shown conduct disorder before 15. Without that childhood history, ASPD can’t be diagnosed, no matter how antisocial adult behavior looks.
BPD has no childhood requirement. It can be diagnosed in adolescence, and many people first meet criteria in their late teens or early twenties.
7. How Each Responds to Treatment
This difference between ASPD and BPD matters most for families. BPD has several therapies with strong research support, and most people improve over time. ASPD treatment research is thin, and people with ASPD rarely seek help on their own.
What Causes ASPD and BPD?
Neither disorder has a single cause. Both appear to grow from a mix of inherited temperament and early environment, but the ingredients differ.

Roots of ASPD
ASPD almost always grows out of childhood conduct disorder. Risk factors include harsh or inconsistent parenting, childhood abuse or neglect, early exposure to violence, and inherited traits like low fear and high thrill-seeking.
Early help changes the path. Family-based treatment for conduct disorder in childhood is one of the best-studied ways to lower the chance of adult ASPD.
Roots of BPD
The most widely used model, from DBT developer Marsha Linehan, describes BPD as an emotionally sensitive temperament meeting an “invalidating” environment, where a child’s feelings are dismissed, punished, or ignored.
Many people with BPD report childhood trauma, but not all do. Our medical reviewers stress this point, because assuming trauma can make people without that history doubt their own diagnosis.
Where ASPD and BPD Overlap (And Why They Get Confused)
Antisocial and borderline personality disorder share real ground. Both involve impulsivity, anger problems, risk-taking, and high rates of alcohol and drug problems. Both can damage careers and families.

Researchers have debated whether they are one underlying problem shaped by gender. A review in Comprehensive Psychiatry concluded they are separate disorders, with emotional instability as the trait that sets BPD apart.
Can You Have Both ASPD and BPD?
Yes. BPD’s most common personality disorder partner is antisocial PD. A 2026 study in Borderline Personality Disorder and Emotion Dysregulation reports co-occurrence of 5.6% to 27% in community samples and more than 50% in clinical and forensic settings.
When both are present, the picture is usually more intense. In that same study, the combined group had the most severe borderline symptoms, the most emotional dysregulation, and the highest impulsivity and anger.
The Gender Bias Problem
Clinicians are human, and stereotypes leak into diagnosis. A 2024 study of psychiatrists found that female patients with ASPD were misdiagnosed with BPD, which can lead to treatment without supporting evidence.
The reverse happens too. When a man and a woman show similar anger and impulsivity, the woman may get labeled borderline while the man gets labeled antisocial.
Men With BPD Who Get Labeled “Antisocial”
Men with BPD are less likely to seek care. They also tend to show more substance use and outward aggression, which can look antisocial at first glance. Across the questions our care team receives, a common theme is a man told he’s “just angry” when the real driver is intense fear of rejection.
A useful test: what happens after the outburst? Shame, panic, and desperate attempts to repair point toward BPD. Indifference points toward ASPD.
How Common Are ASPD and BPD in the US?
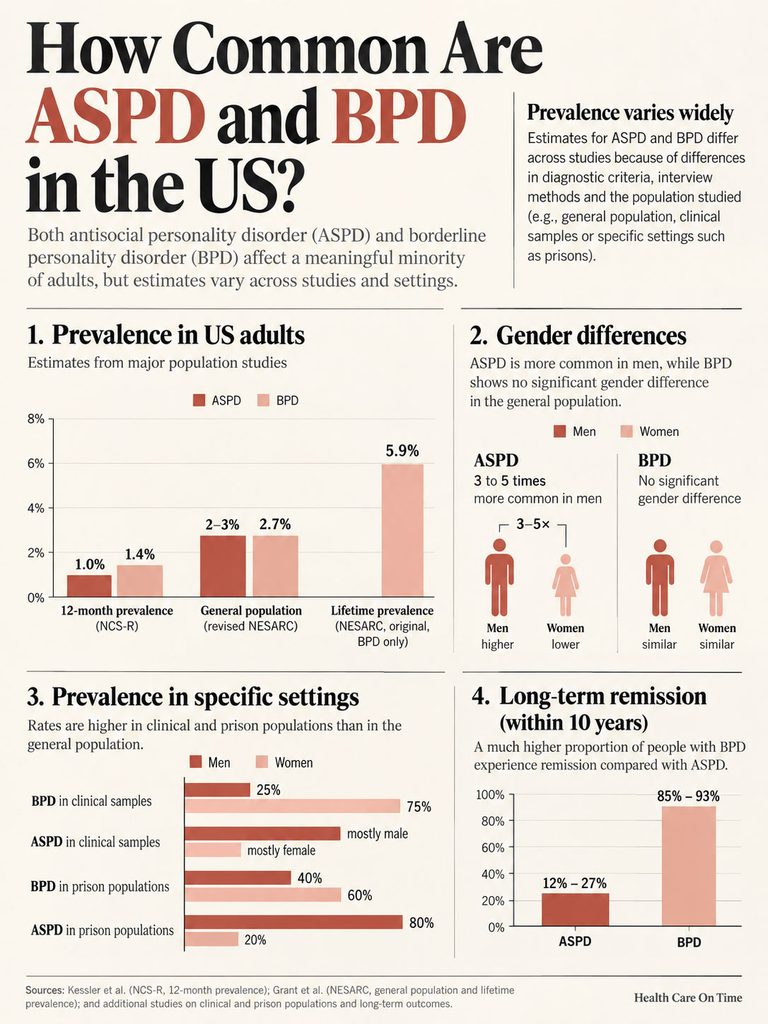
Prevalence numbers for both disorders vary widely, and page after page online quotes them without explaining why. The table below shows the main US estimates side by side.
| Measure | ASPD | BPD | Source |
| 12-month prevalence, US adults | 1.0% | 1.4% (NCS-R) | NIMH; Trull et al., 2010 |
| General population estimate | 2% to 3% | 2.7% (revised NESARC scoring) | StatPearls; Trull et al., 2010 |
| Lifetime prevalence, original NESARC | Not applicable | 5.9% | Grant et al., J Clin Psychiatry, 2008 |
| Men vs women | About 6% vs 2% (3 to 5 times more common in men) | 5.6% vs 6.2% (no significant difference) | StatPearls; Grant et al., 2008 |
| Clinical samples | Mostly male | About 75% female | Grant et al., 2008 |
| Prison populations | Up to 80% of male and 60% of female inmates (late 1990s studies) | Elevated, less studied | StatPearls |
| Long-term remission | 12% to 27% in past studies | 85% to 93% within 10 years | StatPearls; MSAD and CLPS |
Why the Numbers Disagree
Three things drive the spread. First, survey method: lay interviewers using checklists find more cases than trained clinicians. Second, scoring rules: the original NESARC counted a diagnosis if just one trait caused distress, while the revised scoring required distress for each trait, cutting BPD from 5.9% to 2.7%.
Third, setting: clinics see who walks in. Women seek mental health care more often, which explains why clinics see mostly women with BPD while community surveys find a near-even split.
Our medical reviewers recommend treating any single “X% of Americans” figure with caution. A range of roughly 1% to 3% for ASPD and 1.4% to 5.9% for BPD is the honest answer.
ASPD vs BPD Treatment and Long-Term Outlook
Here is where the comparison stops being academic. The two conditions have very different treatment evidence, and that shapes what families can realistically expect.
BPD: The 2024 APA Guideline
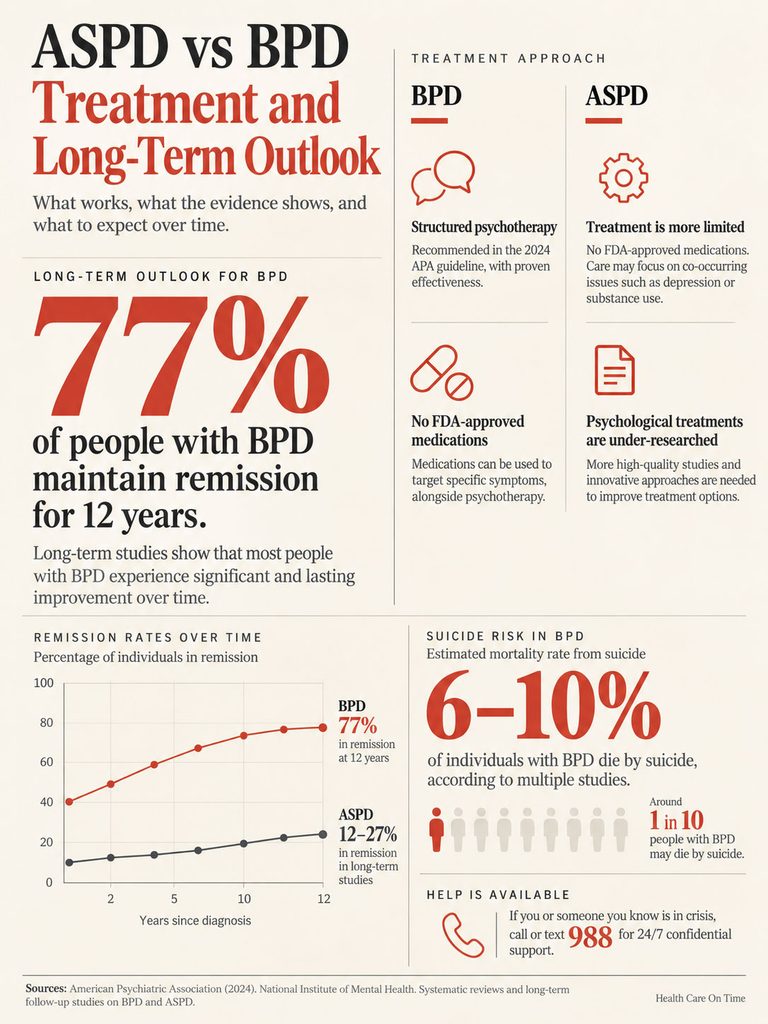
In December 2024, the American Psychiatric Association published its updated BPD practice guideline. Its top recommendation is a structured psychotherapy with research support that targets the core features of the disorder.
Therapies with the strongest evidence include:
- Dialectical behavior therapy (DBT): Teaches skills in emotion regulation, distress tolerance, mindfulness, and relationships. It has the largest evidence base for reducing self-harm.
- Mentalization-based treatment (MBT): Helps people understand their own and others’ mental states, especially under stress.
- Transference-focused psychotherapy (TFP): Uses the therapy relationship to explore and change unstable views of self and others.
- Schema therapy: Targets long-standing beliefs and patterns rooted in early experiences.
Most of these run for a year or longer. Dialectical behavior therapy programs usually combine weekly individual sessions with a weekly skills group.
Medications: No FDA Approval for Either Condition
There is still no FDA-approved medication for BPD, as Psychiatric News points out. The APA suggests any medication be time-limited, aimed at a specific measurable symptom, and used alongside psychotherapy, not instead of it.
ASPD has no FDA-approved medication either. Clinicians may treat co-occurring problems, such as depression, ADHD, or alcohol use disorder, which can lower risk even when core traits remain.
Our lab partners report that baseline blood work often comes before these prescriptions. Several mood stabilizers and antipsychotics require liver, kidney, and metabolic monitoring, so a starting panel gives the prescriber a reference point.
ASPD: What the Evidence Actually Shows
The 2020 Cochrane review of psychological treatments for ASPD included 19 studies. Only 8 of the 18 interventions reported data on the main outcomes, such as aggression and reconviction. The authors concluded that better studies are needed and a new approach may be required.
There are hopeful signs. A trial of patients with both BPD and ASPD tested mentalization-based treatment against structured clinical management, with a focus on anger and aggression. Researchers in England have also run trials adding MBT to probation supervision for men with ASPD.
Treating substance use is one of the most practical steps. Over 90% of people with ASPD have at least one other psychiatric disorder, and alcohol or drug problems are among the most common.
Who Gets Better?
For BPD, the long-term news is surprisingly good. The McLean Study of Adult Development followed nearly 300 people for decades. Principal investigator Mary Zanarini reports that all participants achieved remission, and 77% sustained it for 12 years.
Remission isn’t the same as full recovery, though. Long-term data show diagnostic remission in 85% to 93% within 10 years, but fewer than half reach good social and work functioning in that time. About 30% of those in stable remission had symptoms return by year 10.
For ASPD, StatPearls reports past remission rates of 12% to 27%. Many people “burn out” with age, meaning crime and violence drop. Traits like deceitfulness may remain, just expressed less overtly.
A Note on Safety
BPD carries a serious suicide risk. A review in Medicina estimates up to 10% of people with BPD die by suicide, and a 2026 synthesis puts the figure near 6%. The same research shows most people with BPD improve over time, and those who recover are far less likely to die this way.
If you or someone you love is thinking about suicide, call or text 988 to reach the 988 Suicide and Crisis Lifeline. Help is available 24 hours a day.
4 Myths About ASPD and BPD
Myth 1: “BPD Is a Women’s Disorder”
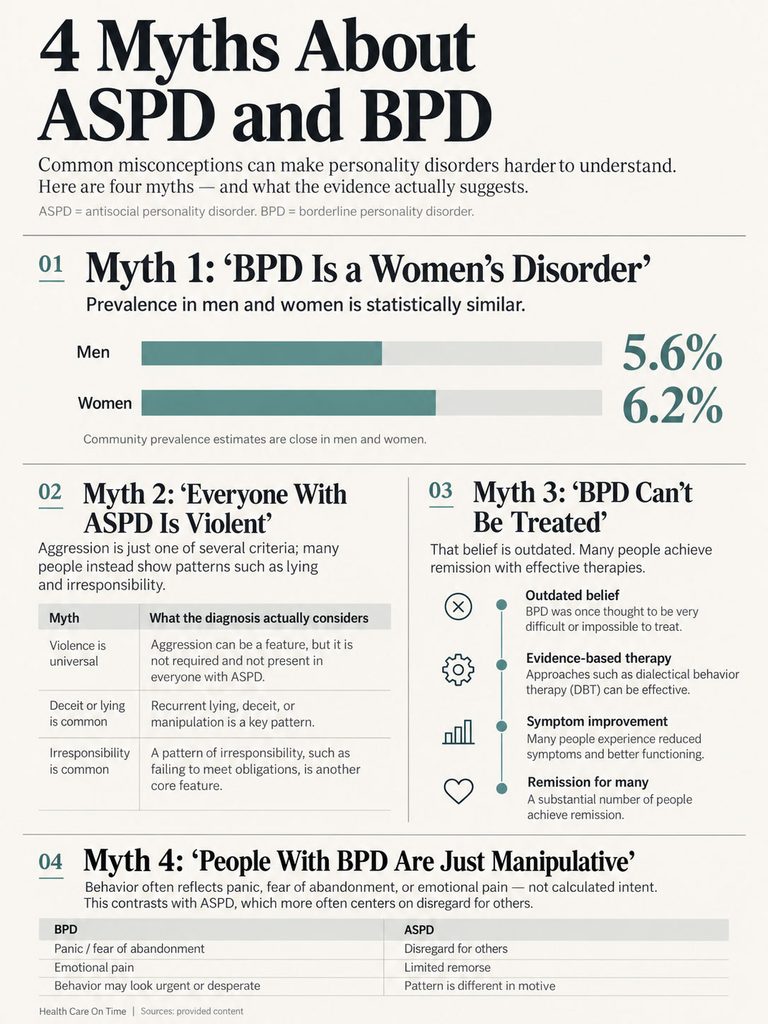
Community data don’t support this. The NESARC survey found BPD in 5.6% of men and 6.2% of women, a difference that wasn’t statistically significant. Women are simply more likely to be diagnosed in clinics.
Myth 2: “Everyone With ASPD Is Violent”
Aggression is one of seven possible criteria, not a requirement. Many people with ASPD show the pattern through lying, irresponsibility, and exploitation, not violence. Movie portrayals of serial killers distort the picture badly.
Myth 3: “BPD Can’t Be Treated”
This belief was standard in the 1980s and is now outdated. Long-term studies show most people reach remission, and several therapies have strong evidence. Some clinicians describe BPD as one of the more treatable serious mental health conditions.
Myth 4: “People With BPD Are Just Manipulative”
Behavior that looks manipulative in BPD usually comes from panic, not strategy. A barrage of texts at 2 a.m. is typically fear of abandonment talking. In ASPD, manipulation tends to be calculated and goal-driven, which is a meaningful difference.
What to Do If You Recognize These Signs

Reading a list of traits can raise questions about yourself, a partner, or a child. Only a licensed clinician can diagnose a personality disorder, usually after a structured interview over more than one visit. The table below offers practical next steps.
| Scenario | Recommended Action | Who to Contact |
| Thoughts of suicide or self-harm | Get support today; don’t wait for an appointment | Call or text 988; call 911 for immediate danger |
| You see BPD traits in yourself | Ask for a full evaluation and a referral to DBT or another structured therapy | Primary care provider, psychiatrist, or licensed psychologist |
| A partner who frightens or controls you | Prioritize your safety before trying to “diagnose” them | National Domestic Violence Hotline: 1-800-799-7233 |
| A teen with lying, fighting, cruelty, or rule-breaking | Request an evaluation for conduct disorder; family-based therapy works best early | Pediatrician or child and adolescent psychiatrist |
| A past diagnosis that doesn’t fit | Request a second opinion with a structured diagnostic interview | Psychiatrist or psychologist who specializes in personality disorders |
| Alcohol or drug use alongside these traits | Treat both at once; substance use worsens both disorders | SAMHSA National Helpline: 1-800-662-4357 |
| Family member with BPD or ASPD | Learn boundaries and coping skills for yourself | NAMI HelpLine: 1-800-950-6264 |
Ruling Out Medical Causes First
Personality disorders are diagnosed only when a medical condition or substance doesn’t better explain the behavior. Head injuries, thyroid disease, seizure disorders, and drug or alcohol effects can all change mood, impulse control, and judgment.
Patients booking tests with us often ask which labs make sense. Clinicians commonly order a thyroid panel (TSH), a complete blood count, a metabolic panel, and a urine drug screen. These tests can’t diagnose ASPD or BPD, but they can rule out look-alikes.
How to Find a Qualified Therapist in the US
Start with your health plan’s behavioral health directory. Under federal mental health parity law, most plans must cover mental health care on terms similar to medical care.
Behavioral Tech, the training group founded by DBT’s developer, lists DBT-trained clinicians. Community mental health centers offer sliding-scale fees, and FindTreatment.gov lists SAMHSA-supported programs. Telehealth has widened access, especially in rural areas.
Frequently Asked Questions
Can someone have both ASPD and BPD?
Yes. Antisocial personality disorder is the personality disorder most often found alongside BPD. Studies report co-occurrence in 5.6% to 27% of community samples and over half of clinical and forensic samples. People with both tend to have more intense anger, impulsivity, and emotional swings than people with either disorder alone.
Is BPD more common in women than men?
Not in the general population. A large US survey found BPD in 5.6% of men and 6.2% of women, with no meaningful difference. Clinics see more women because women seek mental health care more often, and men with BPD are sometimes misdiagnosed with ASPD or substance use disorders.
Which is worse, ASPD or BPD?
Neither is “worse” in a simple sense; they cause different harms. BPD carries higher suicide and self-harm risk, while ASPD carries more legal and violence-related risk to others. BPD has far better treatment evidence, with most people reaching remission within 10 years, while ASPD remission rates are much lower.
Can BPD turn into ASPD?
No. ASPD requires conduct disorder that started before age 15, so it can’t develop out of adult BPD. What can happen is that a person has both disorders, or that BPD in men gets mistaken for ASPD because of outward anger and substance use. A careful history usually clears this up.
Do people with BPD feel empathy?
Usually, yes. Many people with BPD are highly tuned to others’ moods and sensitive to rejection. Research suggests that under intense stress, their ability to read others accurately can drop, and neutral faces may seem hostile. This differs from ASPD, where indifference to others’ pain tends to be steady.
Do people with ASPD feel guilt?
Lack of remorse is one of the seven ASPD criteria, so many people with ASPD feel little guilt about harming others. They may express regret about consequences, such as getting caught. Not every person with ASPD meets this criterion, since a diagnosis requires only three of the seven traits.
Is ASPD the same as being a sociopath?
Mostly. “Sociopath” is an informal, older term that NIMH notes is often used for ASPD. “Psychopath” is different: psychopathy is a research measure with extra traits like shallow emotion and grandiose charm. Most people with ASPD are not psychopaths, even though most psychopaths meet ASPD criteria.
Is there medication for BPD?
No medication is FDA-approved for BPD. The American Psychiatric Association’s 2024 guideline names structured psychotherapy as the core treatment. Medications may be used for a limited time to target a specific symptom, such as severe mood swings or co-occurring depression, but only alongside therapy.
Can a teenager be diagnosed with ASPD or BPD?
A teenager can be diagnosed with BPD if symptoms have lasted at least one year. ASPD can’t be diagnosed before age 18. Teens with serious antisocial behavior receive a conduct disorder diagnosis instead, and early family-based treatment gives the best chance of preventing adult ASPD.
Is BPD caused by trauma?
Trauma is a common risk factor but not the only cause. Many people with BPD report childhood abuse, neglect, or invalidation, yet some don’t. The leading model describes BPD as an emotionally sensitive temperament meeting an environment that dismisses or punishes emotions. Inherited traits likely play a meaningful role.
How is ASPD diagnosed?
A psychiatrist or psychologist conducts a detailed interview, often with records or family input, since self-report can be unreliable. They confirm the person is 18 or older, meets at least three of seven traits, and had conduct disorder before 15. They also rule out bipolar disorder, schizophrenia, and substance effects.
Can BPD go away?
For most people, symptoms ease substantially. Long-term studies show diagnostic remission in 85% to 93% of people within 10 years, and relapse after long remission is uncommon. Full recovery, meaning stable relationships and work, takes longer and is less certain, which is why ongoing therapy and support matter.
Disclaimer: This article is for educational purposes only and is not a substitute for professional diagnosis or treatment. Personality disorders can only be diagnosed by a licensed mental health professional. If you or someone you know is in crisis or thinking about suicide, call or text 988 to reach the 988 Suicide and Crisis Lifeline, available 24/7. If there is immediate danger, call 911.
References
- National Institute of Mental Health: Antisocial Personality Disorder Statistics
- Grant BF et al. Prevalence, Correlates, Disability, and Comorbidity of DSM-IV Borderline Personality Disorder (NESARC Wave 2). J Clin Psychiatry. 2008
- Trull TJ et al. Revised NESARC Personality Disorder Diagnoses: Gender, Prevalence, and Comorbidity
- StatPearls: Antisocial Personality Disorder (Nursing)
- StatPearls: Antisocial Personality Disorder
- Antisocial and Borderline Personality Disorders Revisited. Comprehensive Psychiatry
- Comorbidity of Borderline With Antisocial and Narcissistic Personality Disorders: A Multimethod Study. 2026
- Gender Bias of Antisocial and Borderline Personality Disorders Among Psychiatrists. 2024
- American Psychiatric Association: Updated Practice Guideline on the Treatment of Borderline Personality Disorder
- Psychiatric News: Borderline Personality Disorder, Medications, and Psychotherapy
- Gibbon S et al. Psychological Interventions for Antisocial Personality Disorder. Cochrane Database Syst Rev. 2020
- Bateman A et al. MBT vs Structured Clinical Management for Comorbid BPD and ASPD. BMC Psychiatry. 2016
- McLean Hospital: Lessons Learned From a Decades-Long BPD Study
- Soloff PH. Diagnostic Remission and Psychosocial Recovery in BPD
- Paris J. Suicidality in Borderline Personality Disorder. Medicina. 2019
- Phenotypes and Trajectories of Suicidality in Borderline Personality Disorder. European Psychiatry. 2026
- 988 Suicide and Crisis Lifeline
- FindTreatment.gov (SAMHSA)





