“It hurts when you press on it, so it can’t be your heart.” Millions of Americans use this home test every year. It’s one of the least reliable tests in all of chest pain medicine.
Table of Contents
Most sharp sternum pain really does come from the chest wall, not the heart. But “most” isn’t “all,” and the gap between those two words is where people get hurt. This guide covers the 11 main causes, the numbers doctors actually use, and what to do next.
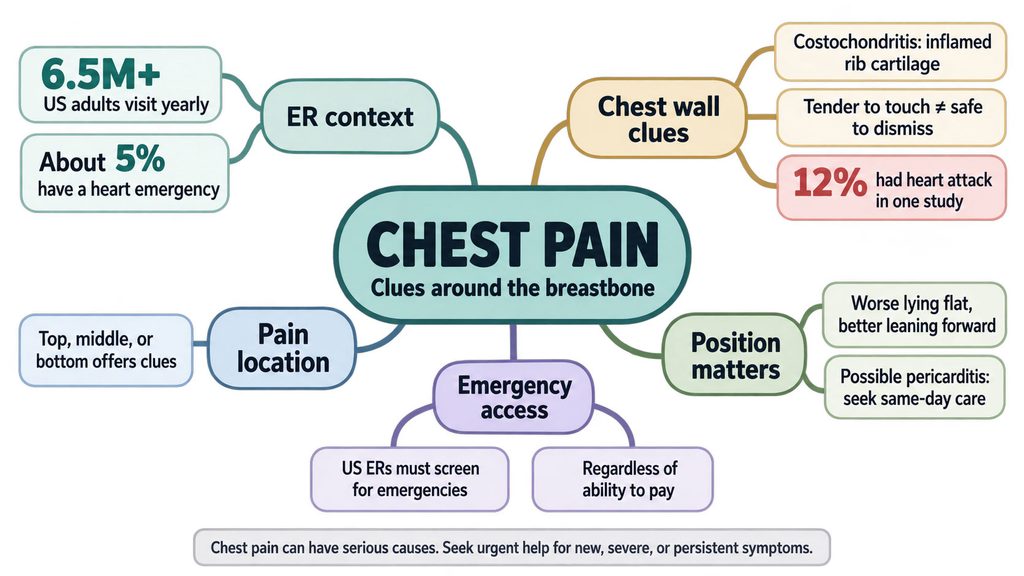
Quick Answer: Sharp sternum pain is most often caused by costochondritis or a strained chest muscle, especially if it hurts to press, breathe deeply, or twist. Sharp pain lowers the odds of a heart attack but does not rule one out. Call 911 if the pain comes with pressure, shortness of breath, sweating, nausea, fainting, or spreads to your arm, jaw, or back.
Call 911 right away if sternum pain comes with any of these:
- Pressure, squeezing, or heaviness in the chest
- Pain spreading to one or both arms, shoulders, the jaw, or the back
- Shortness of breath
- Cold sweat, nausea, or vomiting
- Lightheadedness or fainting
- Pain that started with physical effort
- Sudden, tearing pain that goes through to the back
At a Glance
- Chest pain sends more than 6.5 million US adults to the emergency room each year, and only about 5% of them have a heart attack or related heart emergency.
- Costochondritis (inflamed rib cartilage) is the most common cause of sharp sternum pain.
- Pain you can press on makes a heart attack less likely, but in one study, 12% of ER patients with chest wall tenderness were also having a heart attack.
- Where the pain sits (top, middle, or bottom of the breastbone) gives strong clues.
- Pain that is worse lying flat and better leaning forward may mean pericarditis, which needs a same-day visit.
- Federal law requires US emergency rooms to check you for an emergency whether or not you can pay.
What Your Sternum Is (And Why Pain There Is So Confusing)
Your sternum, or breastbone, is the flat bone in the center of your chest. Your ribs attach to it through strips of flexible cartilage, and your collarbones attach at the top.

Right behind it sit your heart, your esophagus (food pipe), the large blood vessels, and the front edges of both lungs. That crowded neighborhood is exactly why sternum pain is so hard to read.
Three Zones, Three Sets of Causes
Doctors often think about the sternum in three parts. Each zone tends to point toward different problems.
- Top (where the collarbones meet the sternum): sternoclavicular joint strain, arthritis, or injury. Pain often gets worse when you reach overhead.
- Middle (the long body of the sternum): costochondritis, muscle strain, bruising, reflux, and heart or lung causes.
- Bottom (the small tip called the xiphoid): xiphoid pain, reflux, and stomach problems that feel like chest pain.
Why the Heart, Lungs, and Gut All “Report” to the Same Spot
Your internal organs don’t have precise pain maps the way your skin does. Signals from the heart, esophagus, and lungs travel along shared nerve pathways into the spinal cord.
Your brain can’t always tell which organ sent the signal, so it points you to the middle of your chest. That’s why reflux can feel like a heart problem, and a heart problem can feel like indigestion.
Sharp Sternum Pain: When to Call 911 Right Now
The seven warning signs above override everything else in this article. If you have any of them, stop reading and call 911. Don’t drive yourself.

Paramedics can run an ECG in your living room and send it ahead to the hospital. Every minute of delay during a heart attack means more heart muscle lost.
Why “Sharp” Lowers the Odds but Doesn’t Clear You
Doctors use a tool called a likelihood ratio to judge how much a symptom changes the odds of a diagnosis. A number above 1 raises the odds. A number below 1 lowers them.
A major review in JAMA by Swap and Nagurney found that pain that is stabbing, gets worse with breathing, changes with position, or can be reproduced by pressing has likelihood ratios of 0.2 to 0.3 for a heart emergency. That’s a real drop in risk.
The same review found that pain spreading to one or both shoulders or arms, or pain brought on by exertion, carries likelihood ratios of 2.3 to 4.7. If your sharp pain also spreads to your arm, the reassuring part is outweighed.
Our medical review team treats “sharp” as one clue among many, never as a verdict. A 25-year-old with sharp pain after moving furniture is in a very different place than a 62-year-old with diabetes and the same pain.
Women, Diabetes, and Older Adults: The “Atypical” Label Problem
For decades, chest pain was sorted into “typical” and “atypical.” The 2021 AHA/ACC chest pain guideline told doctors to stop using “atypical.”
The American Heart Association explained that women more often report extra symptoms such as nausea, fatigue, and shortness of breath. The “atypical” label was too often read as “not the heart,” which delayed care for women.
The same caution applies to people with diabetes and adults over 65. Nerve changes can dull the classic crushing pain, so a heart attack may show up as tiredness, breathlessness, or an odd ache.
11 Causes of Sharp Sternum Pain, Ranked From Common to Rare
Patients who book chest pain workups through HealthCareOnTime often ask for one simple answer. The honest answer is a list, ranked by how often each cause shows up and how dangerous it is.

Chest Wall Causes
1. Costochondritis
Costochondritis is inflammation of the cartilage that joins your ribs to your sternum. According to Mayo Clinic, it most often affects the upper ribs on the left side, and the pain can feel sharp, aching, or like pressure.
The pain gets worse with deep breaths, coughing, sneezing, or twisting. Pressing where the rib meets the breastbone usually brings it on. AAFP notes it’s most common between ages 40 and 50, with a slight lean toward women.
The cause is often unclear. Heavy lifting, a long coughing illness, or a new workout can set it off.
2. Muscle Strain
The chest muscles attach to the sternum and ribs. A hard coughing fit, bench pressing, carrying boxes, or a sudden twist can strain them.
Strain pain usually starts within a day of the activity. It hurts to move your arms or twist, and it feels sore rather than deep.
3. Sternal Bruise or Fracture
A car crash, especially the force of a seat belt, a fall, or a sports hit can bruise or crack the sternum. The pain is sharp right away and worse with breathing, coughing, and lying face down.
Any sternum pain after real trauma needs an exam and usually an X-ray. A hard enough blow can also bruise the heart muscle underneath.
4. Sternoclavicular Joint Problems
The sternoclavicular joint is where your collarbone meets the top of your sternum. Arthritis, overuse, or an injury can inflame it.
You may notice swelling or a bump at the top of the breastbone. Pain rises when you shrug, reach overhead, or sleep on that side.
5. Xiphoid Pain (Xiphodynia)
The xiphoid is the small, pointed tip at the bottom of your sternum. When it’s irritated, you feel sharp, local pain just above the stomach.
Bending forward, a big meal, or a tight waistband can trigger it. People often mistake it for a stomach problem.
6. Tietze Syndrome
Tietze syndrome looks like costochondritis, with one key difference: visible swelling at the rib-sternum joint. It usually affects one spot, often the second or third rib, and is more common in people under 40.
It’s harmless but can last weeks to months. Swelling at the joint deserves a doctor’s look to confirm the diagnosis.
Digestive Causes
7. Acid Reflux, Esophageal Spasm, and Pill Esophagitis
Reflux usually causes burning behind the breastbone after meals or when lying down. Esophageal spasm is different: it can cause sudden, sharp, squeezing pain that feels very much like a heart problem.
Pill esophagitis is a cause most websites skip. A pill that sticks in the esophagus can burn a small sore and cause sharp pain behind the sternum, often worse when you swallow.
Doxycycline, NSAIDs, potassium pills, and some bone-density drugs are common culprits. Taking pills with a full 8-ounce glass of water and staying upright for 30 minutes lowers the risk.
Lung Causes
8. Pleurisy, Pneumonia, and a Collapsed Lung
Pleurisy is inflammation of the lining around the lungs. It causes a sharp, stabbing pain that spikes with every breath, often after a viral infection.
Pneumonia adds fever, cough, and fatigue. A collapsed lung (pneumothorax) causes sudden sharp pain plus shortness of breath and is more common in tall, thin young men and people who smoke.
Heart and Blood Vessel Causes
9. Pericarditis
Pericarditis is inflammation of the sac around the heart. Its pain is sharp, sits behind the sternum, and has a signature pattern: worse lying flat, better sitting up and leaning forward.
It often follows a viral illness. It isn’t a heart attack, but it needs a same-day evaluation, because fluid can build up around the heart.
10. Heart Attack, Pulmonary Embolism, and Aortic Dissection
These are the “can’t miss” causes. A heart attack more often feels like pressure or squeezing, but it can feel sharp, especially in women and older adults.
A pulmonary embolism (a blood clot in the lung) causes sudden sharp pain with breathing plus shortness of breath. It’s more likely after a long flight, surgery, new leg swelling, pregnancy, or estrogen use.
Aortic dissection is a tear in the body’s main artery. It’s rare, but the pain is sudden, severe, and often described as ripping through to the back. All three need 911.
Other Causes
11. Panic Attacks and Shingles
Panic attacks can cause sharp chest pain, a racing heart, tingling hands, and a sense of doom. The pain is real, even though the heart is healthy. A first episode should always be checked before it’s labeled anxiety.
Shingles is the sneaky one. Burning or sharp pain along one side of the chest can appear two to three days before the rash does.
How the Main Causes Compare
| Cause | What the Pain Feels Like | What Makes It Worse | Key Clue | Urgency |
| Costochondritis | Sharp or aching, left side of sternum | Deep breath, pressing, twisting | Tender where ribs meet sternum | Routine visit if lasting |
| Muscle strain | Sore, sharp with movement | Arm movement, twisting | Recent lifting, coughing, or workout | Home care |
| Sternal fracture | Sharp, immediate | Breathing, lying face down | Recent crash, fall, or hit | Same day, urgent care or ER |
| Reflux or spasm | Burning or squeezing | Meals, lying down | Sour taste, relief from antacids | Routine visit |
| Pleurisy | Stabbing | Every breath in | Recent cold or flu | Same-day visit |
| Pericarditis | Sharp, behind sternum | Lying flat | Better leaning forward | Same day |
| Heart attack | Pressure, squeezing, sometimes sharp | Exertion | Spreads to arm or jaw, sweating | 911 |
| Pulmonary embolism | Sudden, sharp | Breathing in | Shortness of breath, recent travel or surgery | 911 |
| Panic attack | Sharp, tight | Stress | Racing heart, tingling, fear | After heart ruled out |
The Press Test Myth: What the Research Really Shows
The belief that “tender to touch means not the heart” feels logical. The data tells a messier story.

30% Had Costochondritis, and Some Still Had Heart Attacks
In a prospective emergency department study by Disla and colleagues, researchers examined 122 people with chest pain. Of those, 36 (30%) had costochondritis, and most were women.
Here’s the part competitors leave out. The heart attack rate in the costochondritis group was 6%, compared with 28% in the group without chest wall tenderness. Lower, yes. Zero, no.
A later AAFP review cites a study where 12% of ER patients with chest pain and chest wall tenderness were also having a heart attack. You can have a sore chest wall and a heart attack at the same time.
In cases reviewed by our medical team, this is the single most common false reassurance people describe. They pressed, it hurt, and they waited hours they didn’t have.
Pain Features That Raise vs Lower Heart Risk
Think of symptoms as weights on a scale. Sharp, pressable, breath-related pain adds weight to the “chest wall” side.
Pain that spreads to the arms, starts with exertion, or comes with sweating or nausea adds weight to the “heart” side. When both kinds show up together, the heart side wins, and you call 911.
What These Numbers Can and Can’t Tell You
Honest data comes with limits. The Disla study was small (122 people), took place at one New York City hospital, and was published in 1994, before high-sensitivity troponin tests existed.
The 12% figure comes from a single study, and the JAMA likelihood ratios pool research from 1970 to 2005. Today’s ER tests catch smaller heart injuries, so exact percentages would likely look different now.
What hasn’t changed is the direction of the evidence. Every one of these sources agrees that chest wall tenderness lowers the odds of a heart attack without removing them. That is the takeaway worth keeping.
Sharp Chest and Sternum Pain in the US: Key Numbers
| Statistic | Figure | Source |
| Adult ER visits for chest pain per year | More than 6.5 million | 2021 AHA/ACC Chest Pain Guideline |
| Share of all US ER visits | 4.7% | 2021 AHA/ACC Chest Pain Guideline |
| Outpatient visits for chest pain per year | Nearly 4 million | 2021 AHA/ACC Chest Pain Guideline |
| ER chest pain patients with acute coronary syndrome | 5.1% | 2021 AHA/ACC Chest Pain Guideline |
| ER chest pain patients with a noncardiac cause | More than half | 2021 AHA/ACC Chest Pain Guideline |
| ER chest pain patients with costochondritis | 30% (36 of 122) | Disla, Arch Intern Med 1994 |
| Heart attack rate, costochondritis vs no tenderness | 6% vs 28% | Disla, Arch Intern Med 1994 |
| Chest-wall-tender ER patients also having a heart attack | 12% | AAFP Rapid Evidence Review, 2021 |
| Costochondritis patients with chest pain after 1 year | 55% (11 of 21) | Disla, Arch Intern Med 1994 |
| Likelihood ratio: sharp, pressable, positional pain | 0.2 to 0.3 | Swap and Nagurney, JAMA 2005 |
| Likelihood ratio: pain spreading to arm(s) or with exertion | 2.3 to 4.7 | Swap and Nagurney, JAMA 2005 |
Special Situations: Pregnancy, Teens, and After Chest Surgery
Some groups need a different threshold for getting checked. These are the three our medical reviewers flag most often.

Pregnancy and the First Months After Birth
Heartburn is very common in pregnancy and often causes burning behind the sternum. But pregnancy and the weeks after delivery also raise the risk of blood clots in the lungs.
A less known cause is spontaneous coronary artery dissection (SCAD), a tear in a heart artery that can strike healthy young women, including around childbirth. Sharp chest pain with shortness of breath during pregnancy or postpartum needs 911, not a wait-and-see approach.
Teens and Young Adults
In children and teens, chest pain is rarely from the heart. Muscle strain, costochondritis, and anxiety are far more common.
Still, chest pain that happens during sports, causes fainting, or comes with a family history of sudden death at a young age needs a same-day evaluation. Those can point to rare inherited heart conditions.
After Heart or Chest Surgery
People who’ve had open-heart surgery have a sternum that was cut and wired closed. Some soreness during healing is normal.
Call your surgeon the same day for fever, redness, drainage from the incision, or a clicking or shifting feeling in the breastbone. Those can signal infection or a sternum that isn’t healing properly.
How Doctors Figure Out the Cause
Knowing what happens next makes the visit less scary. It also helps you ask better questions.

In the ER
The 2021 guideline recommends an ECG within about 10 minutes of arrival for chest pain. You’ll also get a blood test for troponin, a protein released when heart muscle is damaged, and the guideline prefers the high-sensitivity version.
Many hospitals then use a scoring tool such as the HEART score. It combines your history, ECG, age, risk factors, and troponin to sort you into low, intermediate, or high risk.
Low-risk patients can often go home the same day with follow-up. Depending on your score, you may get a CT scan of the heart arteries or a stress test.
At Primary Care or Urgent Care
For mild, clearly chest-wall pain, a doctor will press along your ribs and sternum, listen to your heart and lungs, and ask about recent activity. StatPearls advises that an ECG and chest X-ray be considered for all adults with chest pain.
Blood work can help in some cases. A CBC checks for infection or anemia, and a CRP test measures inflammation. Across the patients we serve, these two tests are the most common add-ons ordered for unexplained chest wall pain.
How Costochondritis Is Diagnosed
There’s no single test that proves costochondritis. It’s a diagnosis made by exam, after serious causes are ruled out.
Doctors look for tenderness at more than one rib joint, pain that matches your usual pain, and no red flags. If there’s visible swelling, the label becomes Tietze syndrome.
ER, Urgent Care, or Telehealth? Choosing the Right Door
Cost worries keep many Americans home when they shouldn’t be. Here’s what to know before you decide.

Your Right to Emergency Care
A federal law called EMTALA requires any US hospital ER that accepts Medicare to screen you for an emergency and stabilize you, whether or not you have insurance or can pay. Billing questions come later.
Matching the Setting to Your Symptoms
- ER (by ambulance): any red flag, new severe pain, or pain after trauma. Uninsured ER visits for chest pain often run $1,500 to $3,000 or more once testing is added; insured patients typically pay their plan’s ER copay or deductible.
- Urgent care: mild pain with no red flags, especially after a clear strain. Visits often cost $100 to $250 without insurance. Many urgent care centers can’t run troponin tests, so they’ll send heart concerns to the ER.
- Telehealth: follow-up on known costochondritis, reflux questions, or medication advice. It can’t rule out a heart attack, because it can’t do an ECG or blood test.
- Primary care: pain that’s been mild and steady for more than a week or two.
Treatment and Relief for Chest Wall Sternum Pain
Once your doctor confirms the pain is from the chest wall, treatment is simple. The goal is to calm the inflammation and give the tissue time to heal.

Over-the-Counter Pain Relievers
NSAIDs such as ibuprofen (Advil, Motrin) and naproxen (Aleve) are the usual first choice. Follow the label: OTC ibuprofen is typically 200 to 400 mg every 4 to 6 hours, with no more than 1,200 mg in 24 hours unless a doctor advises otherwise.
OTC labels also say not to use them for pain longer than 10 days without talking to a doctor. Ask first if you have kidney disease, stomach ulcers, heart failure, or take blood thinners.
Acetaminophen (Tylenol) is an option when NSAIDs aren’t safe. It eases pain but doesn’t reduce inflammation.
Heat, Ice, and Gentle Movement
Ice for 15 to 20 minutes can help in the first 48 hours after a strain. After that, a heating pad on low often feels better for tight muscles.
A gentle doorway stretch, arms on the frame and leaning forward slowly, can ease stiffness. Stop if it causes sharp pain.
Change the Activity That Triggers It
Take a break from heavy lifting, pushups, bench press, and rowing for a few weeks. If a cough started it, treating the cough is part of treating the chest.
People often return to the gym too soon. Coming back at half your usual weight and building up over two to three weeks lowers the chance of a flare.
How Long It Really Lasts
Most chest wall strains feel better in one to three weeks. Mayo Clinic says costochondritis can take several weeks or more to improve.
The longer view is less rosy than most sites suggest. In the Disla study, 55% of costochondritis patients still had chest pain a year later, though only a third still had clear costochondritis. If pain lasts beyond six to eight weeks, a physical therapist or a steroid injection may help, and your doctor should take a second look.
What to Do Next: A Step-by-Step Plan
Here’s how to act in the moment, based on what patients commonly ask us after a scare.

The First 10 Minutes at Home
- Check for the 7 red flags. If any are present, call 911 now.
- Follow the 911 dispatcher’s instructions. They may tell you to chew one regular 325 mg aspirin. Don’t take aspirin on your own if you’re allergic to it, have a bleeding problem, or take a blood thinner.
- If there are no red flags, sit down and notice the pattern. Does it change when you breathe, move, press, or lean forward?
- Write down when it started, what you were doing, and what makes it better or worse.
- If the pain is new, severe, or you’re unsure, get checked the same day. Being wrong at the ER costs a few hours; being wrong at home can cost much more.
What to Tell the Doctor
Clear details speed up the right answer. Bring this short script:
- Where exactly it hurts (top, middle, or bottom of the sternum)
- What it feels like (sharp, burning, pressure, tearing)
- What makes it worse (breathing, moving, eating, lying down, effort)
- Any spread to the arm, jaw, back, or belly
- Recent lifting, coughing, illness, travel, surgery, or injury
- Your medicines, including new pills and supplements
Scenario and Action Guide
| Scenario | What It May Mean | Recommended Action |
| Sharp pain plus pressure, sweating, or pain down the arm | Possible heart attack | Call 911 now |
| Sudden sharp pain with breathing plus shortness of breath after a long flight or surgery | Possible pulmonary embolism | Call 911 now |
| Sudden tearing pain that goes through to the back | Possible aortic dissection | Call 911 now |
| Sharp pain worse lying flat, better leaning forward, after a cold | Possible pericarditis | Same-day urgent care or ER |
| Sternum pain after a car crash or hard fall | Possible fracture or heart bruise | Same-day urgent care or ER |
| Pain you can press on after moving furniture, no other symptoms | Muscle strain or costochondritis | Home care, see a doctor if not better in 1 to 2 weeks |
| Burning or sharp pain after meals, sour taste | Reflux or esophageal spasm | Primary care visit; ER if pain is severe or new |
| Sharp pain when swallowing after starting a new pill | Pill esophagitis | Call your doctor or pharmacist within 1 to 2 days |
| One-sided burning pain, rash appears days later | Shingles | Primary care within 72 hours of rash for antiviral treatment |
Frequently Asked Questions
How Can You Tell If Sternum Pain Is Your Heart?
You can’t be certain at home. Pain that is sharp, changes with breathing, or hurts when pressed makes a heart cause less likely. Pain with pressure, sweating, nausea, shortness of breath, or spread to the arm or jaw makes it more likely. Only an ECG and a troponin blood test can answer the question.
Why Does the Sternum Hurt When Pressed?
Tenderness to touch usually means the chest wall is involved, most often costochondritis or a strained muscle. The cartilage where your ribs meet the breastbone is inflamed and sensitive. Still, research shows some people with a tender chest wall are having a heart attack at the same time, so tenderness alone doesn’t rule out the heart.
Why Does the Sternum Hurt When Breathing In?
Pain that spikes with a deep breath usually comes from the chest wall or the lining of the lungs. Costochondritis, muscle strain, and pleurisy are common causes. If breathing pain comes with shortness of breath, a fast heartbeat, or recent travel or surgery, call 911, since a blood clot in the lung is possible.
Can Anxiety Cause Sharp Sternum Pain?
Yes. Panic attacks can cause sharp or tight chest pain along with a racing heart, fast breathing, tingling, and a feeling of doom. Tense chest muscles and fast breathing both play a role. Because anxiety and heart problems can look alike, the first episode should always be checked by a doctor.
Can Acid Reflux Cause Sharp Pain in the Sternum?
It can. Reflux usually burns, but esophageal spasm can cause sudden, sharp, squeezing pain behind the breastbone that feels like a heart problem. Pain linked to meals, lying down, or a sour taste points toward reflux. New or severe pain still needs a heart check before blaming the stomach.
How Long Does Costochondritis Last?
Many cases improve within a few weeks with rest and anti-inflammatory medicine. Some last several months. In one emergency department study, 55% of costochondritis patients still had chest pain a year later, though fewer still had clear costochondritis. Pain lasting beyond six to eight weeks deserves a follow-up visit.
Why Does the Sternum Hurt When Lying Down?
Lying flat can worsen reflux, because stomach acid flows up more easily. It’s also the classic sign of pericarditis, where pain eases when you sit up and lean forward. Lying face down can hurt with a sternum bruise. Pericarditis-type pain needs a same-day medical visit.
Is Sternum Pain After Lifting Weights Serious?
Usually not. Bench presses, pushups, and heavy carrying can strain chest muscles or irritate rib cartilage. The pain tends to be sore and worse with arm movement. If pain began during the lift with pressure, shortness of breath, or sweating, treat it as a possible heart problem and call 911.
Can Gas Cause Sharp Sternum Pain?
Trapped gas in the stomach or upper colon can cause sharp pain that seems to come from the lower chest. It often moves around, eases after burping or passing gas, and is linked to meals. Gas does not cause sweating, shortness of breath, or arm pain. Those symptoms point elsewhere.
Why Does the Sternum Hurt When Swallowing?
Pain with swallowing usually points to the esophagus. Reflux, esophageal spasm, and pill esophagitis are common causes. Pills like doxycycline, NSAIDs, and potassium can irritate the esophagus if they get stuck. Take pills with a full 8-ounce glass of water and stay upright for 30 minutes afterward.
Should You Go to the ER or Urgent Care for Sternum Pain?
Go to the ER, by ambulance, for any red flag: pressure, shortness of breath, sweating, fainting, or pain spreading to the arm, jaw, or back. Urgent care fits mild, clearly chest-wall pain with no red flags. Many urgent care centers can’t run troponin tests, so heart concerns belong in the ER.
Can Costochondritis Come Back?
Yes. Costochondritis can flare again, often after heavy lifting, a bad cough, or a return to hard workouts too quickly. Easing back into exercise, treating coughs early, and working on posture can lower the risk. Each new episode with different or stronger symptoms should be checked, not assumed.
Disclaimer: This article is for general information only and is not a substitute for medical advice, diagnosis, or treatment. Chest pain can be a sign of a life-threatening emergency. If you have chest pain with pressure, shortness of breath, sweating, nausea, fainting, or pain spreading to your arm, jaw, or back, call 911 immediately. Cost figures are general estimates and vary by location and insurance plan. Always talk with a qualified healthcare provider about your symptoms.
References
- 2021 AHA/ACC/ASE/CHEST/SAEM/SCCT/SCMR Guideline for the Evaluation and Diagnosis of Chest Pain: Executive Summary (JACC)
- 2021 AHA/ACC Chest Pain Guideline, Full Text (Circulation)
- American Heart Association: New Guidelines Help Doctors Diagnose Chest Pain
- Swap CJ, Nagurney JT. Value and Limitations of Chest Pain History. JAMA 2005
- Disla E, et al. Costochondritis: A Prospective Analysis in an Emergency Department Setting. Arch Intern Med 1994
- American Family Physician: Costochondritis Rapid Evidence Review (2021)
- American Family Physician: Costochondritis Diagnosis and Treatment (2009)
- American Family Physician: Chest Pain Evaluation, Updated AHA/ACC Guidelines (2023)
- StatPearls: Costochondritis (NCBI Bookshelf)
- Mayo Clinic: Costochondritis Symptoms and Causes
- Cleveland Clinic: Costochondritis