Crohn’s disease and endometriosis share enough symptoms (belly pain, diarrhea, bloating, exhaustion) that many women go years without a clear answer about which one they have. Timing is usually the first thing that separates them, and a few specific tests do the rest.
Table of Contents
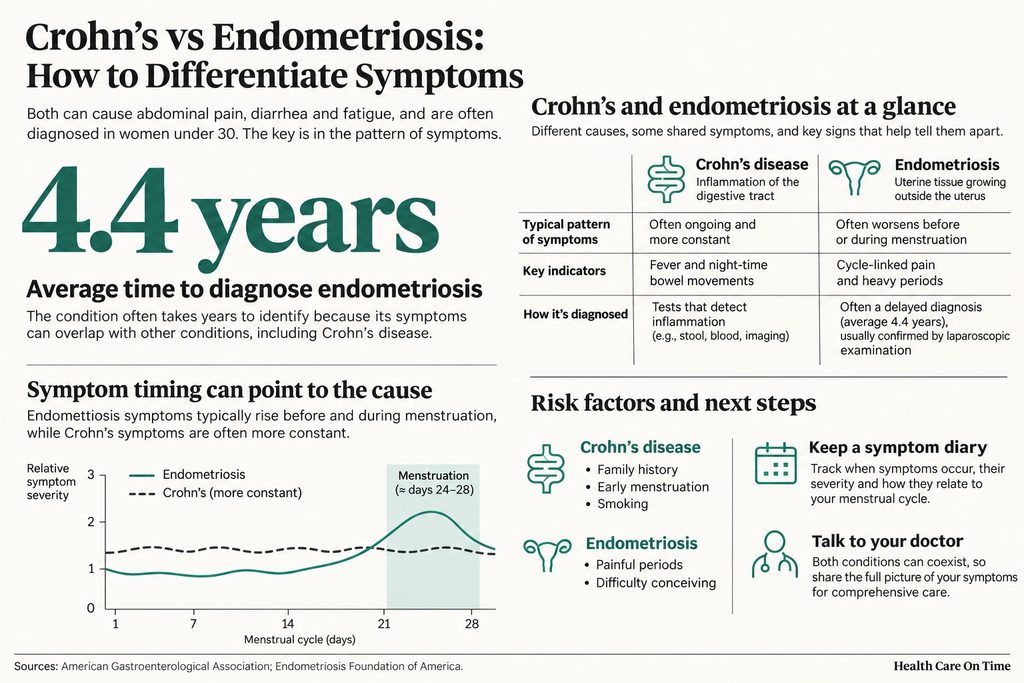
Quick answer: Endometriosis symptoms usually build before and during your period, often with painful periods, pain during sex and pain with bowel movements. Crohn’s symptoms don’t follow your cycle as closely and are more likely to bring fever, weight loss, diarrhea that wakes you at night, mouth sores or blood in the stool. A stool calprotectin test and colonoscopy look for Crohn’s; imaging and laparoscopy look for endometriosis. Some women have both.
Why Crohn’s and endometriosis get mixed up
Both conditions show up in the same years of life. Most people with Crohn’s are diagnosed before age 30, and endometriosis affects roughly 5% to 10% of women of menstruating age. So a woman in her 20s with cramping, loose stools and fatigue fits the profile for either one, and her doctor’s first guess often depends on which specialist she happens to see.

The symptoms overlap more than most people expect. Endometriosis is tissue similar to the uterine lining growing outside the uterus, and in some women that tissue grows on or into the bowel. When it does, it can cause the same kind of crampy pain, diarrhea or constipation that Crohn’s causes.
Crohn’s is a long-term inflammation of the digestive tract. Besides belly pain and diarrhea, it can bring fever, mouth sores, appetite loss and deep fatigue, and it can affect the joints, skin, eyes, liver and bones. When the main complaints are low cramping and constant tiredness, though, the whole thing can feel gynecologic, and the first appointment is often with a gynecologist.
Diagnosis is slow on the endometriosis side especially. A 2017 survey of 638 US women with diagnosed or suspected endometriosis put the average time from first symptoms to diagnosis at 4.4 years. Women whose diagnosis came through an ob-gyn got there faster, about 21.5 months from the first visit compared with 40.3 months when other clinicians made the diagnosis. A written record of when the pain comes, what your stool looks like and whether you’ve lost weight gives that first doctor much more to work with.
Timing is the strongest clue
Do your symptoms rise and fall with your menstrual cycle? Start there.
What a cycle-linked pattern looks like
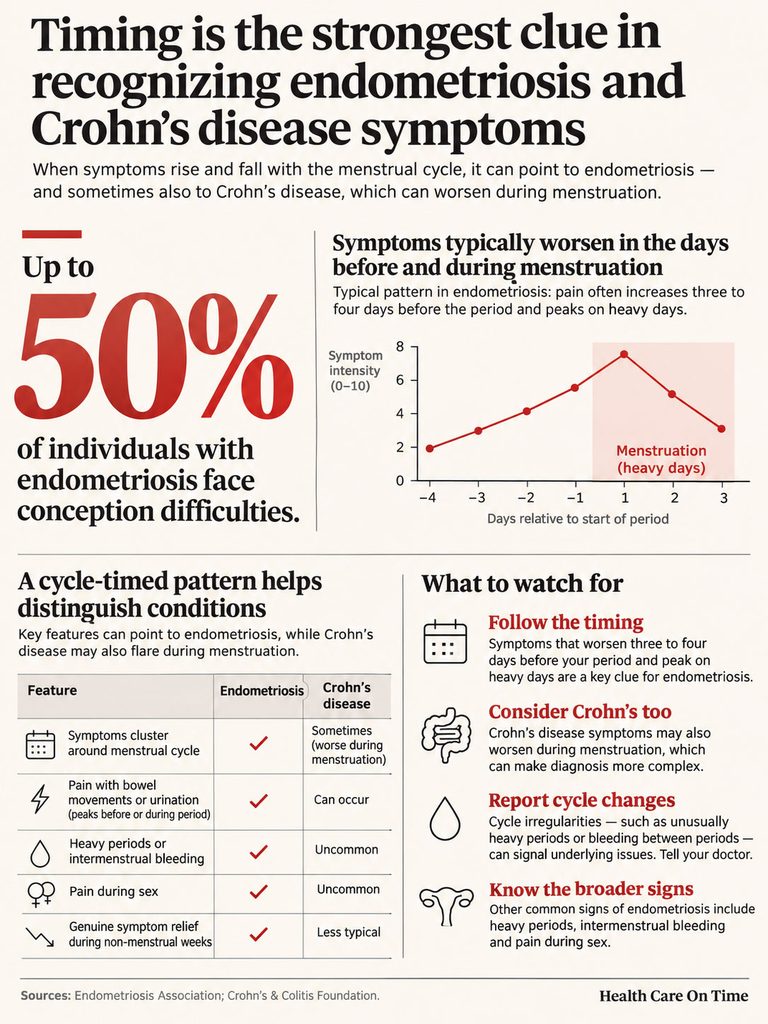
Endometriosis is driven by hormones, so its symptoms tend to cluster around your period. Pain with bowel movements or urination is most likely before or during a period, and diarrhea, constipation, bloating and nausea are more common at those times too. Period pain from endometriosis often starts before bleeding begins and lasts into it, sometimes with low back pain.
A typical pattern might look like this: you feel fine for most of the month, then three or four days before your period you start bloating, your bowel movements become painful or loose, and the pain peaks on the first heavy days. A week later it fades. That rhythm, repeated month after month, leans hard toward endometriosis.
Now picture the other version. You have loose stools most mornings. Some weeks are worse than others. You get up at night to use the bathroom. Your jeans are looser than they were in spring, and you haven’t been trying. Your period makes the cramps worse for a few days, but the good weeks never quite arrive. That picture fits Crohn’s far better, even though the period still plays a part.
Other cycle-related signs add to the picture: heavy periods, bleeding between periods, pain during or after sex, and trouble getting pregnant. Up to half of people with endometriosis have difficulty conceiving, although many with mild or moderate disease still conceive. Lighter bowel changes before a period, the kind that arrive with mood swings and sore breasts and ease once bleeding starts, usually belong with ordinary premenstrual symptoms instead.
Why Crohn’s can also get worse around your period
Crohn’s can flare around your period as well, which blurs the line. In a large survey of women with Crohn’s or ulcerative colitis, over half said their symptoms got worse during menses, probably because of hormone shifts, even though the disease itself stays active all month. Crohn’s can also shift the cycle itself; in the Ocean State Crohn’s and Colitis Area Registry, 25% of women had a change in cycle length in the year before their IBD diagnosis. If your periods have become irregular at the same time your bowel habits changed, mention both to your doctor in the same visit.
The more telling detail is whether you get two or three genuinely good weeks between periods.
Crohn’s and endometriosis side by side
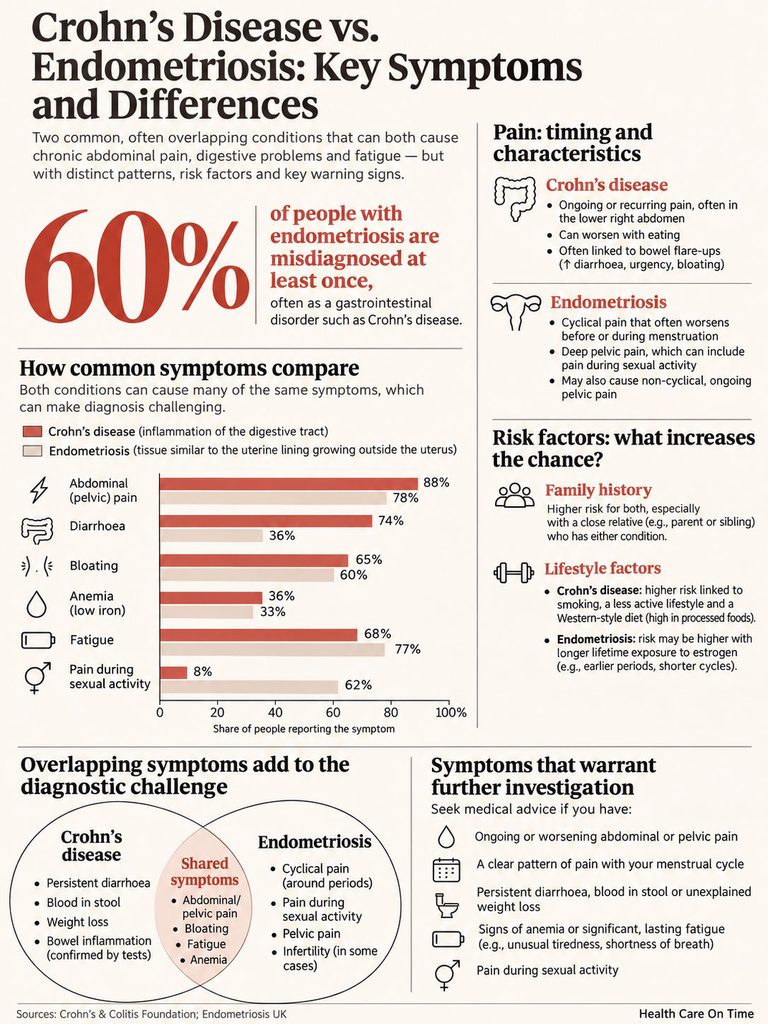
| Feature | Crohn’s disease | Endometriosis | What it suggests |
| Timing of pain | Present most days, can worsen near periods | Builds before and during periods, often eases after | Pain that disappears between periods points to endometriosis |
| Diarrhea | Common; can last more than 1 to 2 weeks and wake you at night | Occurs, mostly before or during periods | Night-time diarrhea points to Crohn’s |
| Blood in stool | A listed Crohn’s symptom, though not always visible | Rare, even with bowel endometriosis | Recurrent blood calls for a colonoscopy |
| Fever | Can occur with active inflammation | Unusual | Fever with gut symptoms points to Crohn’s |
| Weight loss | Common, often unplanned | Not on the usual symptom list | Unexplained weight loss points to Crohn’s |
| Pain during or after sex | Not on the core symptom list | A classic symptom | Deep pain with sex points to endometriosis |
| Mouth sores, joint, skin or eye problems | Can appear outside the gut | Not on the usual symptom list | These point to Crohn’s |
| Family history and habits | Up to 1 in 5 have an affected relative; smoking raises risk | Mother, aunt or sister with it raises risk | A relative with either condition is worth mentioning |
Signs that lean toward Crohn’s
Crohn’s core symptoms are diarrhea with fever, fatigue, belly pain, blood in the stool, mouth sores, reduced appetite with weight loss, and pain or drainage near the anus from a fistula. Of those, fever separates the two best, since it’s unusual with endometriosis. Family history counts as well. Up to 1 in 5 people with Crohn’s have an affected family member, and smoking raises both the risk of Crohn’s and the chance of more severe disease.
Waking up at night to have a bowel movement is another. Primary care doctors are taught to treat night-time bowel movements, unintended weight loss, iron-deficiency anemia, fever, diarrhea lasting more than four weeks and perianal fistula or abscess as red flags for IBD. Signs outside the gut count too: arthritis, eye inflammation, painful red bumps on the shins and recurring mouth ulcers. Women tend to treat each of these as a separate nuisance, which is part of why the early signs of Crohn’s in women so often go unconnected for a long time.
Crohn’s can also affect the area between the rectum and vagina. A rectovaginal fistula, an abnormal channel that can let gas or stool pass through the vagina, is uncommon, affecting roughly 2.3% of women with Crohn’s in the one study that measured it. If it happens, Crohn’s is the usual cause, and it needs prompt care.
What makes endometriosis more likely
Very painful periods, pain during or after sex, pain with bowel movements that shows up around your period, heavy periods, spotting between periods and difficulty getting pregnant all fit. Some women learn they have endometriosis only during infertility testing.
Known risk factors include starting periods early, short cycles of less than 27 days, heavy periods lasting longer than seven days, never having given birth, and a mother, aunt or sister with endometriosis.
In bowel endometriosis, the tissue usually sits on the outer layers of the bowel wall and rarely breaks through the inner lining, so rectal bleeding is rare. Repeated blood in the stool is more typical of Crohn’s or another inflammatory problem and should be checked either way.
Anemia and tiredness can come from either side
Both conditions can wear you out, sometimes through the same route. Crohn’s can lead to iron-deficiency anemia through bleeding and poor absorption, and it can also leave you low in vitamin B12. Heavy periods, which are common with endometriosis, drain iron as well.
If a blood test shows low iron, the next thing to work out is where the iron is going. Heavy periods alone can explain it, but iron deficiency together with diarrhea, weight loss or a raised calprotectin is a red flag for IBD and deserves a gut workup, even if your periods are also heavy. A woman who has been taking iron for years without a clear reason is worth a second look.
Symptoms that don’t settle it
Crampy lower belly pain, bloating, nausea, diarrhea alternating with constipation, and pain before or during a bowel movement turn up in both conditions and don’t help much on their own. Both can narrow the bowel, too. A tight enough narrowing causes a blockage, with swelling, vomiting and no passing of gas or stool. Severity doesn’t sort them either. Endometriosis pain doesn’t track with how much endometriosis is present, so mild-looking disease can hurt badly and widespread disease can be quiet.
Can you have both?
Yes, and more often than chance alone would predict. Danish researchers tracked 37,661 women hospitalized with endometriosis between 1977 and 2007 in a nationwide cohort, published in Gut in 2012, and compared their rate of inflammatory bowel disease with the general population’s. Women with endometriosis had about a 50% higher rate of IBD overall and about a 60% higher rate of Crohn’s disease specifically. The higher risk was still there about 20 years after the endometriosis diagnosis, and it held up in women whose endometriosis had been confirmed by surgery; the authors read that long-lasting risk as a genuine link and not a fluke of early misdiagnosis.
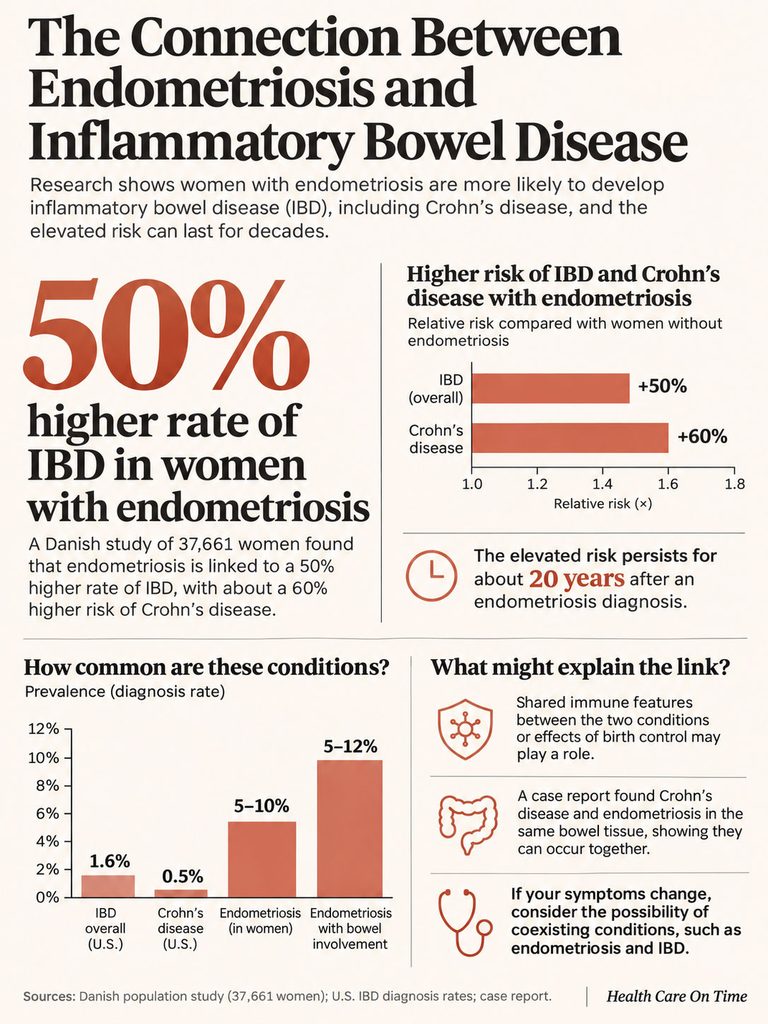
Why the two conditions travel together isn’t settled. The Danish authors suggested shared immune features, or an effect of the birth control pills commonly used to treat endometriosis.
Pathologists have even found both diseases in one piece of bowel. A 2013 case report in the World Journal of Gastroenterology described a woman whose surgically removed ileum showed active Crohn’s disease with endometriosis tissue inside the same lesions. Her symptoms were not tied to her cycle, and she didn’t have painful periods, so nothing pointed to endometriosis until the tissue was examined.
| Figure | Number | Source |
| US adults ever diagnosed with IBD | 1.6% (about 4.1 million) | CDC NCHS, NHIS 2023-2024 |
| US adults ever diagnosed with Crohn’s disease | 0.5% (about 1.3 million); same rate in women and men | CDC NCHS, NHIS 2023-2024 |
| US women vs men with any IBD | 1.7% vs 1.4% | CDC NCHS, NHIS 2023-2024 |
| Women of menstruating age with endometriosis | About 5% to 10% | World Journal of Gastroenterology, 2013 |
| Women with endometriosis who have bowel involvement | 5% to 12% | International Journal of Women’s Health, 2020 |
| Crohn’s risk in women with endometriosis | About 1.6 times the expected rate (37,661 women) | Gut, 2012 (Danish cohort) |
| Average time from endometriosis symptoms to diagnosis | 4.4 years (638 US women) | Journal of Women’s Health, 2017 |
The US figures come from the CDC’s National Health Interview Survey, where women’s higher IBD rate came from ulcerative colitis; Crohn’s ran level between the sexes. If you already have one diagnosis and your symptoms have changed, the other condition is worth asking about. A woman with known Crohn’s whose pain now arrives like clockwork before each period, or a woman with known endometriosis who starts losing weight and waking at night with diarrhea, has a reason to go back and ask whether something new is going on. Neither diagnosis protects you from the other, and having one on your chart can make it easier for a new symptom to be blamed on the old condition.
Where IBS fits in
Irritable bowel syndrome muddies things further. It causes belly pain and changes in bowel habits without visible inflammation, and it overlaps heavily with endometriosis. A 2022 meta-analysis found almost three times the odds of IBS in women with endometriosis (pooled odds ratio 2.97), and about 23.4% of women with endometriosis also had IBS. IBS has no specific test, so it’s often the first label a woman with bowel symptoms is given, whatever is really going on.
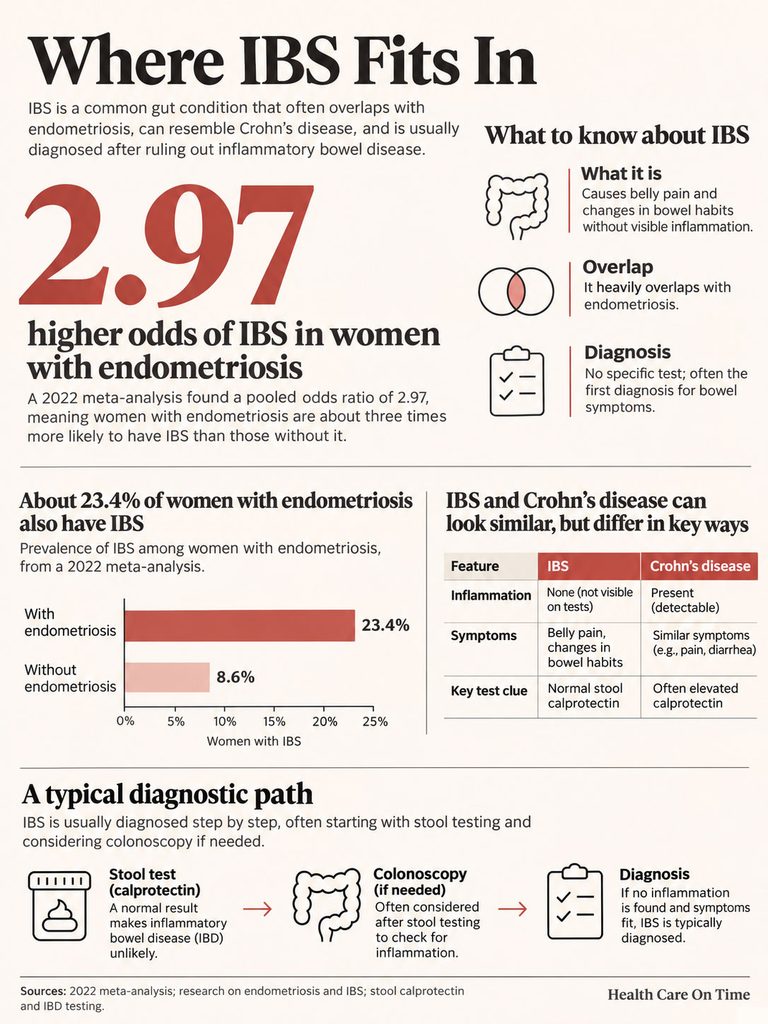
IBS and Crohn’s feel similar but differ in one measurable way: Crohn’s causes inflammation that tests can detect, and IBS doesn’t. A normal stool calprotectin test makes IBD unlikely, which is often the first step in deciding whether a colonoscopy is needed.
How doctors sort it out
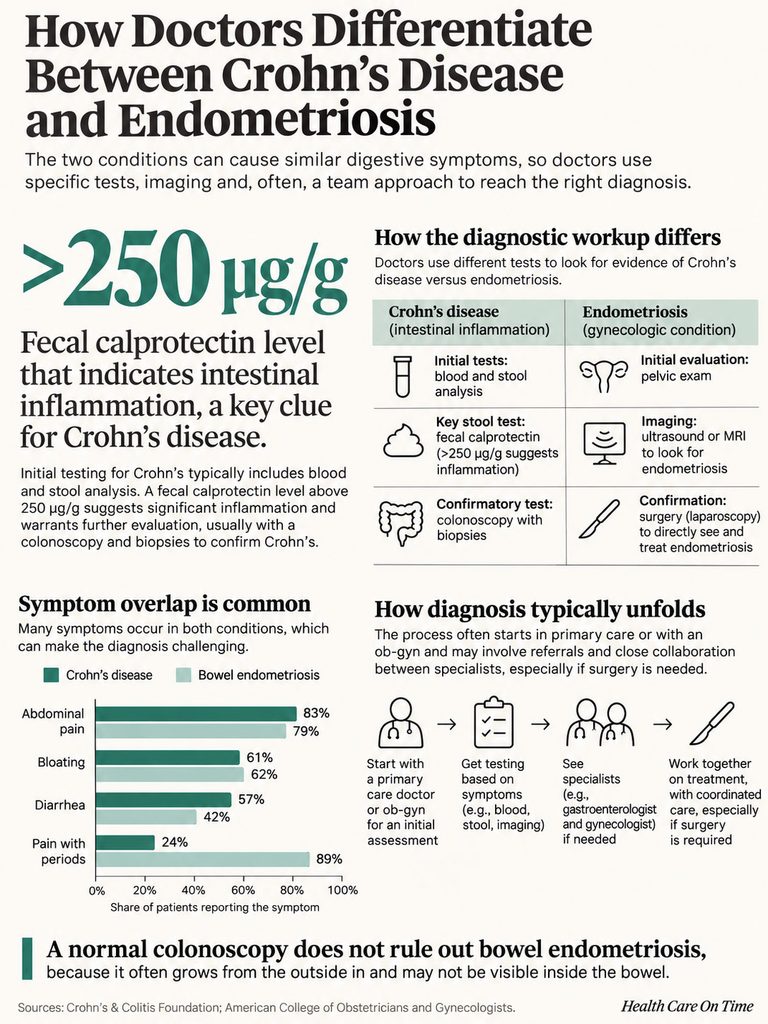
No single test answers “Crohn’s or endometriosis?” Doctors usually check for inflammation in the gut first, because those tests are simple and noninvasive, then look at the pelvis.
Tests that look for Crohn’s
The workup for Crohn’s usually starts with blood and stool. Blood tests check for anemia and signs of inflammation, often with iron studies and celiac testing added when diarrhea has gone on for a while. Stool tests rule out infection and measure markers of inflammation.
The key stool test is fecal calprotectin, a protein that white blood cells release into the intestine when it’s inflamed. Its main job is telling IBD apart from IBS: a normal result usually means the bowel isn’t inflamed, while a high result usually leads to a colonoscopy. A level above 250 µg/g is a strong sign of inflammation and a reason to see a gastroenterologist. The test has limits: infections, ibuprofen and similar painkillers, and some other bowel problems can raise it, and a normal value doesn’t completely rule out IBD. Tell your doctor if you take NSAIDs or acid-reducing pills, since these can affect the result.
Colonoscopy with biopsies is the main test for Crohn’s. The scope examines the colon and the end of the small intestine (the terminal ileum), and tissue samples are taken even if the lining looks normal. CT or MR enterography images the small bowel and can show narrowing, fistulas and inflammation the scope can’t reach. Capsule endoscopy, a swallowed camera, is another option for the small intestine, though it isn’t used if a blockage is suspected.
Finding endometriosis: exam, imaging and surgery
A pelvic exam can sometimes find tender spots, nodules or cysts, though small patches usually can’t be felt. A transvaginal ultrasound can find endometriomas (cysts on the ovaries) and, in experienced hands, deep endometriosis on the bowel. MRI shows where growths are and how big they are, and for bowel endometriosis its reported sensitivity is 88% with 98% specificity.
Surgery is still the only way to confirm endometriosis. In a laparoscopy, a surgeon looks inside the abdomen through a small cut near the navel, takes tissue samples and can often remove endometriosis during the same procedure.
Why a normal colonoscopy doesn’t rule out bowel endometriosis
Colonoscopy looks only at the inside lining of the bowel. Bowel endometriosis usually grows from the outside in and rarely involves the lining, so a colonoscopy can look completely normal in a woman who has it. Most bowel endometriosis sits in the rectum and sigmoid colon (up to 90% of intestinal lesions), close to the uterus and ovaries. Endometriosis on the terminal ileum, the stretch of small intestine a colonoscopy checks for Crohn’s, is less common: about 1% to 7% of intestinal endometriosis.
If your colonoscopy is clean and your stool calprotectin is normal but your pain still follows your cycle, the next step is usually pelvic imaging with a specialist, not another round of gut tests.
Which doctor to start with
Start with whoever can order the first round of tests, usually your primary care doctor or ob-gyn. If your symptoms are mostly cycle-linked pelvic pain, an ob-gyn is a good first stop. Whoever you see, bring the diary, a list of every medicine and supplement you take, any old lab results showing low iron, and the dates and results of any colonoscopy or pelvic ultrasound you’ve already had, so nobody repeats a test you’ve done or overlooks one that came back abnormal. If you have red flags for Crohn’s such as weight loss, night-time diarrhea, blood in the stool or a raised calprotectin, ask for a gastroenterology referral. There’s no need to finish the gynecology workup first. Both can happen at once.
When both specialists are needed, it helps if they talk to each other. Bowel endometriosis surgery in particular calls for a surgeon skilled in bowel surgery, and those specialists are hard to find in many parts of the country.
Why the right label changes treatment
Crohn’s treatment calms the immune system. The usual options are short courses of corticosteroids, immune-suppressing drugs, biologics, oral JAK inhibitors such as upadacitinib (not for use in pregnancy) and, for some complications, antibiotics. Nearly half of people with Crohn’s may need at least one surgery, but the benefits of surgery are often temporary because the disease frequently comes back.

Endometriosis is treated mainly with hormones and surgery, and the choice depends on how bad the pain is and whether pregnancy is a goal. Hormonal birth control, progestin treatments (including a levonorgestrel IUD, the arm implant and shots), GnRH drugs that create a temporary menopause, and aromatase inhibitors can all reduce pain. Surgery can remove endometriosis tissue, and in bowel endometriosis that sometimes means shaving the lesion off the bowel wall or removing a segment of bowel. Hormone treatment doesn’t cure endometriosis, and symptoms can come back when it stops.
If you turn out to have both, you may end up with two plans running at once, hormonal treatment from a gynecologist and anti-inflammatory treatment from a gastroenterologist, and it’s reasonable to ask both doctors to work out which condition a new symptom belongs to before either plan changes.
Hormones do nothing for Crohn’s inflammation, and the immune drugs used for Crohn’s aren’t endometriosis treatments. Over-the-counter NSAIDs such as ibuprofen and naproxen are a common first step for period pain, but they can worsen bowel inflammation in Crohn’s. If you think you might have Crohn’s, ask your doctor before relying on NSAIDs for cramps.
If you’re trying to get pregnant
With endometriosis, up to half of people have trouble conceiving, and treatment may include surgery, ovulation-stimulating medicine or in vitro fertilization through a reproductive endocrinologist. With Crohn’s, some medicines need a plan before pregnancy, upadacitinib among them. If pregnancy is on your horizon, say so early, because it can change which tests and treatments come first.
What happens if it isn’t treated
Poorly controlled Crohn’s can lead to bowel narrowing and blockage, ulcers, fistulas, abscesses and anal fissures, along with malnutrition, osteoporosis, kidney stones and a higher risk of colon cancer.
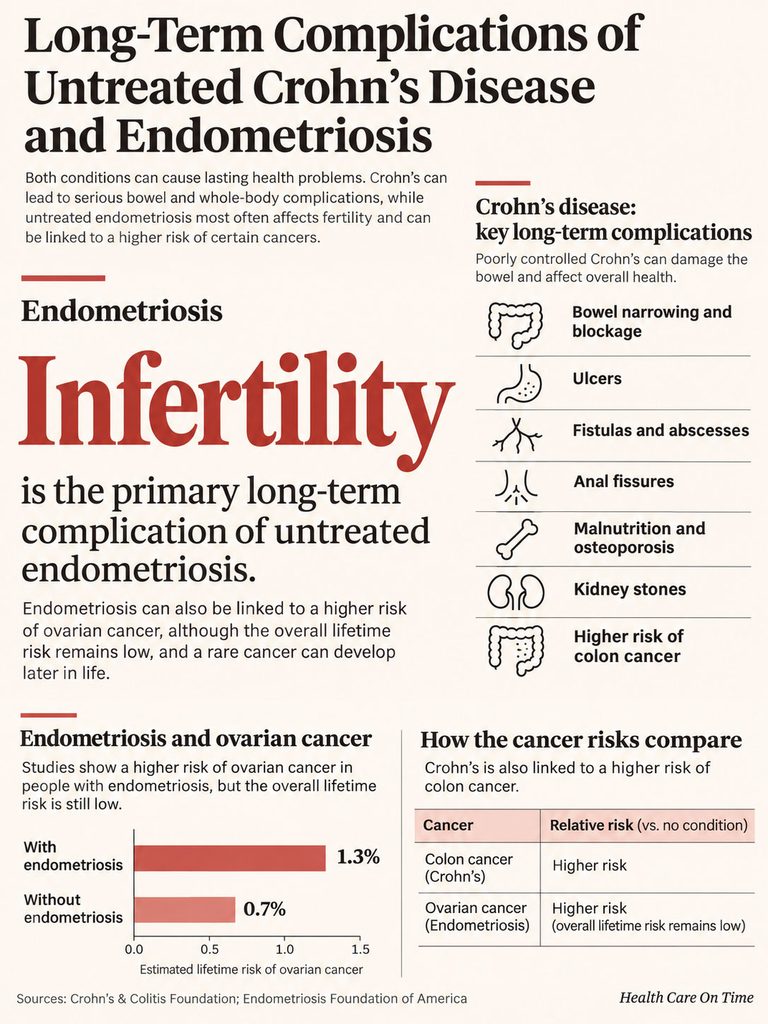
For endometriosis, the main long-term complication is infertility. Some studies suggest a higher risk of ovarian cancer, though the overall lifetime risk stays low, and a rare cancer linked to endometriosis can appear later in life.
Keep a two-cycle symptom diary
A diary kept for two full menstrual cycles often tells your doctor more than a single description can. It doesn’t need to be elaborate. Write down, each day:

- Cycle day (day 1 is the first day of bleeding).
- Belly or pelvic pain, rated 0 to 10, and where it sits (low pelvis, rectum, around the navel, one side or both).
- Bowel movements: how many, how loose, and whether any woke you at night.
- Any blood or mucus in the stool.
- Fever or chills, and your temperature if you take it.
- Pain during sex, if relevant.
- Medicines you took, including over-the-counter painkillers.
Weigh yourself once a week at the same time of day. A slow, unplanned drop over two months is easy to miss without numbers. Clothes fitting differently counts as a clue too. If you already use a period-tracking app, add the bowel notes to it so the two records line up day by day, which makes a pattern far easier to spot than two separate lists kept in different places.
At the end of two cycles, look at the pattern before your appointment. If most bad days cluster in the week before and the first days of your period, say so; if bad days are scattered through the month, say that too, and bring the diary itself.
When to see a doctor, and when to go now
Make an appointment if you’ve had ongoing changes in bowel habits, belly pain or diarrhea lasting more than one to two weeks, or periods painful enough to keep you home. Some situations can’t wait for a routine visit, though.

| Situation | What to do | Why it matters |
| Severe belly pain with vomiting, swelling and no gas or stool | Go to the emergency room now | Both conditions can block the bowel |
| Fever with belly pain and diarrhea | Call your doctor the same day | Points to active inflammation or an abscess |
| Painful lump or drainage near the anus or vagina | See a doctor within a day or two | Possible abscess or fistula from Crohn’s |
| Gas or stool passing through the vagina | Book an urgent appointment | Possible rectovaginal fistula |
| Diarrhea more than four weeks, night-time stools or weight loss | Ask for stool calprotectin and a GI referral | These are IBD red flags |
| Pain with bowel movements mostly before and during periods | See an ob-gyn and bring a symptom diary | Fits endometriosis, including bowel endometriosis |
| Normal colonoscopy but cycle-timed pain continues | Ask about pelvic MRI or specialist ultrasound | Colonoscopy can miss bowel endometriosis |
Very heavy bleeding, fainting, or chest pain and shortness of breath alongside anemia symptoms are also reasons to get care right away.
Questions to ask at your appointment
Write these down and take them with you, and cross off any your doctor answers before you ask.
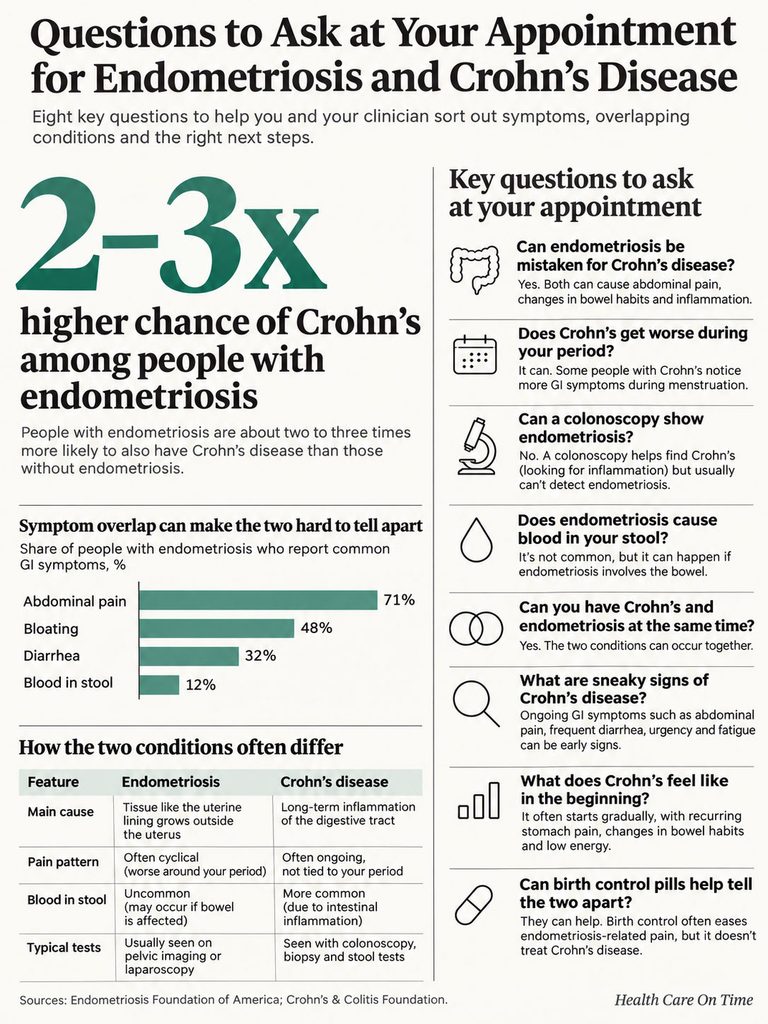
- Does this pain pattern sound more like endometriosis, Crohn’s or both?
- Is a stool calprotectin test worth doing first?
- If the colonoscopy comes back normal, what’s the next step for the pelvic pain?
- Can a transvaginal ultrasound or MRI look for endometriosis on the bowel?
- Is it safe to keep taking ibuprofen for period cramps while we figure this out?
- Would it help to see a gastroenterologist and a gynecologist who work together?
- If we’re planning a pregnancy, how would either condition change the plan?
Frequently Asked Questions
Can endometriosis be mistaken for Crohn’s disease?
It can, mainly when endometriosis grows on the bowel and causes crampy pain, diarrhea, constipation or even narrowing. A 2015 case described a 45-year-old woman whose bowel endometriosis looked like Crohn’s on a CT scan. Pain that follows your cycle is the main clue that endometriosis is involved.
Does Crohn’s get worse during your period?
Many women with IBD notice this; over half of 1,203 women in one large US survey reported worse symptoms during menses. The difference from endometriosis is that Crohn’s symptoms are usually still present between periods, while endometriosis symptoms tend to fade once the period ends.
Can a colonoscopy show endometriosis?
Usually not. A colonoscopy looks at the inner lining of the bowel, and bowel endometriosis typically grows from the outside of the bowel wall inward, rarely reaching the lining. Because of that, a colonoscopy can be completely normal in a woman who has significant bowel endometriosis. A transvaginal ultrasound done by an experienced sonographer or a pelvic MRI is better at finding it, and laparoscopy is the only way to confirm it. Colonoscopy still earns its place, because it’s the main test for Crohn’s and can rule out inflammation of the colon and the end of the small intestine.
Does endometriosis cause blood in your stool?
Only rarely, since bowel endometriosis seldom reaches the bowel lining. Blood in the stool should always be checked, since Crohn’s, hemorrhoids and other conditions can cause it.
Can you have Crohn’s and endometriosis at the same time?
Yes. A Danish study of 37,661 women with endometriosis found about 1.6 times the expected rate of Crohn’s disease, and the higher risk lasted for decades after the endometriosis diagnosis.
What are sneaky signs of Crohn’s disease?
Some of the easiest Crohn’s signs to miss are fatigue from iron-deficiency anemia, mouth sores, joint pain, painful red bumps on the shins, eye inflammation and small tears or drainage near the anus. Unplanned weight loss and a low fever are also easy to overlook. In some women, a change in cycle length shows up in the year before the diagnosis.
What does Crohn’s feel like in the beginning?
Early Crohn’s often feels like belly cramping, loose stools that don’t settle down, tiredness that sleep doesn’t fix and a smaller appetite. Those symptoms are easy to blame on stress, food or your period, which is one reason Crohn’s can take a while to diagnose.
Can birth control pills help tell the two apart?
Not reliably, and they shouldn’t be used as a test. Hormonal birth control is a standard treatment for endometriosis pain, so cycle-linked pain often improves on it, but improvement doesn’t prove endometriosis, and continuous use can stop periods, which removes the cycle pattern you’d otherwise track. The pill doesn’t treat Crohn’s inflammation. The Danish cohort authors raised the possibility that oral contraceptives used for endometriosis might be part of why IBD is more common in these women, though that link isn’t proven. If you’re thinking about starting or stopping birth control because of bowel symptoms, talk with your doctor first, and ask whether a calprotectin test should come before any trial of hormones.
Medical disclaimer: This article is for general information and isn’t a substitute for advice from your own doctor. Crohn’s disease and endometriosis need a professional diagnosis. If you have severe pain, fever, signs of a bowel blockage or heavy bleeding, seek medical care right away.
References
- Mayo Clinic. Crohn’s disease: Symptoms and causes. Updated September 15, 2026. https://www.mayoclinic.org/diseases-conditions/crohns-disease/symptoms-causes/syc-20353304
- Mayo Clinic. Crohn’s disease: Diagnosis and treatment. Updated September 15, 2026. https://www.mayoclinic.org/diseases-conditions/crohns-disease/diagnosis-treatment/drc-20353309
- Cleveland Clinic. Crohn’s disease. Reviewed April 23, 2026. https://my.clevelandclinic.org/health/diseases/9357-crohns-disease
- Mayo Clinic. Endometriosis: Symptoms and causes. August 30, 2024. https://www.mayoclinic.org/diseases-conditions/endometriosis/symptoms-causes/syc-20354656
- Mayo Clinic. Endometriosis: Diagnosis and treatment. August 30, 2024. https://www.mayoclinic.org/diseases-conditions/endometriosis/diagnosis-treatment/drc-20354661
- Eunice Kennedy Shriver National Institute of Child Health and Human Development. Endometriosis. Reviewed February 21, 2020. https://www.nichd.nih.gov/health/topics/endometriosis
- Dahlhamer JM, Terlizzi EP. Inflammatory Bowel Disease Among Adults Age 18 and Older: United States, 2023-2024. NCHS Health E-Stats No. 122. CDC, 2026. https://cdc.gov/nchs/data/hestat/hestat122.htm
- Jess T, Frisch M, Jørgensen KT, Pedersen BV, Nielsen NM. Increased risk of inflammatory bowel disease in women with endometriosis: a nationwide Danish cohort study. Gut. 2012;61(9):1279. https://gut.bmj.com/content/61/9/1279
- Kaemmerer E, Westerkamp M, Kasperk R, Niepmann G, Scherer A, Gassler N. Coincidence of active Crohn’s disease and florid endometriosis in the terminal ileum: a case report. World J Gastroenterol. 2013;19(27):4413-4417. https://pmc.ncbi.nlm.nih.gov/articles/PMC3718912
- Habib N, Centini G, Lazzeri L, et al. Bowel endometriosis: current perspectives on diagnosis and treatment. Int J Womens Health. 2020;12:35-47. https://www.dovepress.com/bowel-endometriosis-current-perspectives-on-diagnosis-and-treatment-peer-reviewed-fulltext-article-IJWH
- Saha S, Zhao YQ, Shah SA, et al. Menstrual cycle changes in women with inflammatory bowel disease: a study from the Ocean State Crohn’s and Colitis Area Registry. Inflamm Bowel Dis. 2014;20(3):534-540. https://scholars.mssm.edu/en/publications/menstrual-cycle-changes-in-women-with-inflammatory-bowel-disease–2/
- The Influence of Hormonal Fluctuation on Inflammatory Bowel Disease Symptom Severity: A Cross-Sectional Cohort Study. Inflamm Bowel Dis. 2018;24(2):387-393. https://pubmed.ncbi.nlm.nih.gov/29361085/
- Nabi MY, Nauhria S, Reel M, et al. Endometriosis and irritable bowel syndrome: a systematic review and meta-analyses. Front Med. 2022;9:914356. https://frontiersin.org/articles/10.3389/fmed.2022.914356/full
- Factors Associated with Time to Endometriosis Diagnosis in the United States. J Womens Health. 2017. https://journals.sagepub.com/doi/pdf/10.1089/jwh.2016.6003
- A systematic review of the patient burden of Crohn’s disease-related rectovaginal and anovaginal fistulas. BMC Gastroenterol. 2022;22(1). https://doaj.org/article/9ef0be6ecf824740835382cff2083d8a
- MedlinePlus. Calprotectin stool test. Updated January 9, 2024. https://medlineplus.gov/lab-tests/calprotectin-stool-test
- Nebraska Medicine. When should you suspect inflammatory bowel disease? Recognizing red flags in primary care. August 18, 2026. https://www.nebraskamed.com/node/33931
- Endometriosis Foundation of America. Life with Crohn’s and endometriosis: an overlap of painful symptoms. July 16, 2018. https://www.endofound.org/life-with-crohns-and-endometriosis-an-overlap-of-painful-symptoms